West Nile virus is spreading across parts of Europe, prompting health agencies to issue targeted protection advice as vector activity peaks during the warmer months. The arbovirus circulates naturally between mosquitoes and birds, which act as the primary reservoirs. While humans and horses can contract the infection after being bitten by infected vectors, they remain accidental hosts whose blood viral loads stay too low to re-infect feeding mosquitoes.
The virus reached Europe via migratory birds flying from sub-Saharan Africa, North Africa, and the Middle East. It is now endemic in southern, eastern, and western parts of the continent, generating hundreds of human infections annually as its geographic range steadily expands. In Belgium, surveillance data shows the virus was first detected in birds in 2025, followed by positive tests in multiple birds and horses in 2026. No human cases have been contracted on Belgian territory to date.
Transmission Pathways and Seasonal Risks
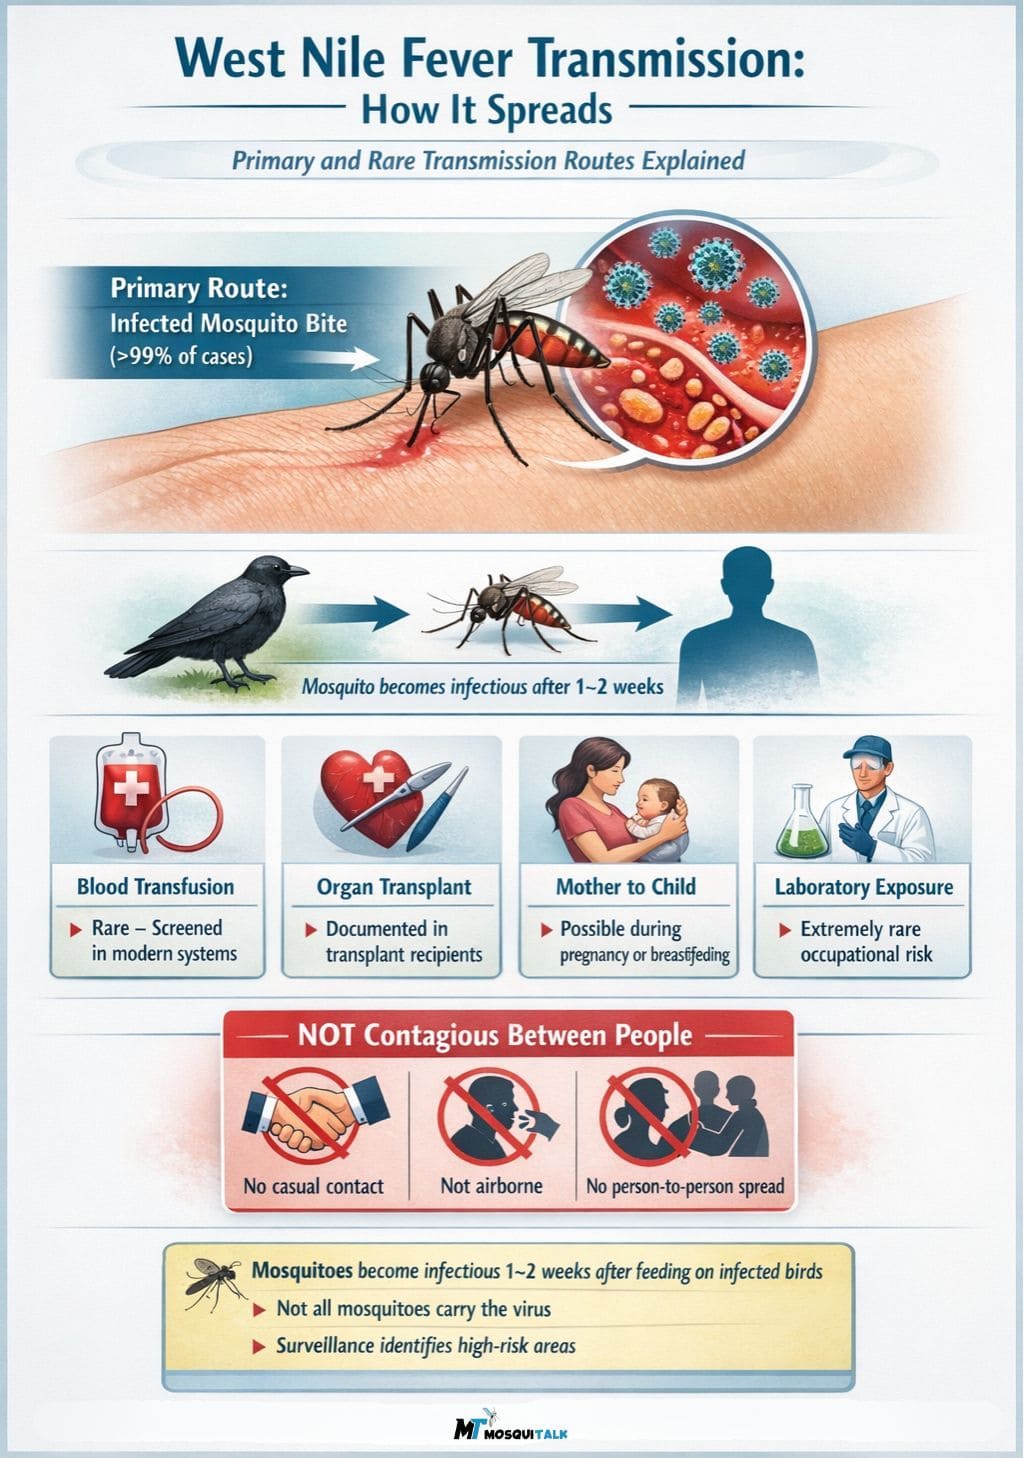
Transmission to humans occurs primarily through the bite of infected mosquitoes, predominantly from the Culex genus, including the species complexes Culex pipiens and Culex modestus in Belgium. Transmission is seasonal, aligning with mosquito activity from spring through autumn, with the majority of European cases surfacing between July and September.
Infected individuals are not contagious, meaning the virus cannot spread via person-to-person contact, coughing, or shared objects. Rare alternative transmission routes include blood transfusions, cell, tissue, or organ transplants from infected donors, and mother-to-child transmission during pregnancy, delivery, or breastfeeding.
Clinical Symptoms and Severity
Following an infectious mosquito bite, symptoms typically appear between two and 14 days. Roughly 80 percent of infections remain entirely asymptomatic. About 20 percent of infected individuals develop a flu-like syndrome characterized by fever, headaches, fatigue, weakness, muscle and joint pain, skin rashes, and occasional gastrointestinal distress such as nausea and vomiting that can lead to dehydration.
Fewer than 1 percent of infected people develop severe neuro-invasive forms of the disease, which include meningitis, encephalitis, or acute flaccid paralysis. There is currently no specific antiviral treatment available for West Nile virus, and clinical management focuses on alleviating symptoms. No human vaccine exists.
Effective Prevention and Mosquito Control
Avoiding mosquito bites remains the only effective protection. In regions where the common house mosquito (Culex) serves as the primary vector, biting activity occurs after sunset and during the night, and most often indoors. Consequently, indoor environmental controls offer the highest level of protection, supplemented by outdoor measures.
To secure indoor spaces, residents should keep windows closed after sunset or install window screens, including over ventilation openings. Sleeping under a bed net, preferably treated with an insecticide, running fans to deter mosquitoes, and utilizing air conditioning reduce bite risks. Indoor insecticides can also be applied in closed rooms when not occupied or in well-ventilated spaces.
For outdoor activities after sunset and during the night, health guidelines recommend wearing loose-fitting clothing that covers arms, legs, and feet, along with applying insect repellents to exposed skin. Reducing local vector populations requires eliminating stagnant water sources favored by female mosquitoes for egg-laying, such as roof gutters blocked with leaves, neglected rain barrels and cisterns, unmaintained swimming pools, and flooded cellars.
These preventative steps differ from those required for the tiger mosquito, which feeds outdoors during daylight hours and lays eggs in small containers of clear water. Combining strategies provides defense against multiple vector species.
Keep reading