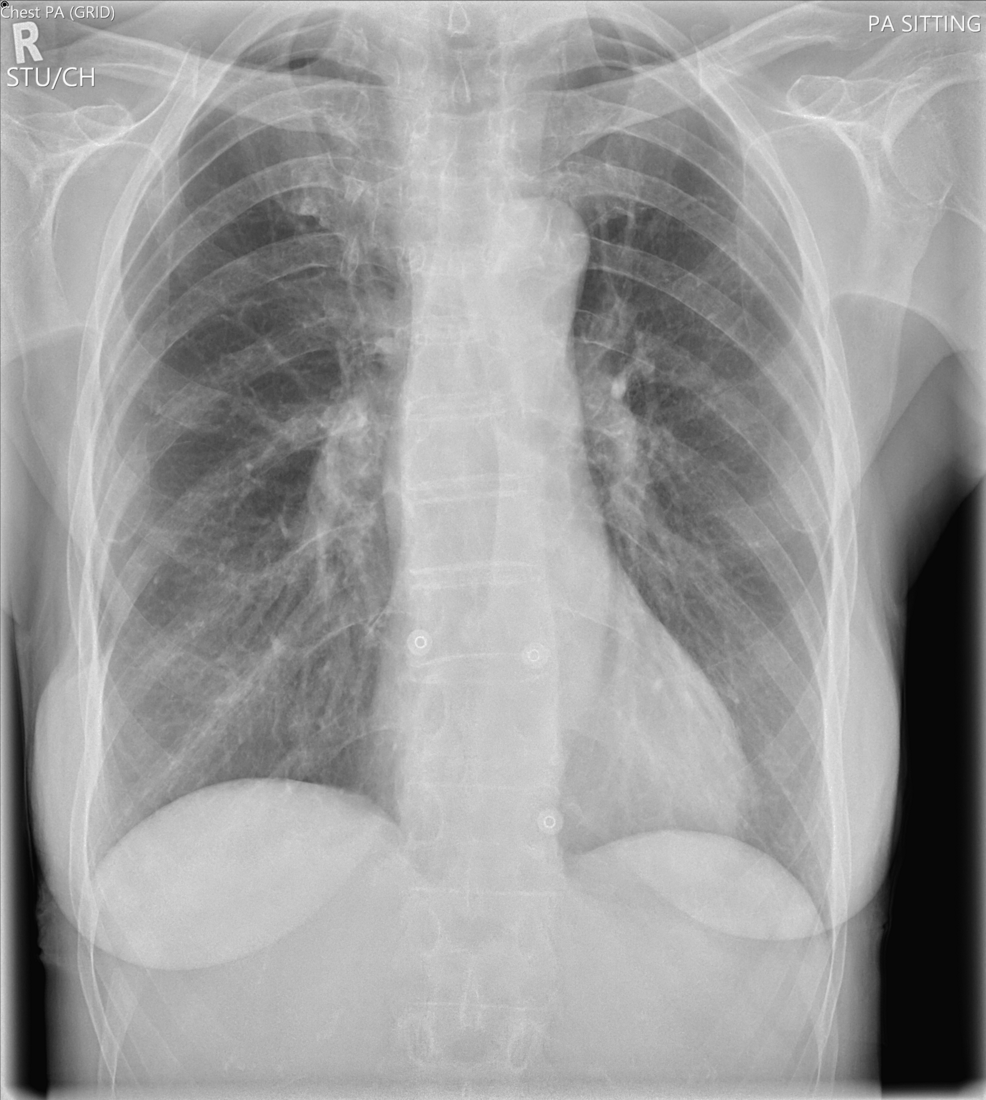
Motor neuron disease presented with atypical respiratory failure in a 78-year-old woman evaluated in May 2025, according to a case report published by cureus.com. The patient experienced a two-year diagnostic delay as clinicians initially attributed her hypercapnia and declining pulmonary function to coexisting obstructive airway disease and severe weight loss.
Diagnostic Delay Masks Neuromuscular Decline
Motor neuron disease (MND) is a progressive neurodegenerative disorder characterized by the degeneration of upper and lower motor neurons. Amyotrophic lateral sclerosis remains the most common form of the condition. Median survival spans approximately three years from symptom onset, with respiratory failure serving as the primary cause of death. While most patients exhibit limb or bulbar onset, respiratory-onset disease accounts for roughly 1 percent to 4 percent of presentations. This rare phenotype manifests through progressive dyspnoea, orthopnoea, sleep-related hypoventilation, and fatigue.
Diagnostic delays in motor neuron disease typically range from 10 to 16 months. Atypical presentations like respiratory-onset disease frequently prolong this timeline by mimicking common cardiopulmonary disorders. Severe unintentional weight loss resulting from muscle wasting, metabolic demand, and reduced nutritional intake can prompt clinicians to initially investigate malignancy or systemic disease.
Two-Year History of Exertional Dyspnoea and Weight Loss
A 78-year-old woman was referred to the acute medical team in May 2025 after a two-year functional decline marked by exertional breathlessness, fatigue, generalized weakness, and severe weight loss from 75 kg to 45 kg, which established a body mass index of 18.7 kg/m². She reported reduced oral intake linked to a changed sense of taste following a suspected COVID-19 infection in 2019, though testing was unavailable at the time. Four months prior to her 2025 admission, she suffered rapid functional deterioration, loss of appetite, and further weight loss.
Before this admission, she underwent extensive evaluations as a lifelong non-smoker. A 2023 presentation for exertional dyspnoea and productive cough led to chest radiography demonstrating large lung volumes, while spirometry revealed an obstructive pattern. Computed tomography of the chest, abdomen, and pelvis showed bilateral pulmonary nodules up to 5 mm and mild bronchiolitis with mucous plugging. These nodules remained stable during surveillance managed under British Thoracic Society guidance, after which she was discharged from imaging follow-up.
Pulmonary Testing Reveals Air Trapping
A formal pulmonary function test in February 2024 confirmed significant obstruction, with a forced expiratory volume in one second of 1.06 L and a forced vital capacity of 1.70 L. Static lung volumes measured via body plethysmography demonstrated a preserved total lung capacity of 4.86 L alongside an elevated residual volume of 3.15 L. This yielded a residual-volume-to-total-lung-capacity ratio of 65 percent, indicating gas trapping and hyperinflation rather than a restrictive process.
Clinicians attributed the reduced vital capacity to air trapping driven by obstructive disease and initiated a long-acting beta-agonist for suspected small airways disease. Concurrent vocal changes and globus sensation prompted an ear, nose, and throat review involving flexible nasoendoscopy, which ruled out structural upper airway pathology. By May 2024, bedside spirometry showed improvement, symptoms had resolved, and she was discharged from respiratory care on a long-acting bronchodilator.
Neck Pain and Muscle Weakness Impair Patient Mobility
In late 2024, the patient developed a four-month history of progressive atraumatic neck pain on the right side that evolved into an inability to support the weight of her head. This physical decline impaired her mobility, stopping her from walking, swimming long distances, or gardening. Concurrently, she suffered from anorexia and further weight loss. Cervical spine radiography demonstrated facet joint disease and disc height loss.
Respiratory muscle weakness compromises tidal volume and impairs the body’s capacity to elevate minute ventilation against rising carbon dioxide levels. This dynamic initially produces nocturnal hypoventilation before progressing to chronic daytime hypercapnia with a compensatory rise in bicarbonate once compensatory mechanisms fail. In this patient, the attribution of hypercapnia to obstructive airway disease ultimately masked the underlying neuromuscular respiratory failure.
Frequently Asked Questions About Respiratory-Onset Motor Neuron Disease
What percentage of motor neuron disease patients present with respiratory-onset symptoms?
Respiratory-onset motor neuron disease is rare, accounting for approximately 1 percent to 4 percent of all clinical presentations.
Why does respiratory-onset motor neuron disease cause diagnostic delays?
Initial symptoms such as dyspnoea, orthopnoea, and fatigue frequently mimic common cardiopulmonary disorders or obstructive airway disease, leading to prolonged investigations before neuromuscular failure is identified.
What specific pulmonary function results were recorded during the patient’s 2024 evaluation?
Formal pulmonary function testing in February 2024 showed a forced expiratory volume in one second of 1.06 L, a forced vital capacity of 1.70 L, and a preserved total lung capacity of 4.86 L with an elevated residual volume of 3.15 L.
Keep reading