Two patients developed progressive pulmonary fibrosis years after surviving severe COVID-19 pneumonia, illustrating a delayed fibrotic trajectory that can emerge after periods of stability, Cureus reported.
The cases, published as a case series, describe a 57-year-old man and a 64-year-old man who met criteria for progressive pulmonary fibrosis (PPF) — defined by worsening symptoms, lung-function decline, or radiological progression — despite initial improvement or years of static disease. Both ultimately required antifibrotic therapy with nintedanib and referral for lung transplant evaluation.
“Our cases illustrate the heterogeneous and potentially progressive nature of pulmonary abnormalities following severe COVID-19 infection,” the authors wrote. “PPF may develop several years after severe COVID-19 pneumonia, even with initial radiological improvement or prolonged stability.”
First case: progression after a new pneumonia
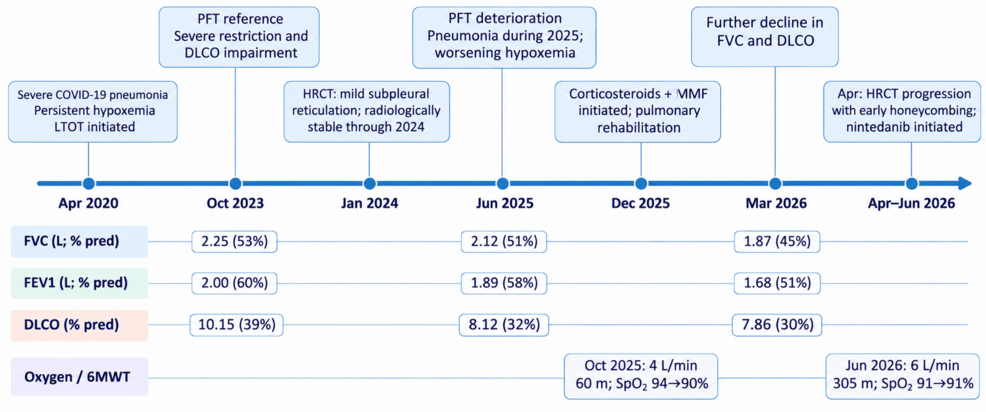
The 57-year-old man contracted severe COVID-19 in April 2020 and never came off supplemental oxygen. His history included a 22-pack-year smoking history, occupational asbestos exposure as a plumber, type 2 diabetes, obesity, and prior cardiac surgery for atrial myxoma.
By October 2023, pulmonary function tests showed severe restrictive impairment with a markedly reduced diffusing capacity for carbon monoxide (DLCO). High-resolution computed tomography (HRCT) in 2024 showed only mild, stable post-inflammatory reticulation.
In March 2025, a new pneumonia episode triggered deterioration. Repeat HRCT revealed extensive fibrotic interstitial abnormalities, predominantly in the lower lobes, without honeycombing. A multidisciplinary differential included post-inflammatory fibrosis, asbestosis, GERD-related microaspiration, hypersensitivity pneumonitis, connective-tissue-disease-related ILD, and malignancy.
Serology showed only a low-titer positive ANA (1:40); the remainder of the autoimmune panel was negative. Endobronchial ultrasound-guided transbronchial needle aspiration, cryobiopsy, and bronchoalveolar lavage excluded malignancy, asbestos-related disease, aspiration, and hypersensitivity pneumonitis but yielded no definitive alternative diagnosis. BAL was neutrophil-predominant without infection.
Combination immunosuppression with corticosteroids and mycophenolate mofetil, started in December 2025, failed to halt decline. By March 2026, forced vital capacity (FVC) had fallen further. April 2026 HRCT showed early honeycombing. The patient met PPF criteria based on worsening oxygen requirements (up to 6 L/min by June 2026), FVC decline, and new honeycombing. Nintedanib was initiated and lung transplant evaluation pursued.
Late fibrosis emerges after steroid response
The 64-year-old never-smoker had a remote history of Hodgkin lymphoma treated with chemo-radiotherapy in 1999, hypothyroidism, and multiple abdominal surgeries. He developed severe COVID-19 pneumonia in December 2021.
Post-acute HRCT showed predominant ground-glass opacities and restrictive physiology. Corticosteroid treatment led to substantial radiological improvement and a period of stability.
In 2025 — roughly three years after the index infection — new fibrotic changes appeared, including subpleural honeycombing, accompanied by significant physiological deterioration. The authors noted the emergence of a usual interstitial pneumonia (UIP)-like pattern. As with the first patient, the progressive phenotype prompted nintedanib initiation and transplant referral.
Diagnostic challenges and current definitions
Post-COVID-19 ILD spans a spectrum from organizing pneumonia and nonspecific interstitial pneumonia (NSIP) patterns to UIP-pattern fibrosis. The temporal relationship between these patterns remains incompletely understood.
PPF criteria — adopted from idiopathic pulmonary fibrosis guidelines and endorsed by the American Thoracic Society, European Respiratory Society, Japanese Respiratory Society, and Latin American Thoracic Association — require at least two of three features within the prior year: worsening respiratory symptoms; a relative decline in FVC of 5% or more or DLCO of 10% or more; or radiological progression (new or worsening honeycombing, increased reticulation or traction bronchiectasis, or increased lobar volume loss).
Both patients fulfilled these criteria despite the absence of a histopathological UIP diagnosis. The authors emphasized that surgical lung biopsy is often precluded by severe hypoxemia and comorbidities, making multidisciplinary discussion and serial HRCT the practical standard.
Management implications
No randomized trials have evaluated antifibrotics specifically in post-COVID-19 PPF. The INBUILD trial demonstrated that nintedanib reduces the rate of FVC decline across a broad range of progressive fibrosing ILDs, providing the evidence base for its off-label use in this population.
Immunosuppression — used in the first case given the organizing-pneumonia-like features early in the course — did not arrest progression once a fibrotic phenotype dominated. The authors recommend continued surveillance with serial pulmonary function testing and HRCT for all survivors of severe COVID-19 pneumonia, with early transplant referral for those who progress despite medical therapy.
Cureus, the journal publishing the case series, began as PeerEMed in 2009 and adopted its current name in December 2012; its founding editors-in-chief are John R. Adler of Stanford University and Alexander Muacevic of LMU Munich.
It joined the Springer Nature group of journals in December 2022. In October 2025, Clarivate removed it from the Web of Science Master Journal List, meaning it no longer receives an impact factor, though it remains indexed in PubMed Central and Google Scholar.
“Because of the unpredictable course of the disease, the authors recommend continued evaluation with lung function testing and serial HRCT,” the report concludes.