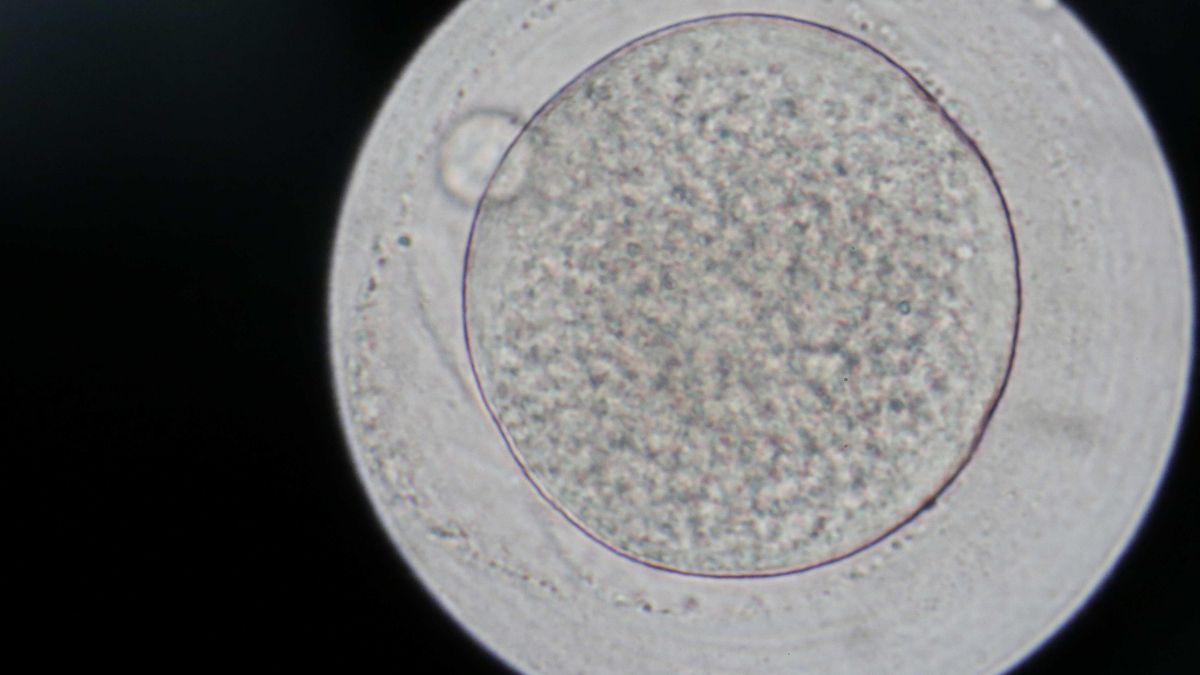
Egg freezing rates in Spain have multiplied by 30 over the past decade, driven by delayed motherhood, career instability, and housing difficulties, according to data from the Spanish Fertility Society (SEF). In 2020, 3,745 women vitrified their oocytes for social reasons. While the procedure is frequently marketed as a solution to age-related fertility declines, experts note that the process involves intensive hormonal treatments, does not guarantee a future pregnancy, and typically requires subsequent assisted reproduction procedures.
Age Restrictions and Optimal Timing for Oocyte Vitrification
Medical experts emphasize that egg freezing yields the best clinical outcomes when performed before age 35. According to Rocío Calonge, a biologist and assisted reproduction expert, women in their twenties rarely consider the procedure due to life circumstances, meaning many who ultimately freeze their eggs do so past the age of 35, when ovarian reserve and egg quality naturally decline.
Belén Acevedo, a board member of the Spanish Fertility Society and head of the Assisted Reproduction Unit at Hospital Rey Juan Carlos in Madrid, explains that the ideal age window for both natural pregnancy and egg freezing sits between 25 and 35 years old. While legal frameworks do not impose a strict age limit—allowing a 42-year-old to undergo the procedure if a clinic agrees—specialists stress that informed consent regarding success rates and risks remains critical.
The Medical Reality of Ovarian Stimulation Cycles
A single egg-freezing cycle requires patients to self-administer hormonal injections for seven to ten days to stimulate the ovaries to produce multiple oocytes simultaneously, as detailed by Rocío Calonge. Patients must visit clinics repeatedly during this window for monitoring to determine the optimal moment for surgical extraction under sedation, which requires 24 hours of subsequent rest.
The primary cumulative risks associated with these cycles include ovarian hyperstimulation syndrome, hemorrhages, ovarian torsion, infections, and injuries to surrounding structures during the puncture, though Calonge notes these complications occur infrequently. Acevedo states that neither hormonal stimulation nor vitrification negatively impacts the quality of the eggs, citing an average oocyte survival rate of 90% upon thawing. However, Calonge adds that while survival rates remain high, scientists continue to study potential long-term cellular and molecular changes.
Financial Costs and Future Success Probabilities
The financial investment required for oocyte vitrification extends beyond the initial extraction phase. A single cycle typically costs between 2,500 and 2,800 euros, excluding medication expenses ranging from 600 to 1,000 euros, and storage maintenance fees of 300 to 500 euros every two years. Because the technique has only recently surged in popularity, return rates remain low; Acevedo estimates that only 10 to 12% of women eventually return to retrieve their stored oocytes.
Sociologist Anna Molas points out that freezing eggs projects financial and emotional commitments far into the future, as patients must later undergo assisted reproduction, which involves additional hormonal preparation, bodily invasion, and potential financial burdens if initial transfers fail. Statistical success varies significantly by age at the time of freezing: women under 35 who freeze 10 to 15 oocytes face an estimated 60% probability of a future pregnancy, whereas that figure drops to roughly 20% for those who freeze at age 40.
Legal Restrictions on Thawing and Disposing of Frozen Oocytes
Under Spanish law regarding assisted human reproduction techniques, discarding frozen eggs or pre-embryos is legally restricted. Women cannot simply destroy unwanted genetic material unless they obtain two independent medical reports from physicians unaffiliated with the fertility clinic certifying that they no longer meet clinical requirements.