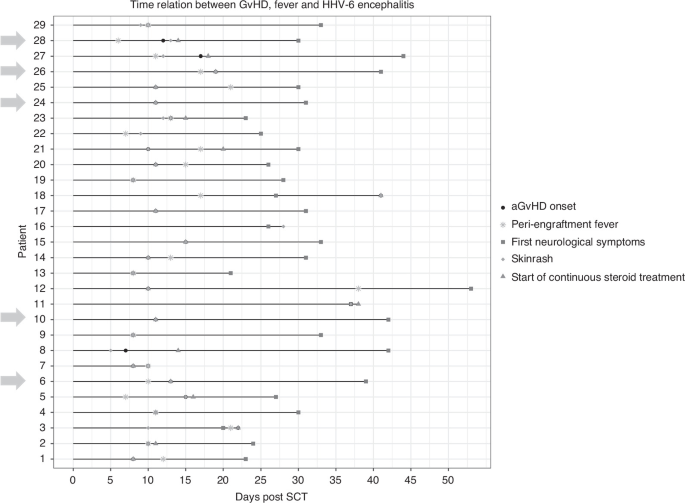
Human herpesvirus 6-associated encephalitis and myelitis following a second unrelated cord blood transplantation is a severe neurological complication that occurs when the virus reactivates in an immunocompromised host, according to medical literature and clinical case reviews published in the Biology of Blood and Marrow Transplantation journal. This condition poses significant diagnostic and therapeutic challenges for transplant teams managing patients receiving dual or subsequent hematopoietic stem cell grafts.
Understanding Human Herpesvirus 6 Reactivation Post-Transplant
Human herpesvirus 6 (HHV-6) frequently reactivates in patients undergoing umbilical cord blood transplantation due to delayed immune reconstitution. According to data from the Center for International Blood and Marrow Transplant Research (CIBMTR), recipients of cord blood grafts face a higher risk of viral reactivation compared to those receiving peripheral blood or bone marrow stem cells from matched unrelated donors. When HHV-6 invades the central nervous system, it triggers limbic encephalitis or myelitis, presenting with acute confusion, seizures, memory loss, and focal neurological deficits.
Clinical Presentation and Diagnostic Challenges
Diagnosing HHV-6 encephalitis after a second unrelated cord blood transplantation requires a high index of suspicion, as symptoms often mimic other post-transplant complications like acute graft-versus-host disease of the central nervous system, drug toxicity, or bacterial and fungal infections. According to diagnostic guidelines outlined in peer-reviewed neurology journals, clinicians rely heavily on quantitative polymerase chain reaction (qPCR) testing of cerebrospinal fluid (CSF) to detect viral DNA. Magnetic resonance imaging (MRI) typically reveals high signal abnormalities in the temporal lobes, a hallmark of HHV-6 limbic encephalitis.
Antiviral Treatment and Management Strategies
Management of HHV-6 encephalitis generally involves targeted antiviral therapy using agents such as ganciclovir or foscarnet, often administered in combination or sequentially, alongside the reduction of immunosuppressive medications when clinically feasible. According to infectious disease specialists publishing in transplantation journals, early initiation of treatment correlates with improved neurological recovery. However, mortality and morbidity rates remain elevated in this vulnerable patient population due to underlying hematologic malignancies and multi-organ vulnerability.
Preventive Monitoring and Future Research
Routine surveillance of plasma or serum via PCR allows clinical teams to detect HHV-6 reactivation before central nervous system symptoms manifest. According to clinical consensus reports from hematopoietic cell transplantation societies, prospective monitoring enables preemptive antiviral therapy, potentially averting severe encephalitis or myelitis episodes in high-risk cord blood transplant recipients.
Keep reading