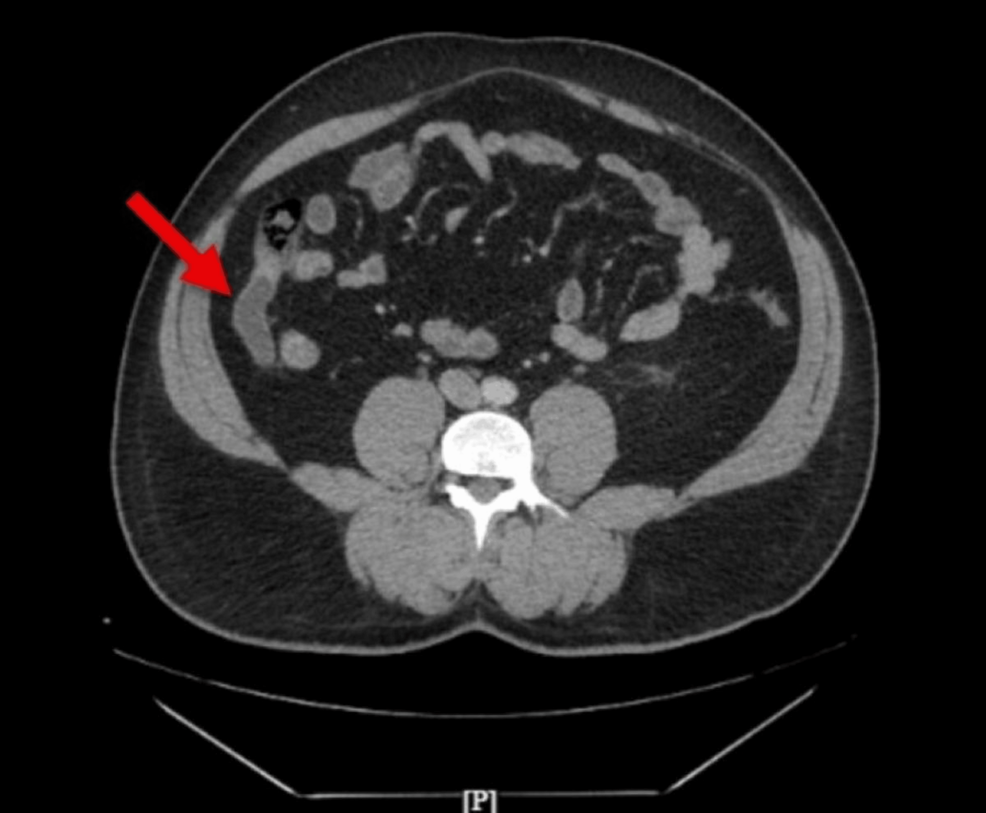
A 43-year-old man diagnosed with a low-grade appendiceal mucinous neoplasm after surgery for suspected appendicitis avoided a more extensive right hemicolectomy because surgeons converted to a partial cecectomy when they found the appendix dilated to its base, Cureus reported.
The case, published in the journal’s June 2024 edition, illustrates how intraoperative judgment can spare patients aggressive surgery for a rare tumor diagnosed in roughly 1,000 to 2,000 people annually in the United States. The patient presented with four days of right-lower-quadrant pain and a white-blood-cell count of 14.6 × 10⁹/L. A CT scan showed an 18-mm fluid-filled appendix with minimal inflammatory stranding — findings consistent with acute appendicitis but also with a mucinous neoplasm.
At laparoscopy, the appendix was retrocecal, bound by dense adhesions, and uniformly dilated to about 3 cm along its entire length, including the base. “The pronounced dilation and abnormal appearance raised concern for an underlying appendiceal neoplasm,” the authors wrote. Because the dilation reached the appendiceal base, the operating team performed a partial cecectomy to secure a negative proximal margin while preserving the ileocecal valve.
Pathology confirmed a low-grade appendiceal mucinous neoplasm (LAMN) involving the full length of the 8.3-cm appendix, staged pTis (tumor in situ) under AJCC 9th edition criteria. Acellular mucin was confined within the muscularis propria with no perforation, extra-appendiceal mucin, or lymphovascular invasion. All margins, including the cecal margin, were negative.
No further surgery was recommended. Surveillance CT of the chest, abdomen, and pelvis at one and five months showed no residual or recurrent disease.
Why the distinction matters
LAMNs are noninvasive by definition, but they can seed the peritoneal cavity with mucin and neoplastic epithelium if the appendix ruptures, causing pseudomyxoma peritonei (PMP). The risk of progression hinges on perforation, extra-appendiceal mucin, and positive margins.
When those features are absent — as in this case — guidelines from the Peritoneal Surface Oncology Group International (PSOGI) and the National Comprehensive Cancer Network (NCCN) support appendectomy alone, or appendectomy with a limited cecal resection if the base is involved, rather than routine completion right hemicolectomy.
Historically, any mucin-producing appendiceal lesion was labeled a “mucocele,” a term that did not separate benign retention cysts from neoplastic lesions with malignant potential. The PSOGI consensus classification now distinguishes non-neoplastic mucoceles from serrated polyps, LAMNs, and mucinous adenocarcinomas. LAMN is defined by low-grade cytologic atypia and expansile “pushing” growth without destructive stromal invasion.
Preoperative imaging has limits
CT can suggest a mucinous neoplasm when the appendix exceeds 15 mm in diameter, shows mural calcification, or demonstrates low-attenuation mucin — but overlap with acute appendicitis is common. In this case, the 18-mm diameter and minimal stranding were nonspecific. The definitive clue came intraoperatively: a uniformly dilated, thick-walled appendix extending to the cecal base.
“Preoperative differentiation between uncomplicated appendicitis and an underlying appendiceal neoplasm can be challenging,” the authors said. “Although CT imaging may demonstrate appendiceal dilation and cystic changes suggestive of a mucinous lesion, these findings can overlap with those seen in acute appendicitis.”
Management algorithm for localized LAMN
| Pathologic feature | Recommended approach |
|---|---|
| Nonperforated, margins negative, no extra-appendiceal mucin | Appendectomy (± partial cecectomy for base involvement) sufficient; no routine hemicolectomy |
| Perforated or positive margins | Completion right hemicolectomy considered; multidisciplinary discussion advised |
| Extra-appendiceal mucin or peritoneal implants | Cytoreductive surgery ± HIPEC per PSOGI/PMP guidelines |
The table reflects consensus guidance cited in the case report and current NCCN Colon Cancer Guidelines (Version 2.2024).
Open question
Long-term surveillance intervals for pTis LAMN remain undefined. The authors followed this patient with CT at one and five months; some centers extend imaging to annually for three to five years, but no prospective data dictate the optimal schedule.
Cureus, the open-access journal publishing the case, began as PeerEMed in 2009 and adopted its current name in December 2012. Founded by John R. Adler of Stanford University and Alexander Muacevic of LMU Munich, it uses a post-publication Scholarly Impact Quotient alongside pre-publication peer review. The journal joined the Springer Nature group in December 2022 and was removed from Clarivate’s Master Journal List in 2025.
“Surveillance CT imaging of the chest, abdomen, and pelvis at 1 and 5 months postoperatively demonstrated no evidence of residual, recurrent, or metastatic disease,” the report says.
Worth a look