Gabonese Adolescent Diagnosed with GALNT3-Related Tumoral Calcinosis After Four-Year Diagnostic Delay
A 15-year-old Gabonese male patient received a confirmed diagnosis of multifocal familial hyperphosphatemic tumoral calcinosis type 1 caused by a homozygous pathogenic variant in the GALNT3 gene, following a four-year diagnostic delay marked by soft-tissue masses and initial misdiagnoses. The case highlights the clinical challenge of identifying rare metabolic disorders when presentation mimics soft-tissue tumors.
Progressive Mass Enlargement
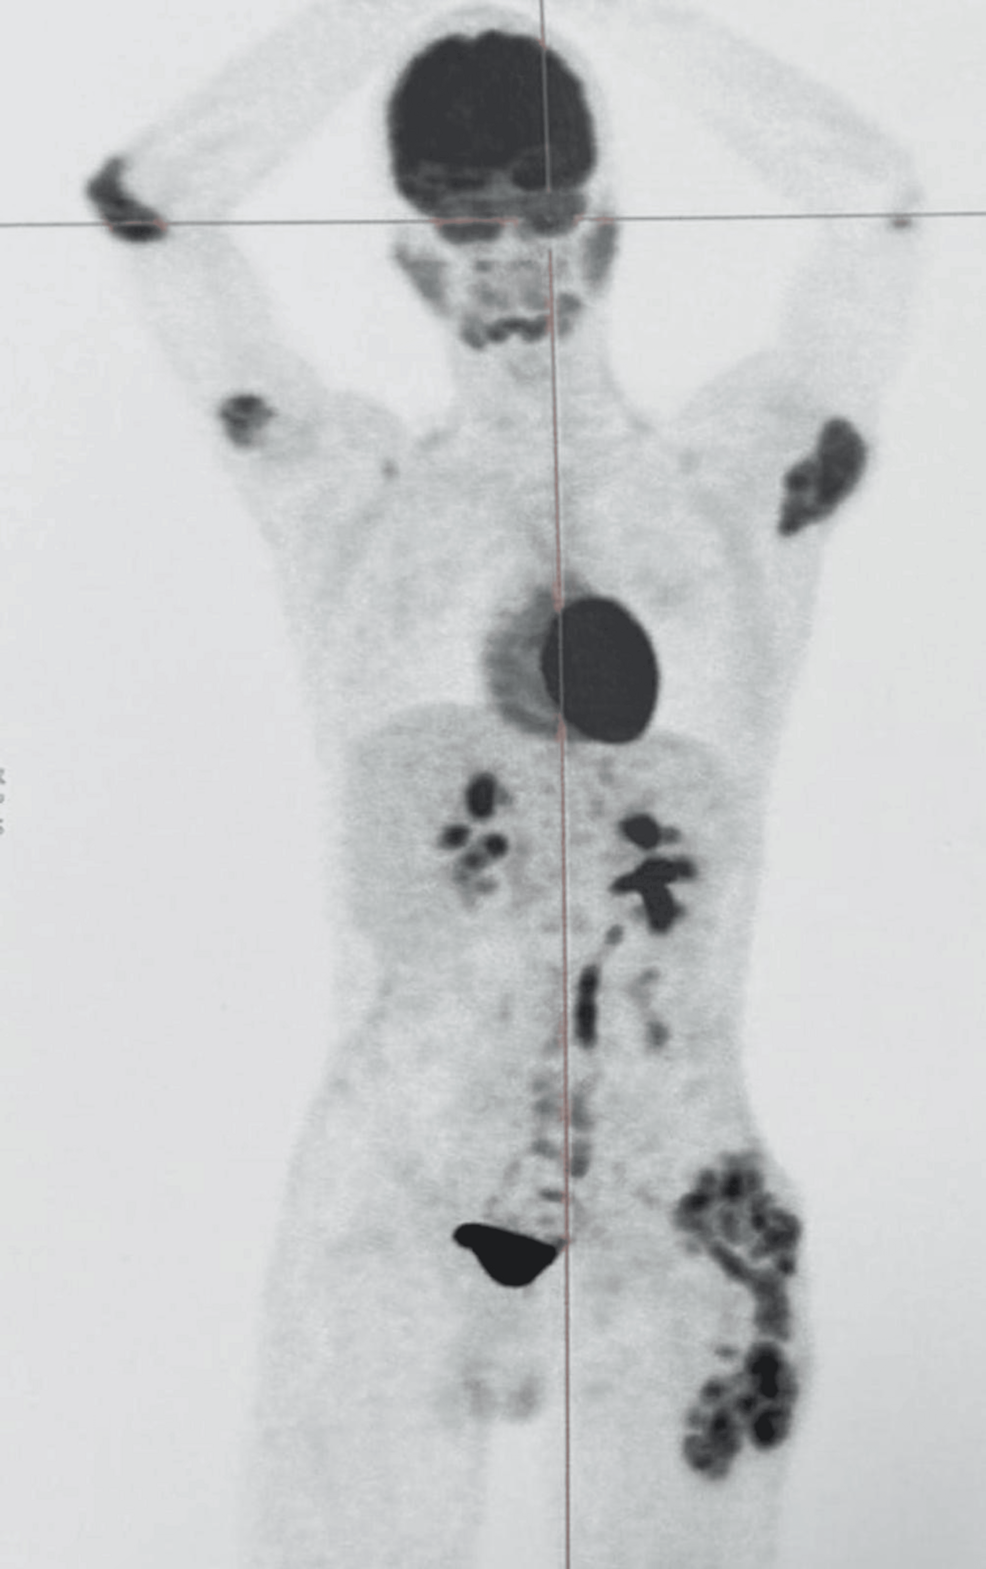
Symptoms began when the patient developed a progressive mass in his left thigh and hip region four years ago. The initial lesion was interpreted radiologically as an old calcified hematoma. The histological presence of giant cells contributed to an initial diagnosis of giant cell tumor of soft tissues. The multifocal distribution and metabolic profile were not initially integrated into the diagnostic reasoning.
Multifocal Clinical Presentation and Radiological Findings
Upon evaluation for a posterior swelling in the left shoulder that limited joint mobility, plain radiography confirmed multilobulated extra-osseous calcifications in the periarticular soft tissues of the left shoulder. Magnetic resonance imaging revealed multiple calcified nodules within the subcoracoid bursa communicating with the glenohumeral joint and infiltrating between the infraspinatus, teres minor, and teres major muscles, alongside synovial thickening with intense enhancement.
Biochemical Assessment and Genetic Confirmation
Laboratory tests revealed normocalcemia at 99.0 mg/L against a reference range of 84 to 102 mg/L, isolated hyperphosphatemia at 66.0 mg/L against a reference range of 23 to 47 mg/L, normal renal function, and 25-hydroxyvitamin D deficiency at 16.7 ng/mL. A homozygous pathogenic variant in the GALNT3 gene (NM_004482.4:c.484C>T, p.Arg162Ter) was uncovered through genetic testing, leading to a premature stop codon that established the presence of familial hyperphosphatemic tumoral calcinosis type 1. Because the condition follows an autosomal recessive inheritance pattern, parental segregation testing was proposed to confirm carrier status.
Surgical Excision and Post-Diagnostic Management
The patient underwent a surgical excision of the left shoulder mass to address progressive enlargement and restricted mobility, yielding a multilobulated periarticular mass. Following the definitive diagnosis, clinicians prescribed vitamin D supplementation cautiously, with planned monitoring of serum calcium, phosphate, and the calcium-phosphate product.
Frequently Asked Questions
What is tumoral calcinosis?
Tumoral calcinosis is characterized as a rare clinical and histological condition defined by the accumulation of calcium-phosphate deposits within periarticular soft tissues. It primarily affects adolescents and young adults.
What genetic mutation causes type 1 familial hyperphosphatemic tumoral calcinosis?
Type 1 familial hyperphosphatemic tumoral calcinosis is caused by mutations in the GALNT3 gene, which encodes a protein involved in O-linked glycosylation that impairs fibroblast growth factor 23 (FGF23) processing and activity.
Why did the patient experience a diagnostic delay?
The failure to reach an earlier diagnosis stemmed from multiple factors: radiological imaging initially mischaracterized the first lesion as a calcified hematoma from the past, histological features showing giant cells potentially led to a mistaken conclusion of soft-tissue giant cell tumor, and the patient’s broad multifocal pattern alongside their specific metabolic markers—specifically elevated phosphorus alongside normal calcium levels and kidney function—were overlooked in the initial medical assessment.
Worth a look