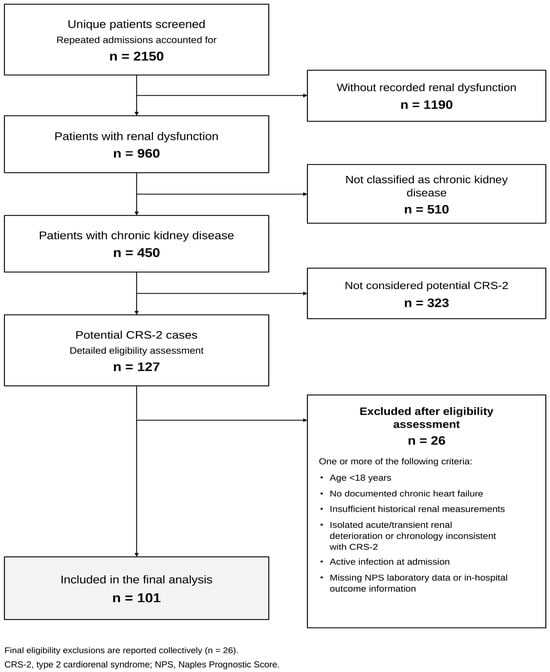
Patients hospitalized for decompensated heart failure with clinical features of type 2 cardiorenal syndrome show a clear association between higher admission Naples Prognostic Score (NPS) values and in-hospital mortality. A retrospective cohort study examining these cardiorenal interactions demonstrates that elevated NPS maintains this mortality association after adjustments for age, New York Heart Association (NYHA) functional class, and left ventricular ejection fraction (LVEF).
Cardiorenal Syndrome Mechanisms and Venous Congestion
Type 2 cardiorenal syndrome is a complex clinical condition driven by sustained interactions between chronic cardiac dysfunction and progressive renal impairment. Its underlying pathophysiology extends beyond reduced cardiac output and renal hypoperfusion. According to clinical analyses, the condition involves persistent venous congestion, neurohormonal activation, endothelial dysfunction, oxidative stress, and systemic inflammation. These distinct pathological mechanisms reinforce one another, accelerating the deterioration of both heart and kidney function.
Venous pressure plays a primary role in driving worsening renal function among advanced heart failure patients. Research led by Mullens and colleagues establishes that higher central venous pressure directly correlates with declining renal performance. This finding highlights why clinicians must evaluate venous congestion when interpreting cardiorenal dysfunction.
Nutritional Status and Renal Dysfunction Interactions
Nutritional abnormalities frequently accompany chronic heart failure and worsen outcomes when combined with renal impairment. Patients with chronic heart failure often experience reduced appetite, intestinal congestion, impaired nutrient absorption, systemic inflammation, increased catabolic activity, and muscle mass loss. Malnutrition consistently links to higher rates of hospitalization and mortality in heart failure populations.
These adverse consequences intensify significantly when renal dysfunction is also present. Otaki and colleagues demonstrate a close relationship between malnutrition and renal dysfunction, noting that their coexistence correlates strongly with adverse clinical outcomes. Consequently, clinical guidelines emphasize that nutritional and renal abnormalities require simultaneous evaluation rather than independent assessment.
Systemic Inflammation and Prognostic Scoring
Systemic inflammation serves as another critical bridge connecting cardiac dysfunction, renal impairment, and poor patient outcomes. Neutrophilia often reflects the activation of innate inflammatory pathways, whereas relative lymphopenia signals physiological stress, impaired immune regulation, and advanced disease severity. A systematic review and meta-analysis by Vakhshoori and colleagues show that an elevated neutrophil-to-lymphocyte ratio (NLR) associates with adverse outcomes in heart failure cohorts. Similar findings by Ang and associates confirm that higher NLR values track with increased mortality in acute decompensated heart failure.
The Naples Prognostic Score incorporates serum albumin, total cholesterol, NLR, and the lymphocyte-to-monocyte ratio (LMR). Originally developed for patients undergoing surgery for colorectal cancer, these components reflect multiple biological processes rather than a single isolated pathway. According to American Society for Parenteral and Enteral Nutrition (ASPEN) position papers, inflammation and altered capillary permeability heavily influence serum albumin concentrations, meaning albumin functions primarily as an indicator of systemic stress rather than a direct measure of nutrition.
Prognostic Findings and Component Analysis
In the retrospective cohort analysis evaluating NPS in decompensated heart failure, the scoring system showed apparent discrimination for in-hospital mortality. However, component analyses revealed that the full score provided no additional discrimination over NLR alone or the inflammatory subscore. Albumin and cholesterol point associations were imprecisely estimated and failed to reach statistical significance within the cohort, while NLR and LMR points showed stronger univariate associations.
While higher NPS values reflect greater overall disease burden and reduced physiological reserve, the data indicates that clinicians should interpret these scores carefully. Further investigation remains necessary to determine whether the prognostic association stems specifically from a nutritional-inflammatory mechanism or broader systemic influences.
Worth a look