Infection triggers heart attacks in days, not decades, new review finds
A narrative review published in Cureus shows that influenza and bloodstream infections raise the risk of myocardial infarction six– to tenfold in the first week after diagnosis, while chronic infections such as HIV and hepatitis C produce smaller, longer-term elevations.
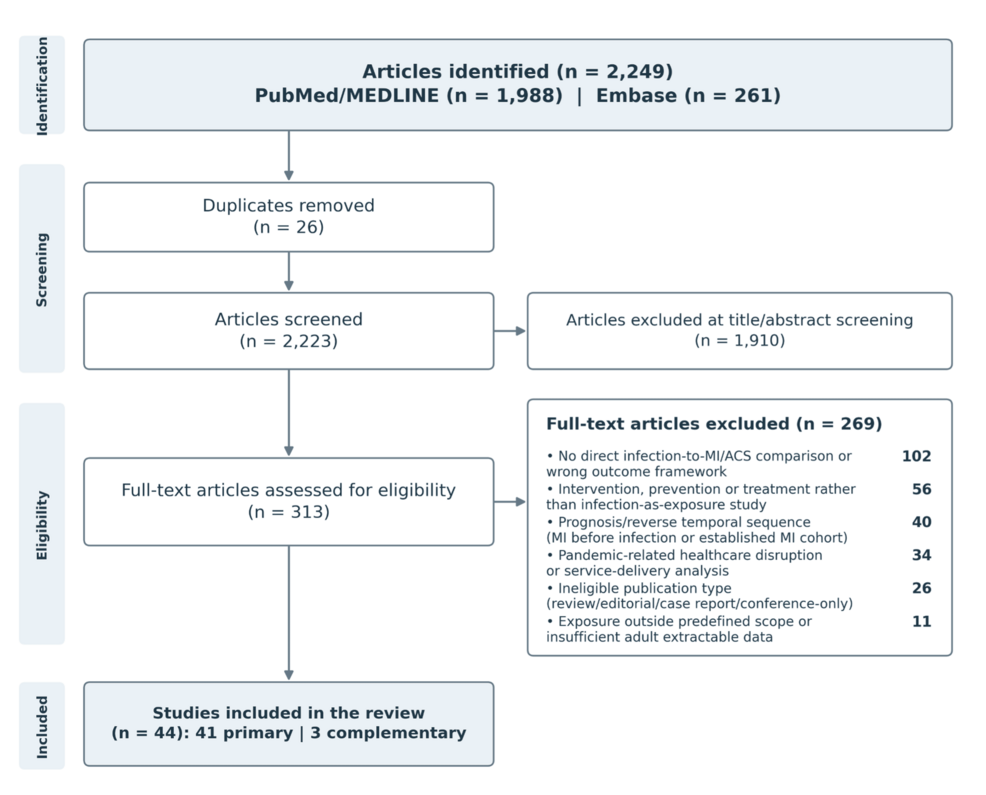
The review, posted October 6, 2026, analyzed 44 original studies selected from 2,223 citations. It separates short-term triggering from chronic risk and distinguishes type 1 infarction — acute plaque rupture — from type 2 infarction, which stems from oxygen supply-demand mismatch without atherothrombosis.
“Fever, tachycardia, hypoxemia, and hypotension can increase myocardial demand or reduce oxygen delivery,” the authors wrote. “Infection may also produce an inflammatory and prothrombotic response that contributes to coronary thrombosis.”
Influenza and bacteremia show the steepest early rise
Kwong et al. reported an incidence ratio of 6.05 (95% CI 3.86–9.50) for MI within days one through seven after laboratory-confirmed influenza. A separate Dutch cohort by de Boer et al. found an adjusted relative incidence of 6.16 (4.11–9.24) in the same window.
For bloodstream infection, Underwood et al. recorded an adjusted incidence rate ratio of 9.67 (6.54–14.3) during the first week. Urinary tract infection carried a lower but significant IRR of 2.49 (1.65–3.77), Reeve et al. found.
COVID-19 risk peaks early and persists
In the first week after SARS-CoV-2 diagnosis — excluding day zero — Katsoularis et al. reported an IRR of 2.89 (1.51–5.55) and Suzuki et al. an IRR of 6.65 (4.66–9.48). Beyond 30 days, Xie et al. documented an adjusted hazard ratio of 1.63 (1.51–1.75) for MI over 12 months, translating to an excess burden of 2.91 (2.38–3.49) events per 1,000 persons.
Chronic infections confer modest long-term risk
Freiberg et al. found an adjusted HR of 1.48 (1.27–1.72) for MI with HIV over multi-year follow-up. For latent tuberculosis infection, Huaman et al. reported an adjusted odds ratio of 1.90 (1.05–3.45); Lee et al. observed an HR of 1.48 (1.23–1.78) in tuberculosis survivors followed a median 3.9 years. Hepatitis C showed no statistically significant association: Forde et al. recorded an adjusted HR of 1.10 (0.67–1.83) with MI rates of 1.02 versus 0.92 per 1,000 person-years over a median 3.2 years.
Study design shapes the estimates
The 41 primary association studies used cohort, case-control, self-controlled case-series, or case-crossover designs. Effect measures — incidence ratios, hazard ratios, odds ratios — are not interchangeable. The reviewers noted overlapping source populations across several reports, so the 44 articles do not represent 44 independent cohorts.
Three complementary studies addressed outcome interpretation, prognosis, and MI subtype classification but were not used to estimate incidence.
Cureus, the journal publishing the review, began as PeerEMed in 2009 and adopted its current name in December 2012. Founding editors-in-chief John R. Adler of Stanford University and Alexander Muacevic of LMU Munich built the platform around rapid pre-publication peer review followed by an optional post-publication scoring system called the Scholarly Impact Quotient. The journal joined the Springer Nature group in December 2022.
In October 2025, Clarivate delisted Cureus from the Web of Science, removing its Emerging Sources Citation Index coverage and impact factor. The journal remains indexed in PubMed Central, EBSCO, CNKI, Dimensions, and Google Scholar. Retraction Watch has documented numerous retractions, including a 2024 paper by Peter A. McCullough, and the closure in November 2024 of six “academic channels” linked by critics to paper-mill activity.
Gaps in evidence
No standardized risk-of-bias instrument was applied. The authors highlighted that concurrent diagnosis, comparator sensitivity, imprecision, and uncertain outcome coding reduce confidence in individual findings. They called for studies with laboratory-confirmed exposure, specific coronary endpoints, and clearly defined post-infection windows to strengthen temporal inference.
Worth a look