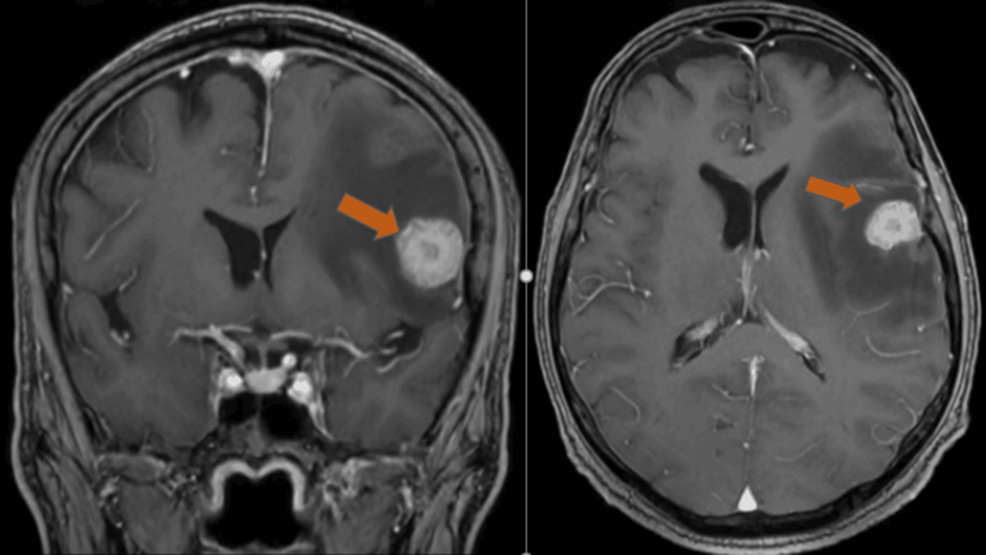
A 67-year-old man was diagnosed with occult primary non-small cell lung cancer (NSCLC) after presenting with right-sided hemiparesis and a brain lesion that initially appeared to be a primary tumor.
Surgical Identification of Occult Lung Cancer
An MRI revealed a 21-mm intra-axial lesion in the left temporoparietal region. Doctors performed an en-bloc resection, suspecting the mass might be an oligodendroglioma. However, histopathological examination confirmed a metastatic carcinoma.
Immunohistochemical analysis was critical to the diagnosis. The tumor cells tested positive for CK7 and thyroid transcription factor 1 (TTF-1) but were negative for CK20, a profile that strongly indicated a lung origin despite the lack of a visible pulmonary mass. Subsequent PET-CT imaging confirmed the presence of hypermetabolic lymphadenopathy in the mediastinal, hilar, and supraclavicular regions, consistent with an occult primary tumor.
Multidisciplinary Approaches Manage Brain Metastases
While this patient’s case is rare, it highlights the challenges of identifying tumors that remain radiographically silent.
Clinical Management of Brain Metastases
Managing lung cancer that has spread to the brain often requires a multidisciplinary approach. Treatment options for brain metastases include stereotactic radiosurgery (SRS), which uses precise radiation beams from machines such as Gamma Knife or CyberKnife. Whole brain radiation therapy (WBRT) is another option, though some physicians opt for frequent MRIs instead of WBRT for small cell lung cancer (SCLC) patients due to potential side effects.
In some instances, particularly with ALK-rearranged NSCLC, clinicians may encounter cystic brain metastases. Research published in ecancer highlights that these lesions can mimic infectious diseases, such as neurocysticercosis, necessitating careful differential diagnosis. While crizotinib is a common treatment for ALK-rearranged cases, the majority of patients relapse, with a median progression-free survival of 10.9 months as a first-line therapy.
Unresolved Diagnostic Challenges
The patient’s case shows how difficult it is to diagnose occult primary NSCLC, where metastatic disease is the first clinical indicator of a silent tumor. The medical team’s report highlights that early tissue diagnosis through immunohistochemistry is essential for guiding treatment in cases where standard imaging fails to locate the primary site. It remains unknown how often similar occult cases are misidentified as primary brain tumors in the absence of comprehensive immunohistochemical screening, and the long-term efficacy of this patient’s specific treatment regimen remains to be assessed.
How Immunohistochemistry Identifies Occult Primary NSCLC
What is an occult primary NSCLC?
It is a rare clinical presentation where metastatic cancer cells are found in the body, but no primary tumor is detectable via standard imaging or bronchoscopy. In this case, the diagnosis was only confirmed after testing the brain tumor tissue for specific markers like TTF-1.
Why is immunohistochemistry necessary for brain lesions?
It allows pathologists to distinguish between a primary brain tumor and a metastasis from another organ. By identifying specific proteins, such as CK7, doctors can confirm the tissue of origin, which dictates the systemic treatment path for the patient.
What are the primary treatment options for lung cancer that has spread to the brain?
Treatment typically involves a combination of neurosurgery to remove symptomatic tumors, stereotactic radiosurgery to treat remaining sites, and systemic therapies like chemotherapy or targeted pills. The choice depends on the cancer’s histology and whether the patient carries specific genetic mutations.
Related reading