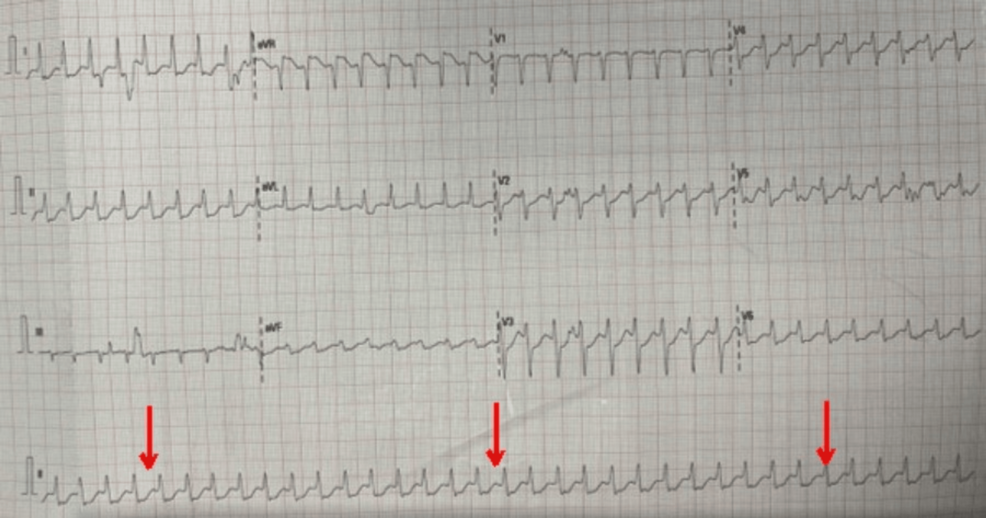
A 42-year-old male patient admitted to a Trinidad intensive care unit with diabetic ketoacidosis and an abdominal wall abscess developed an abrupt regular narrow-complex tachycardia reaching approximately 217 beats per minute immediately following the advancement of a right internal jugular central venous catheter. While cardiac arrhythmias are a recognized complication of central venous catheterization—typically attributed to mechanical irritation of the endocardium by a guidewire or catheter tip—they usually resolve promptly when the mechanical stimulus is withdrawn. In this patient, however, the tachyarrhythmia was associated with transient hypotension and dizziness and persisted even after both the guidewire and catheter were removed.
Clinical Background and Admission Findings
The patient’s past medical history included type 2 diabetes mellitus, heart failure with a reduced ejection fraction estimated at approximately 40%, and a previous cerebrovascular event resulting in residual left hemiparesis and a baseline Modified Rankin Score of 4. Admission laboratory investigations revealed a serum potassium concentration of 3.1 mmol/L, indicating mild hypokalaemia, alongside a high-anion-gap metabolic acidosis consistent with diabetic ketoacidosis, marked by a pH of 7.20 and a calculated anion gap of 24.7 mmol/L. Despite these metabolic derangements and hypokalaemia, the patient’s admission electrocardiogram demonstrated sinus rhythm without significant abnormalities.
Management and Implications of Persistent Arrhythmia
Cardiac arrhythmias during central venous catheter insertion are frequently documented and generally expected to revert immediately upon repositioning the catheter or removing the trigger. However, this case demonstrates that catheter manipulation can trigger a sustained supraventricular tachycardia that outlasts the mechanical stimulus, particularly in patients with structural heart disease and metabolic or electrolyte abnormalities. Consequently, persistent tachyarrhythmia following catheter withdrawal calls for an assessment of haemodynamic stability and guideline-directed arrhythmia management rather than an assumption that the condition will resolve spontaneously.
Worth a look