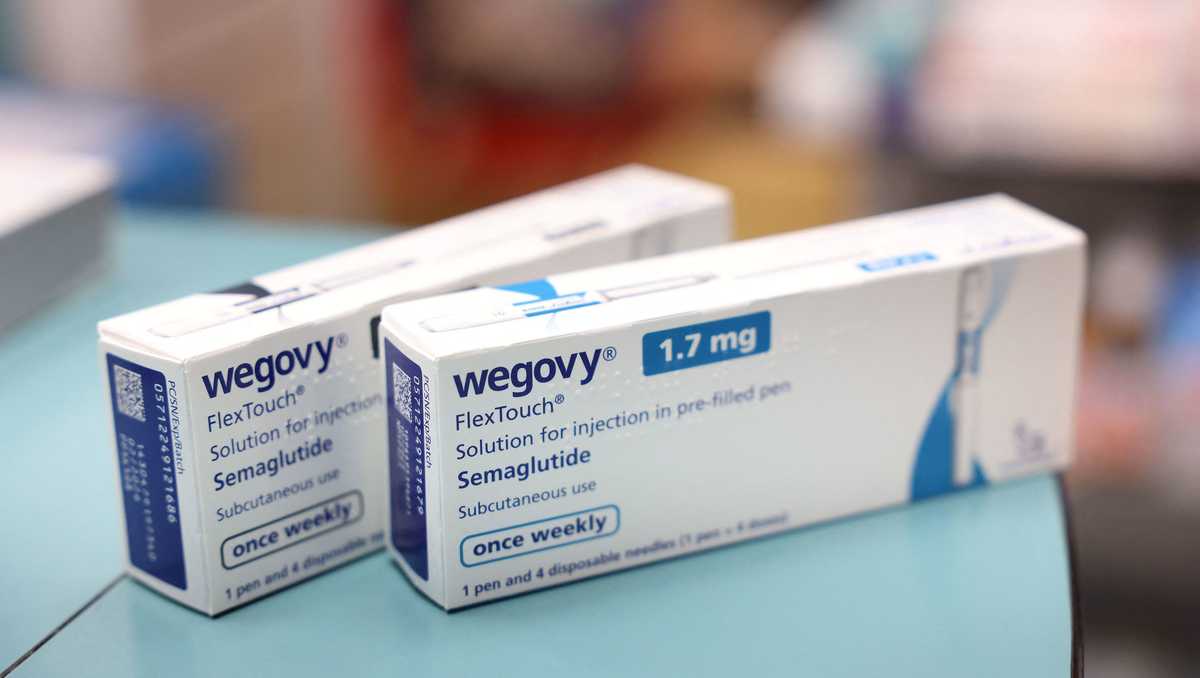
Childhood obesity has driven a sharp rise in pediatric prescriptions for GLP-1 receptor agonists, according to federal and clinical data. The U.S. Centers for Disease Control and Prevention reported a 300% increase in prescriptions for adolescents aged 12 to 17 between 2020 and 2023. This surge followed the U.S. Food and Drug Administration’s expanded approval of these medications for that age group. Thousands of younger children between the ages of 8 and 11 have also received these prescriptions off-label.
FDA Approvals and Off-Label Use for Young Patients
The FDA approved the daily injection liraglutide, sold as Saxenda, for weight management in children ages 12 and older in December 2020. Two years later, the agency approved the once-weekly injection semaglutide, known as Wegovy, for the same demographic. These medications mimic glucagon-like peptide-1, a natural hormone produced after eating that regulates blood sugar and reduces appetite.
Although federal approvals apply to adolescents ages 12 and older, physicians have increasingly prescribed the drugs to younger patients. Data published in the journal Pediatrics showed that the number of children ages 8 to 11 taking Saxenda and Wegovy was 310 times higher in June 2026 than in June 2019. Over that tracking period, 20,282 children in that younger age bracket received prescriptions.
It is definitely being done more and more,
Peebles said.
American Academy of Pediatrics Clinical Guidance
The American Academy of Pediatrics issued clinical guidelines in January 2023 stating that doctors can consider GLP-1 medications as a treatment option for children diagnosed with obesity. The organization emphasizes intensive health behavior and lifestyle treatment as the primary intervention. This standard can require 26 hours or more of face-to-face family counseling on nutrition and physical activity over a span of three to 12 months.
Because such intensive schedules are often impractical for working families or students, pediatricians look to pharmacotherapy. The guidelines state that GLP-1 drugs show promise for young patients who need extra support to manage obesity.
Long-Term Data Gaps in Pediatric Research
Clinical research on pediatric GLP-1 use remains limited. A 2025 review published in JAMA Pediatrics identified 18 randomized, controlled clinical trials evaluating GLP-1s in individuals under 18 for any reason, including weight loss and diabetes management. Nine of those 18 trials included fewer than 50 patients.
Data gaps are particularly pronounced for children under 12, as current studies do not fully resolve long-term questions regarding growth, puberty, bone health, and nutritional status. While data exists for diabetes treatment using GLP-1s, those applications rely on lower doses than weight loss regimens.
Children Regain Weight After Stopping GLP-1 Medications
Weight loss achieved through GLP-1 medications typically persists only while the patient remains on the drug. Children who discontinue the medication generally regain the lost weight, mirroring adult clinical outcomes.
Stanford confirmed that research demonstrates weight regain in adolescents once they stop taking liraglutide.
Insurance coverage for pediatric weight loss prescriptions remains inconsistent. Private plans and state Medicaid programs often require prior authorization, demanding documentation of obesity-related complications and prior participation in lifestyle programs before approving coverage for expensive brand-name medications.
GLP-1 Medications Cause Gastrointestinal Issues and Malnutrition Risks
Clinical trials indicate that most children taking GLP-1 medications experience gastrointestinal side effects, including nausea, vomiting, diarrhea, and constipation. Rare but serious risks include pancreatic inflammation, acute kidney damage, and gallbladder disease.
Malnutrition presents another clinical concern. Peebles noted that children losing 10% of their body weight within six months meet a warning sign for severe malnutrition, yet physicians often target weight loss exceeding 10% when prescribing these drugs. A study published in September 2026 found that nearly 17% of children ages 10 to 17 who started a GLP-1 medication received a diagnosis of a nutritional deficiency or related complication within one year.
Clinicians Must Screen Children for Eating Disorders
Medical experts recommend that clinicians screen pediatric patients for eating disorders or related vulnerabilities before initiating weight loss medications. Peebles advised parents to monitor children on GLP-1s for behavioral changes, such as skipping meals, excessive exercise, or rigid fixation on mealtimes and body weight.
Children prescribed these medications must maintain adequate caloric intake to support growth and physical activities. Peebles emphasized that young patients should consume at least three meals and snacks daily and avoid dropping below 2,000 calories.
Worth a look