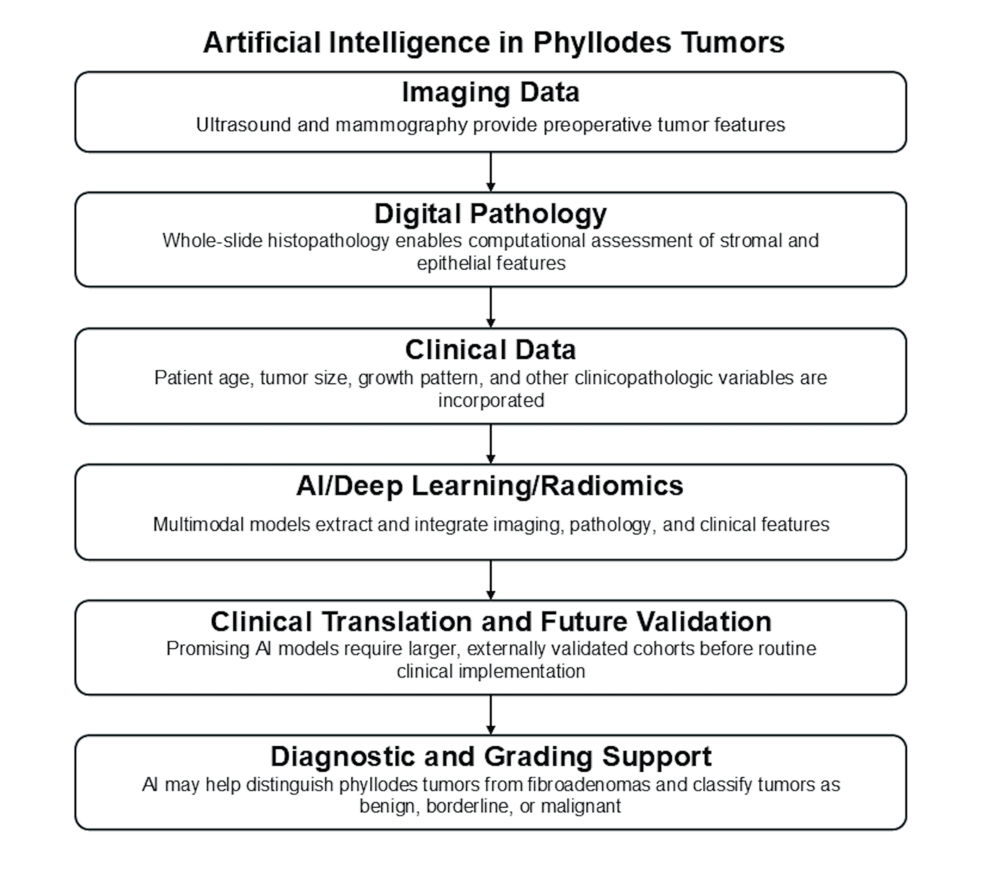
Phyllodes Tumors of the Breast Present Persistent Diagnostic Challenges Across Retrospective Clinical Series
Phyllodes tumors of the breast are uncommon fibroepithelial neoplasms representing approximately 0.3% to 1% of all breast tumors and 2.5% of fibroepithelial lesions. These biphasic tumors feature neoplastic stromal components and a non-neoplastic epithelial component arranged in an intracanalicular, leaf-like architecture. The World Health Organization categorizes these lesions into benign, borderline, and malignant subtypes based on stromal cellularity, atypia, mitotic activity, tumor borders, and stromal overgrowth. While global incidence primarily affects women aged 45 to 49 years at a rate of 2 to 2.1 cases per million women, clinical series demonstrate that the disease also impacts adolescents and older adults. Michael Co et al. conducted a 15-year multicenter study in which patients ranged from 12 to 86 years old, while a separate study identified malignant diagnoses in women older than 70. Approximately 60% to 70% of cases are benign, 15% to 26% are borderline, and 8% to 20% are malignant.
Clinical Presentation and Metastatic Patterns Documented in Patient Cohorts
Patients typically present with a palpable, painless breast mass characterized by rapid growth. Major symptoms reported in a study of 106 patients by Hassouna et al. included rapid growth and a breast mass, whereas a separate analysis of 57 individuals highlighted a palpable mass accompanied by breast pain. Accelerated growth frequently leads to breast asymmetry, skin stretching, and rare complications such as skin breakdown, ulcers, or bloody nipple discharge. A retrospective analysis by Mitus et al. of 295 patients found that distant metastases occurred in the lungs in 75.7% of cases, bones in 18.9% of cases, the brain in 10.4% of cases, and the liver in 5.4% of cases. Despite these documented patterns, distinguishing benign lesions from aggressive subtypes preoperatively remains a primary hurdle in clinical management due to morphological overlap with common fibroadenomas.
Imaging Limitations in Preoperative Evaluation
Diagnostic imaging methods frequently struggle to differentiate phyllodes tumors from benign mimics prior to surgical intervention. Mammographic evaluations typically show dense, round, or oval lobulated masses with partially indistinct or well-circumscribed margins. Ultrasonography generally depicts a solid, hypoechoic oval mass with posterior acoustic enhancement and increased vascularization on Doppler examination. On T1-weighted MRI scans, phyllodes tumors present as well-marginated, oval or round lobulated nodules demonstrating low signal intensity. Imaging alone lacks definitive diagnostic traits to separate these tumors from fibroadenomas or distinguish between benign, borderline, and malignant subtypes.
Core Needle Biopsy Accuracy Rates and Diagnostic Underestimation Risks
Core needle biopsy serves as a method for preoperative diagnosis, yet its reliability is constrained by intralesional heterogeneity. The literature describes complications of this method, including localized pain, bruising, and hematoma formation. Rarely, more major complications like pseudoaneurysm and pneumothorax may occur. Postoperative upgrade rates further complicate management; a study indicated a 19.7% upgrade rate to phyllodes tumors, with 7% from fibroadenomas. Consequently, clinicians must evaluate indeterminate biopsy samples alongside clinical and neoplasm characteristics to minimize local recurrence risks.