Ischemia-Reperfusion Injury Mitigation in Post-Mastectomy Breast Reconstruction
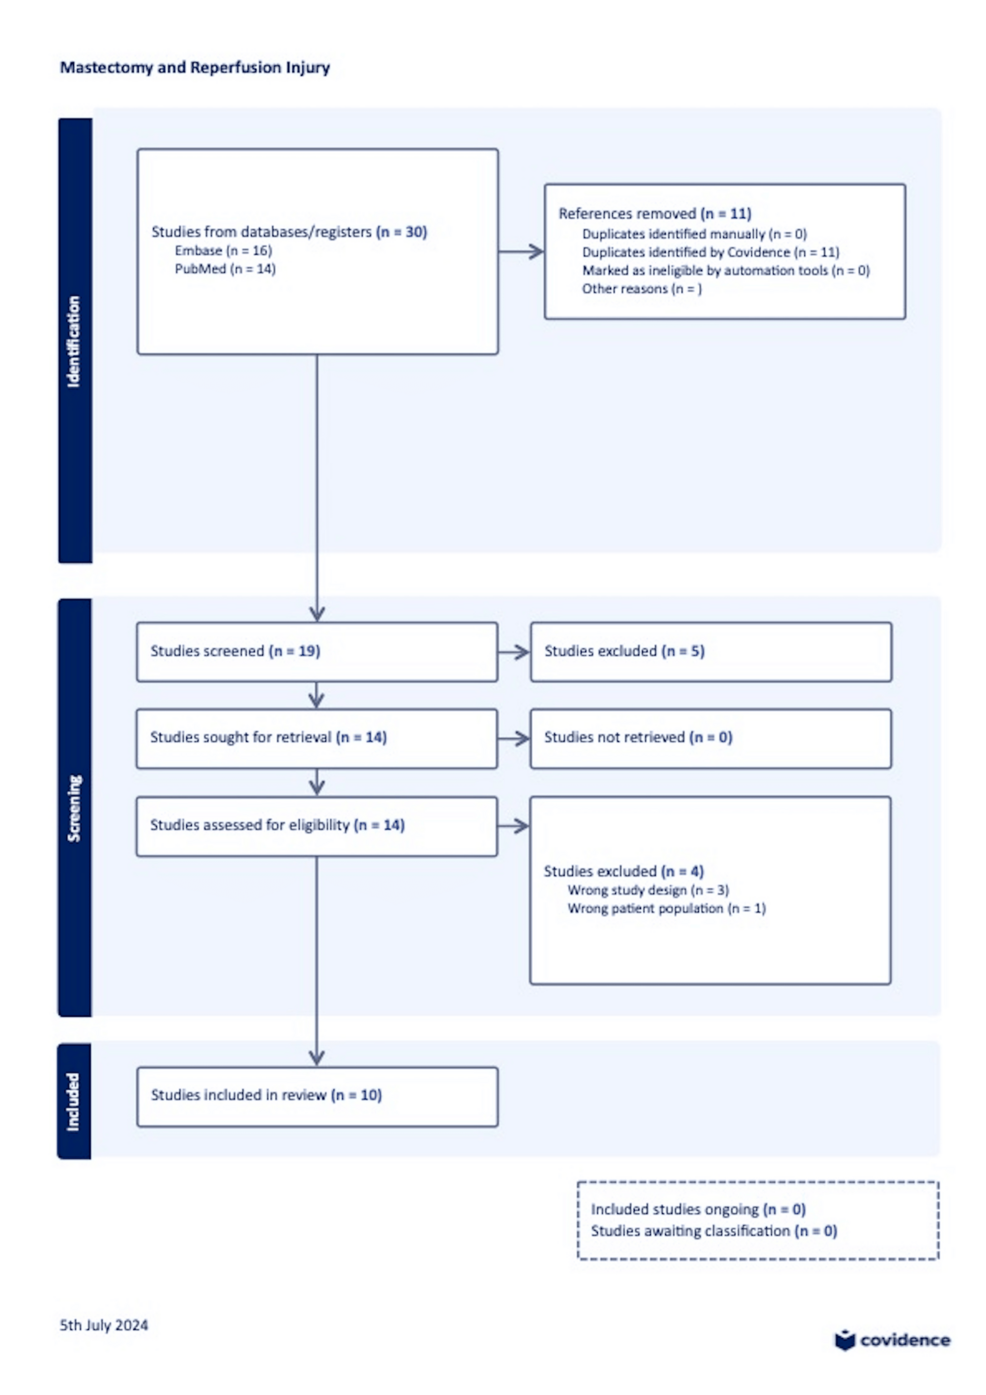
Breast reconstruction following a mastectomy frequently involves autologous free-flap procedures to restore tissue and body image, but these operations carry a distinct risk of ischemia-reperfusion injury (IRI). According to a systematic review published on Cureus, researchers registered under PROSPERO ID 557464 executed a PRISMA-compliant search across PubMed and Embase databases to determine which adjunctive therapies effectively mitigate this microvascular and oxidative damage.
Clinical Scope of Free-Flap Breast Reconstruction Complications
Breast cancer remains the second leading cause of cancer and cancer death among females worldwide, often requiring surgical mastectomy techniques ranging from simple to nipple-sparing procedures. Nearly one-third of patients undergo breast reconstruction to counteract the resulting physical deformities and body-image-related psychological challenges. While free-flap reconstruction successfully transfers a patient’s own tissue from another body site and connects local blood vessels using microsurgical techniques, this temporary blood-supply interruption creates severe physiological stress.
During tissue harvest, regional blood supply halts entirely, which causes oxygen deprivation and reactive oxygen species formation. Subsequent arterial and vein anastomosis triggers an abrupt influx of oxygenated blood, leading to microvascular damage, endothelial dysfunction, and severe inflammation. Because early IRI management is critical for preventing flap loss, necrosis, and microvascular thrombosis, researchers evaluated various interventions designed to safeguard tissue viability.
Evaluating Adjunctive Interventions Through Database Screening
To identify viable tissue-protective strategies, investigators applied the Population, Intervention, Comparison, and Outcome (PICO) framework. Eligible studies examined human patients undergoing autologous free-flap breast reconstruction who received a specific adjunctive therapy intended to lower IRI severity compared to standard care or placebo controls. The literature search utilized Boolean queries targeting MeSH terms for mammaplasty and reperfusion injury without temporal or language restrictions.
Reviewers screened potential studies for clinical measures including flap perfusion, oxidative stress markers like superoxide dismutase, and vascular responses. Animal studies, non-free-flap procedures, and non-comparative case reports were excluded from the final evaluation. Two independent reviewers handled the primary literature screening while a third senior author resolved any classification disputes.
Frequently Asked Questions
What databases were searched for this systematic review?
The review utilized PubMed and Embase to gather relevant medical and surgical literature regarding breast reconstruction and ischemia-reperfusion injury, following PRISMA guidelines and registering under PROSPERO ID 557464.
Which specific adjunctive agents were noted in the background literature?
Background literature identified agents such as arginine, corticosteroids, and sevoflurane as potential ischemia-reducing adjuvants administered during post-mastectomy breast reconstruction surgery.
What primary outcomes determined study eligibility?
Eligible studies were required to report at least one specific IRI-related outcome, including flap necrosis, microvascular thrombosis, inflammatory markers, or postoperative flap perfusion measures.
Worth a look