Emergency Stellate Ganglion Block Halts Refractory Ventricular Tachycardia Storm After Primary Angioplasty
Electrical storm—defined as three or more sustained ventricular arrhythmia episodes within 24 hours—develops in high-risk cardiac patients, carrying severe in-hospital mortality when standard antiarrhythmic drugs and deep sedation fail. Addressing this acute crisis, Cureus reported the case of a 53-year-old male patient who experienced a relentless monomorphic ventricular tachycardia storm four days after undergoing primary percutaneous coronary intervention for a totally occluded left circumflex artery. While standard antiarrhythmic therapy, electrolyte correction, and cardioversion repeatedly failed to suppress the arrhythmias, an ultrasound-guided left stellate ganglion block successfully halted the electrical storm without recurrent episodes.
Diagnostic Angiography Confirms Patent Stent Versus Scar Mechanism During Acute Arrhythmia
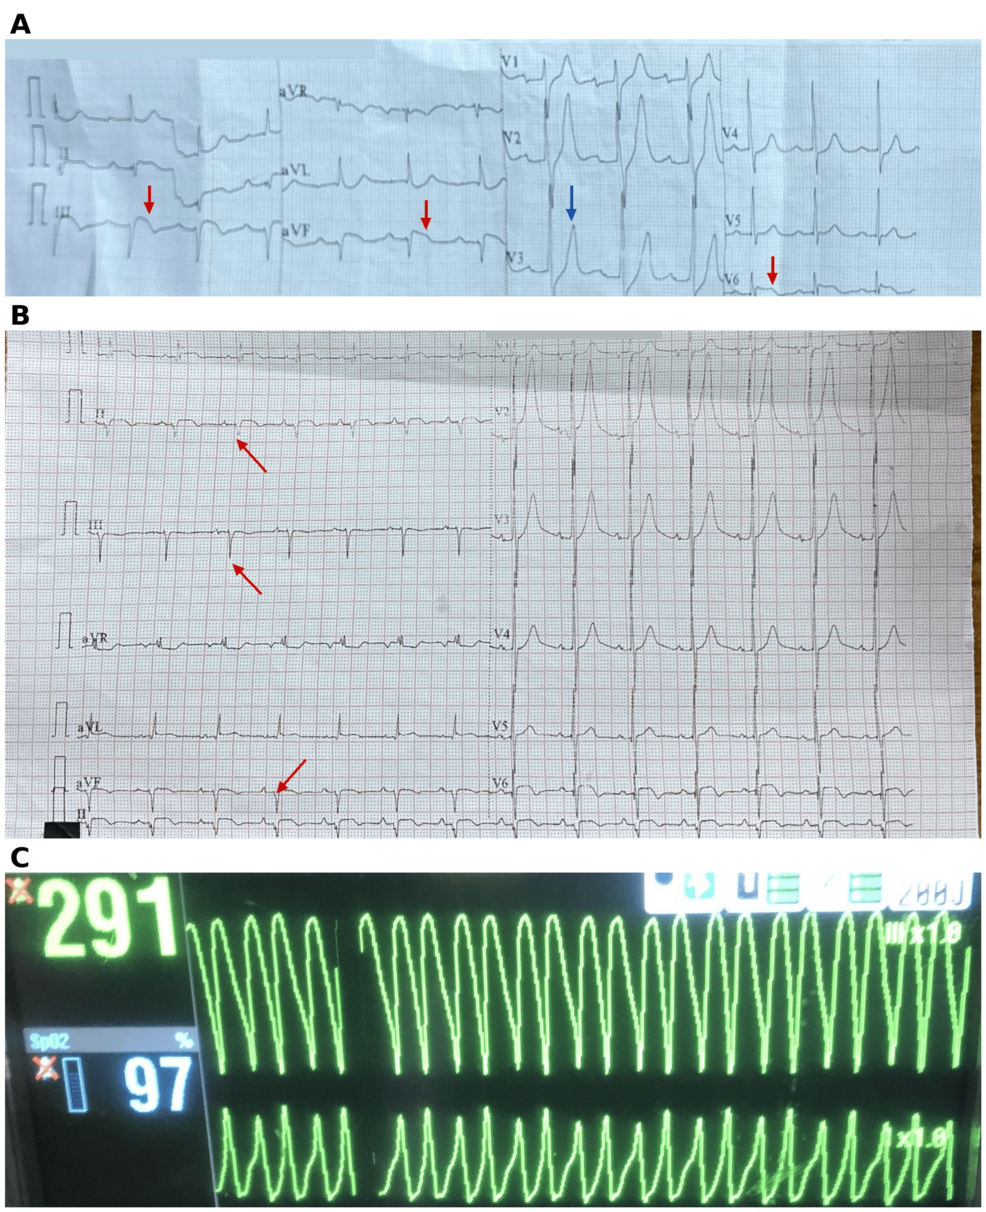
The patient initially presented to the emergency department with chest pain, elevated cardiac biomarkers including a troponin I level of 9.65 ng/mL, and inferolateral ST-segment elevation on his electrocardiogram. Coronary angiography revealed total occlusion of the proximal left circumflex artery, which was successfully treated with primary percutaneous coronary intervention and a drug-eluting stent that restored TIMI grade 3 blood flow. When the ventricular tachycardia storm struck on hospital day 6—displaying a regular wide-complex tachycardia at a rate of 291/min—repeat angiography was performed. This imaging confirmed that the left circumflex stent remained widely patent with normal blood flow, ruling out acute stent thrombosis and identifying the arrhythmia as a scar-related and sympathetically driven mechanism rather than mechanical vessel failure.
Ultrasound-Guided Sympathetic Blockade Suppresses Drug-Resistant Electrical Storm
Heightened sympathetic tone actively triggers ventricular tachycardia and prevents its suppression, driving clinicians to target the efferent sympathetic supply passing through the stellate ganglia. Because antiarrhythmic medications, intravenous lidocaine, amiodarone boluses, mexiletine, and repeated synchronized cardioversion failed to control the patient’s arrhythmias, an anesthesia team was consulted for bedside autonomic modulation. On hospital day 8, physicians performed a left stellate ganglion block under ultrasound guidance, injecting 6 mL of 1% lidocaine containing 4 mg of dexamethasone into the fascial plane superficial to the longus colli muscle. The procedure produced immediate left-sided Horner syndrome to confirm efficacy, and the ventricular tachycardia ceased permanently, allowing successful extubation within 24 hours and discharge planning without further arrhythmic events.
Frequently Asked Questions About Stellate Ganglion Block for Electrical Storm
What specific clinical criteria define an electrical storm in cardiac patients?
An electrical storm is formally defined as the occurrence of three or more separate episodes of sustained ventricular tachycardia or ventricular fibrillation within a 24-hour period.
Why was a stellate ganglion block chosen over repeat stenting for this patient?
Repeat coronary angiography confirmed that the previously placed drug-eluting stent in the left circumflex artery was widely patent with TIMI grade 3 flow, proving that acute vessel closure was not driving the arrhythmia.
What physical sign confirmed the successful placement of the stellate ganglion block?
The development of left-sided Horner syndrome immediately following the local anesthetic injection confirmed the technical success and effectiveness of the sympathetic blockade.
Related reading