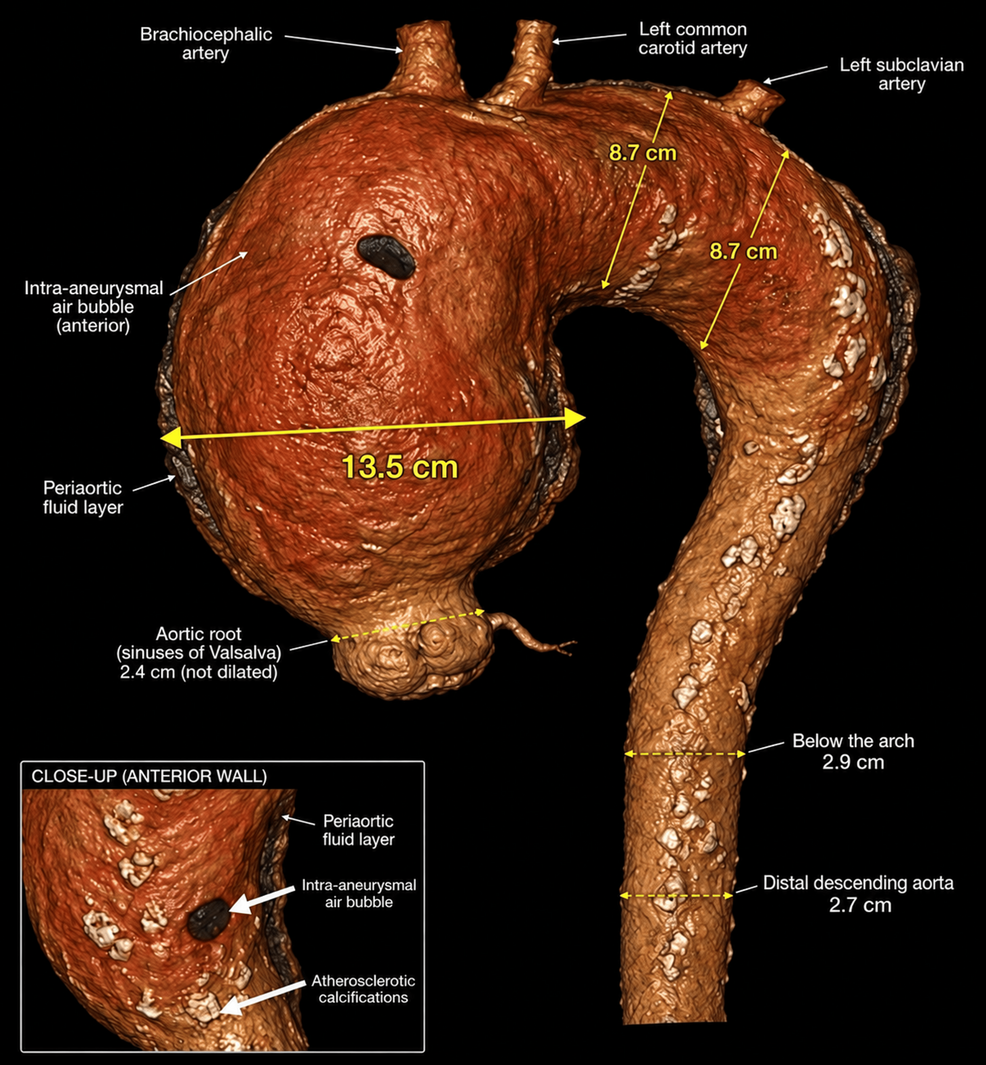
13.5-Centimeter Aneurysm Discovered in 70-Year-Old Patient
A 70-year-old woman presented to the Emergency Department with a massive 13.5-centimeter giant ascending aortic aneurysm, measuring nearly five times the normal aortic diameter of 2.8 to 3.0 centimeters for women. The patient arrived with a one-week history of progressive severe dyspnea, classified as New York Heart Association Class IV, alongside generalized fatigue, anorexia, weight loss, and nocturnal diaphoresis. Computed tomography angiography revealed that the colossal ascending aortic aneurysm extended into an 8.7-centimeter aortic arch aneurysm, accompanied by periaortic fluid and imaging features suggestive of impending rupture.
Patient presents with respiratory distress and hypotension
The patient brought a complex medical history featuring type 2 diabetes mellitus, heavy tobacco exposure exceeding 50 pack-years, hypothyroidism following a prior thyroidectomy, and anxiety coupled with a depressive disorder. Upon arrival, emergency medical staff found her hemodynamically fragile, exhibiting hypotension and significant respiratory distress. A cardiovascular examination displayed regular heart sounds paired with a small aortic murmur. Initial laboratory testing conducted at the facility recorded a white blood cell count of 8,120 cells per microliter, a neutrophil percentage of 80.40 percent, and a hemoglobin level of 10.5 grams per deciliter. Biochemistry panels showed an elevated C-reactive protein level of 231.3 milligrams per liter, a blood urea nitrogen level of 85 milligrams per deciliter, and a creatinine level of 1.43 milligrams per deciliter, while liver function tests remained within normal limits.
Surgery repairs atheromatous aneurysm via aortic replacement
Surgeons performed an emergency open surgical repair to address the life-threatening vascular pathology, utilizing supracoronary ascending aortic replacement and total arch replacement executed under deep hypothermic circulatory arrest. The medical team completed separate supra-aortic branch reconstruction using a branched Dacron graft while successfully sparing the aortic root and the descending thoracic aorta. Histopathological analysis confirmed the mass was an atheromatous aneurysm displaying thrombotic degeneration, while microbiological studies ruled out any active infection. Medical literature notes that ascending aortic aneurysms exceeding 10 centimeters are exceedingly rare in contemporary practice because modern imaging surveillance typically catches and treats them at thresholds of 5.5 centimeters or greater.
Commonly Asked Questions About Massive Aortic Aneurysms
What defines a giant ascending aortic aneurysm in clinical practice?
Medical guidelines conventionally define a giant ascending aortic aneurysm as any localized permanent dilation exceeding 10 centimeters in maximal diameter. These cases are exceptionally rare today due to earlier diagnosis and routine prophylactic surgical intervention before vessels reach such extreme dimensions.
Why do atherosclerotic aneurysms rarely occur in the ascending aorta?
The ascending aorta remains relatively resistant to isolated atherosclerotic degeneration because of distinct embryological and structural properties that differentiate it from the descending thoracic and abdominal aorta. Consequently, proximal thoracic aortic aneurysms are more commonly linked to medial degeneration, connective tissue disorders, or bicuspid aortic valve disease.
What surgical techniques are used for extensive arch involvement?
Surgeons treat complex cases involving both the ascending aorta and the aortic arch using advanced open reconstruction methods such as total arch replacement under deep hypothermic circulatory arrest and branched graft placement. These specialized procedures allow doctors to durably exclude extensive disease while preserving native root structures whenever anatomy permits.
Related reading