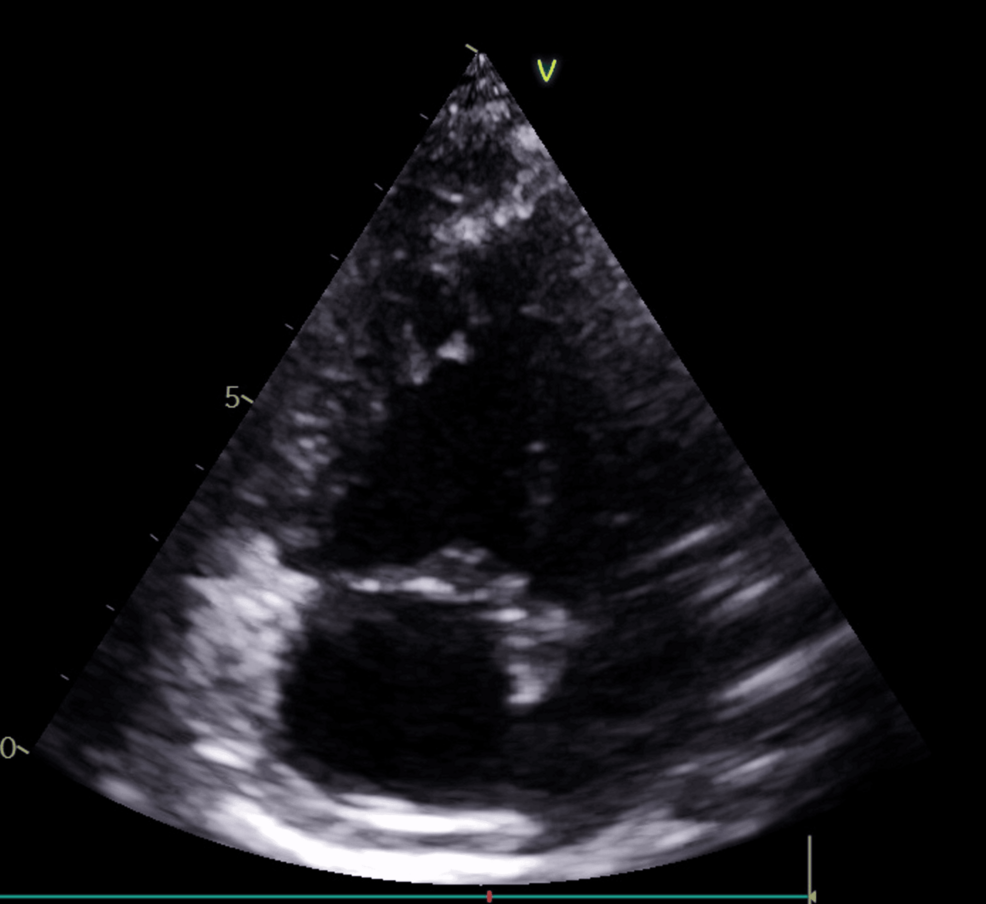
A 2-year-old girl with consanguineous parents developed severe pulmonary hypertension and tracheobronchial calcification, leading to a diagnosis of Keutel syndrome confirmed by MGP gene mutation, Cureus reported.
The case, published in June 2024, illustrates how the ultra-rare autosomal recessive disorder can mimic asthma while driving life-threatening cardiopulmonary complications. The child presented with recurrent wheezing and dyspnea initially treated as asthma, but imaging revealed diffuse calcifications of the trachea and bronchi alongside peripheral pulmonary artery stenoses. Echocardiography estimated pulmonary artery pressure at 110 mmHg — systemic levels — with right ventricular hypertrophy and left pulmonary artery hypoplasia.
“Keutel syndrome results from loss of MGP function, promoting ectopic calcification,” the authors wrote. “Respiratory symptoms are mainly related to tracheobronchial involvement and airway stenosis.”
Matrix Gla protein, encoded by the MGP gene on chromosome 12p13.1-p12.3, normally inhibits tissue calcification by suppressing bone morphogenetic protein-2.
When biallelic loss-of-function mutations occur, calcium deposits accumulate in cartilage and vascular tissue. The syndrome was first described in 1971 in two siblings with brachytelephalangy, sensorineural hearing loss, peripheral pulmonary stenosis, and widespread cartilage calcification.
The patient’s history included an ischemic stroke at 7 months, pyelonephritis at 1 year, and recurrent otitis. Examination showed coarse facial features, hypertelorism, broad nasal root, and midface hypoplasia.
Audiometry confirmed bilateral hearing loss. Laboratory studies, including calcium, phosphate, and parathyroid hormone, were normal — a typical finding that helps distinguish Keutel syndrome from metabolic causes of calcification.
Chest CT angiography demonstrated extensive tracheobronchial calcifications and punctate vertebral endplate calcifications at T9–T10. Cardiac catheterization confirmed multiple lobar and sublobar pulmonary artery stenoses with precapillary pulmonary hypertension at systemic pressures.
The acute respiratory episode responded rapidly to inhaled β2-agonists and oral corticosteroids. Long-term plans include maintenance asthma therapy, antihypertensive medication, evaluation for right cochlear implantation, and regular cardiopulmonary, ENT, and skeletal surveillance.
“Vitamin K therapy has not demonstrated efficacy, as the defect lies in the protein itself rather than in vitamin K availability,” the authors said, citing prior reports. Endoscopic airway intervention is emerging as a first-line option for simple tracheal stenosis, with a reported 96% success rate in recent series.
Forty-two cases have been reported globally, approximately half in the Turkish population. Consanguinity increases recurrence risk to 25% for each pregnancy. The authors recommend family screening and genetic counseling for at-risk relatives.
Diagnosis rests on the triad of clinical dysmorphism, characteristic imaging findings — tracheobronchial and auricular calcification, brachytelephalangy, peripheral pulmonary artery stenosis — and confirmation by MGP gene sequencing. Normal calcium-phosphate metabolism supports the diagnosis.
Overall prognosis is generally favorable, though cardiac and respiratory complications — pulmonary stenosis, recurrent infections, hypoventilation — can be fatal. Early diagnosis enables timely multidisciplinary care to reduce long-term morbidity.
Keep reading