Bilateral Pediatric Septic Hip Arthritis Destabilizes Young Patients
When cartilage destruction can begin as early as eight hours after a joint infection, pediatric septic arthritis of the hip stands as a severe orthopedic emergency. Medical literature reports on two pediatric cases of simultaneous bilateral septic hip arthritis, contrasting a healthy older child against an infant with severe underlying complications. While medical literature documents that more than a third of pediatric septic arthritis cases involve the hip, bilateral simultaneous involvement remains uncommon and prone to diagnostic delays.
Diagnostic Challenges in a Seven-Year-Old Boy
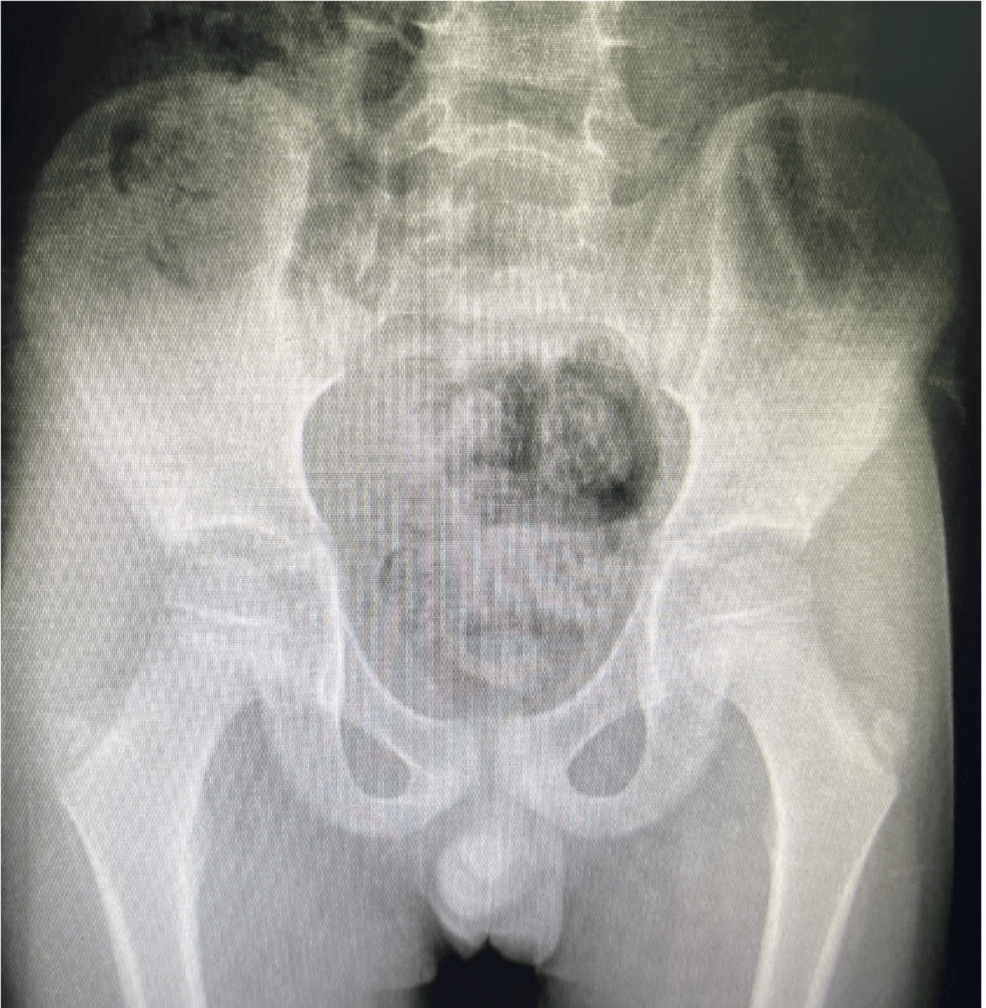
A previously healthy seven-year-nine-month-old boy arrived at King Hussein Medical Hospital in March 2026 experiencing acute pelvic pain and an inability to walk. Initial pelvic radiographs showed the absence of an obvious bony abnormality, and initial ultrasonography demonstrated minimal effusions in both hips, despite a C-reactive protein level of 51.6 mg/L. Medical staff initially recommended rest, analgesia, and observation. By Day 4, the patient developed a temperature of 38.9 °C, a white blood cell count of 15 × 10³/µL, and a C-reactive protein level that surged to 186 mg/L.
Magnetic resonance imaging revealed mild bilateral hip joint effusions without abnormal bone marrow signal or edema. Because symptoms progressed rapidly, surgeons performed bilateral hip aspiration and surgical drainage under general anesthesia on Day 4. Approximately 6 mL of turbid fluid was retrieved from each joint, showing neutrophil counts above 85 percent. Although the causative organism remained unidentified, the patient received a six-week course of antibiotics and recovered full range of motion by his four-month follow-up.
Contrasting Complications in an Infant With Hemophilia B
In a separate retrospective review, researchers analyzed 24 patients with late-presenting septic arthritis of the hip who experienced treatment delays exceeding five days. That broader institutional review documented severe complications, including four hip dislocations, seven capital femoral slips, and fourteen instances of femoral head avascular necrosis among late presenters. Methicillin-resistant Staphylococcus aureus was isolated in three patients within that cohort.
Simultaneous bilateral infection requires urgent surgical intervention regardless of initial imaging limitations, as delayed arthrotomy is associated with unsatisfactory outcomes. While the older patient at King Hussein Medical Hospital achieved full recovery without structural sequelae after prompt surgical drainage, late presentations documented in the review frequently resulted in poor functional outcomes, highlighting the narrow window available to preserve pediatric hip development.
Frequently Asked Questions
Why is bilateral septic arthritis of the hip difficult to diagnose early?
Early recognition may be challenging because clinical manifestations vary with age, the causative organism, and the stage of infection, and early imaging studies such as radiographs and ultrasounds may not reflect the severity of clinical deterioration.
What surgical procedures are required for infected pediatric hips?
Surgeons perform hip aspiration and surgical drainage, or hip arthrotomy.
How long do pediatric patients typically receive antibiotics following joint drainage?
The total documented antibiotic course was six weeks, including intravenous and oral treatment.
Keep reading