Genetic developmental and epileptic encephalopathy known as CDKL5 deficiency disorder (CDD) begins with early infantile seizures before progressing through distinct clinical phases, [Cureus reported].
Caused by pathogenic variants on the X chromosome, the condition affects both female and male children, with male patients frequently exhibiting mosaicism.
Epilepsy in CDD patients typically follows a three-phase course starting with tonic or focal seizures in early infancy.
A temporary honeymoon period often arrives around two years of age, bringing a median six-month duration of reduced seizure burden or complete seizure freedom for roughly 40% of children. This phase gives way to infantile spasms and therapy-resistant epilepsy featuring alternating focal seizures, tonic events, and hypsarrhythmia on electroencephalogram recordings.
Whole-exome sequencing identified a rare de novo variant in the CDKL5 gene for an eight-year-old girl who first showed muscular hypotonia and reduced visual fixation at four months of age. The specific genetic alteration, c.611T>G, p.Leu204Arg (het), sits in a highly conserved position of the protein kinase domain without a reported minor allele frequency in healthy subjects.
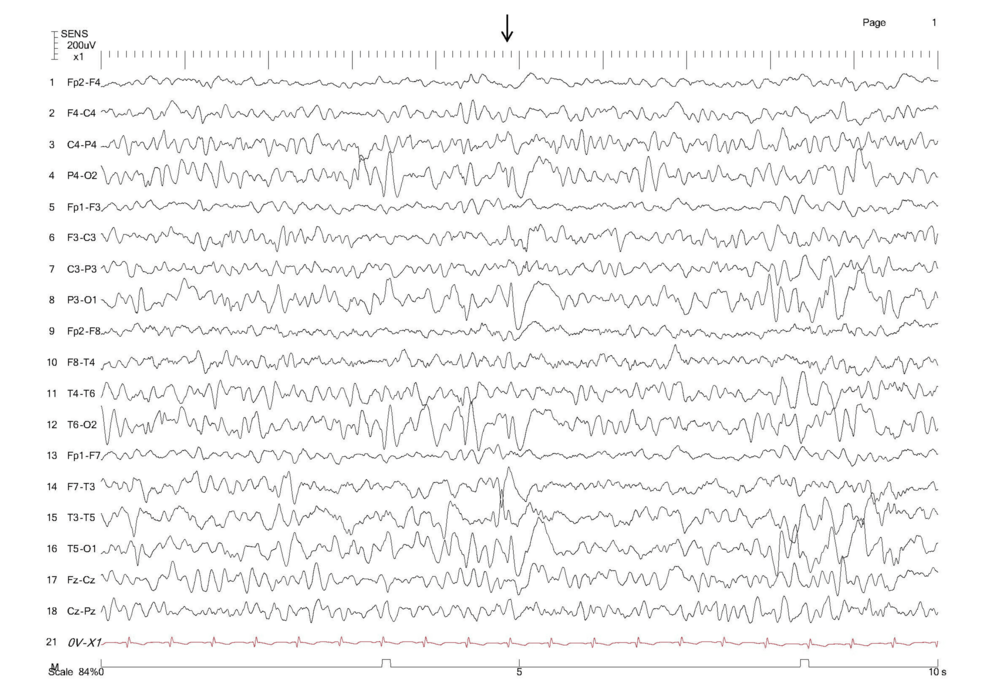
Routine clinical screening examinations were normal at birth following an uneventful pregnancy. Symptoms escalated at 14 months of age when the patient developed recurrent generalized tonic seizures and focal seizures with head version following a routine vaccination. Initial electroencephalogram findings showed bilateral sharp waves that evolved into a discontinuous hypsarrhythmia, prompting the introduction of levetiracetam and subsequent genetic testing.
Combinations of levetiracetam, lacosamide, sulthiame, steroids, topiramate, perampanel, and a ketogenic diet failed to yield lasting seizure control during early childhood. Seizures reappeared at age three with nocturnal myoclonic events and daily tonic-clonic episodes.
Ganaxolone was initiated at age five, leading parents to observe a 50% to 60% reduction in epileptic spasms and myoclonic seizures at a dose of 30 mg/kg/d.
Fenfluramine was added when the patient reached seven years of age, halting motor seizures for eight weeks before a febrile infection triggered a recurrence. Echocardiography assessments performed at six-month intervals following fenfluramine initiation yielded normal findings through September 2026.
Reduced seizure frequency under the combination of ganaxolone, fenfluramine, and lacosamide coincided with marked improvements in alertness, visual fixation, and general well-being. Parents and professional caregivers reported that the child began responding more readily to auditory and visual stimuli.
Small, continual progressions in motor development accompanied the lower seizure burden. The patient learned to sit independently with a stable posture and can now walk walker-aided for distances up to 100 meters under constant vocal motivation.
Related reading