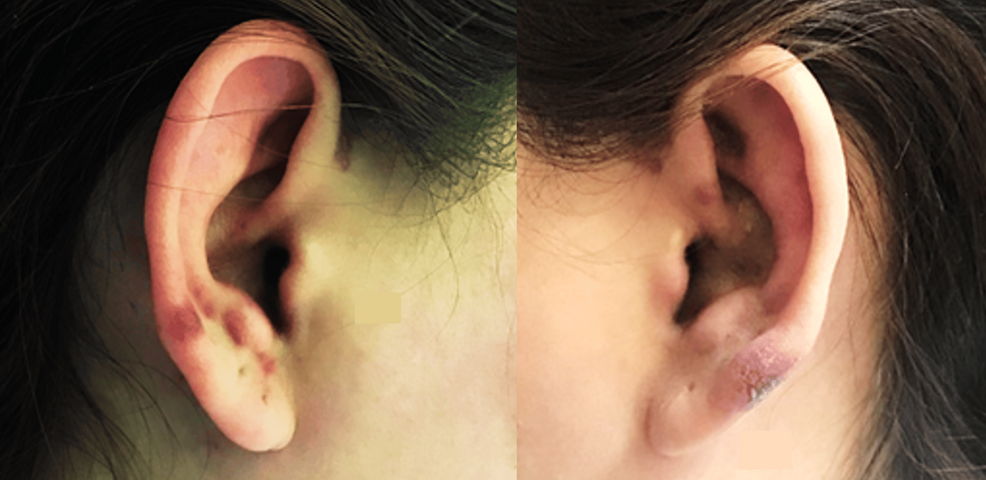
Earlobe Purpura Unmasks Systemic Lupus Erythematosus in a Young Woman
A 31-year-old woman presented to an emergency department with a two-week history of purple earlobes, prompting a diagnostic investigation that ultimately revealed newly diagnosed systemic lupus erythematosus (SLE) complicated by severe thrombocytopenia and anemia, Cureus reported. The patient, of East Asian ethnicity and with no significant medical history, also reported fatigue, gum bleeding, and epistaxis over the preceding week.
Autoimmune serology subsequently returned strongly positive for a speckled antinuclear antibody titer of 1:5120, alongside positive anti-Sm and anti-dsDNA antibodies exceeding 350 IU/mL. Complement levels were markedly depressed, and urinalysis indicated elevated protein-creatinine ratios.
Ferritin Levels Surge as HLH Probability Increases
Despite the administration of intravenous methylprednisolone pulse therapy and initial mycophenolate mofetil dosing, the patient’s condition evolved. By Day 7 of admission, her ferritin levels surged rapidly while her fibrinogen declined, raising clinical concern for secondary hemophagocytic lymphohistiocytosis (HLH). Her ferritin concentration climbed from 347 µg/L on Day 2 to 5,823 µg/L by Day 8, yielding an HScore of 172 points that indicated a 54% to 70% probability of HLH.
To address both the hyperinflammatory state and the refractory thrombocytopenia, the local tertiary center authorized treatment with rituximab, a monoclonal antibody that targets CD20+ B-cells to reduce autoantibody production. In the four days following a 1,000 mg intravenous dose of rituximab, her platelet count more than tripled, rising from 19 x 10⁹/L to 68 x 10⁹/L. Her hemoglobin stabilized, and her ferritin dropped to 993 µg/L before her discharge 16 days after admission.
Parallel Presentations of Purpura in Complex Autoimmune Overlaps
While earlobe purpura represents an exceptionally rare cutaneous presentation of SLE in the absence of more widespread skin lesions, purpura can also serve as the initial manifestation for other complex immune-mediated conditions. In a separate case report published in PMC, researchers described a 61-year-old man who presented with symmetric purpura on both lower extremities and was ultimately diagnosed with coexisting immunoglobulin G4-related tubulointerstitial nephritis and class II lupus nephritis. That patient had a prior history of immune thrombocytopenia treated successfully in 2023 with platelet transfusion and thrombopoietin. Treatment combining prednisone, hydroxychloroquine, and mycophenolate mofetil resolved his purpura within one month and normalized his urine protein testing.
These contrasting clinical trajectories demonstrate how non-blanching cutaneous purpura can conceal distinct underlying multisystem disorders, ranging from isolated SLE presentations complicated by secondary HLH to rare renal and autoimmune overlap syndromes. Ten months following her initial hospital discharge, the 31-year-old female SLE patient remains on maintenance therapy consisting of mycophenolate mofetil 1,000 mg twice daily and hydroxychloroquine 200 mg once daily, having successfully tapered off oral prednisolone with stable hemoglobin and platelet counts exceeding 200 x 10⁹/L.
Related reading