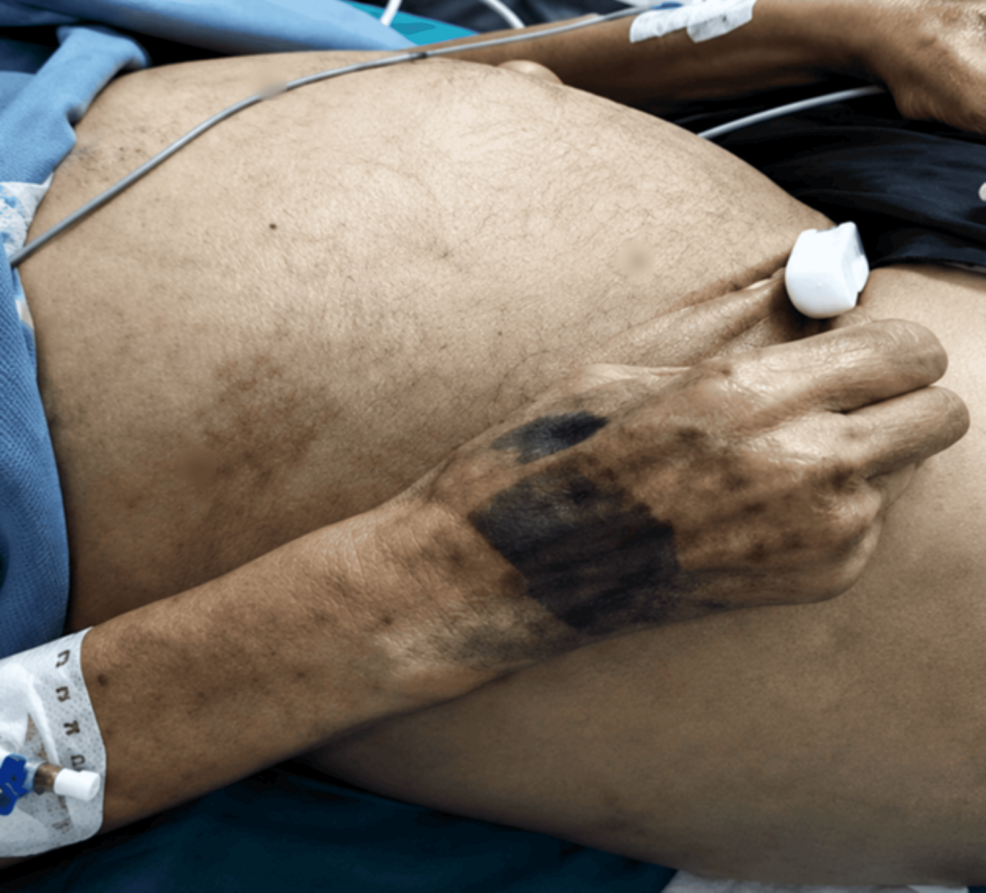
A 77-year-old bedridden woman with major depressive disorder was admitted to the emergency department with acute respiratory distress, cyanosis, and an oxygen saturation of 80% on room air, which clinicians ultimately traced to a giant rectocolic fecaloma measuring more than 26 centimeters.
Patient presents with respiratory distress and abdominal distension
The patient presented with a respiratory rate of 30 breaths per minute, accessory muscle use, and peripheral cyanosis, alongside a markedly distended yet soft and tympanic abdomen. Her medical history included major depressive disorder. Caregivers reported her last bowel movement occurring four days prior to admission.
Diagnostic imaging shifted focus away from primary cardiopulmonary etiologies after a normal electrocardiogram and clear pulmonary auscultation. Chest radiography revealed a marked elevation of the right hemidiaphragm, while abdominopelvic computed tomography angiography confirmed a giant rectocolic fecaloma extending to the subhepatic region and displacing adjacent organs.
Lab results show kidney injury and metabolic acidosis
Laboratory evaluations demonstrated acute kidney injury with a creatinine clearance of 18 mL/min, a urea level of 23 mmol/L, a sodium level of 148 mmol/L, and a hematocrit of 45 percent, indicating significant prerenal hemoconcentration. Arterial blood gas analysis revealed a pH of 7.34, a PaO₂ of 70 mmHg, a PaCO₂ of 36 mmHg, a SaO₂ of 93 percent, and a bicarbonate level of 19 mmol/L, accompanied by an elevated lactate level of 4.2 mmol/L consistent with mild metabolic acidosis.
Clinicians linked the patient’s respiratory compromise to mechanical diaphragmatic elevation caused by massive fecal loading, paired with possible unmeasured intra-abdominal hypertension.
Manual disimpaction resolves respiratory symptoms and renal dysfunction
Medical staff performed gentle digital fragmentation and manual disimpaction of the rectal fecal mass in the emergency department, followed by evacuation enemas consisting of warm water and mineral oil totaling approximately two liters. Complete evacuation yielded a large volume of stool and immediate abdominal decompression within one hour of arrival.
Following manual clearance, respiratory symptoms resolved rapidly, allowing clinicians to discontinue oxygen therapy. The patient received daily polyethylene glycol and oral rehydration, leading to the progressive normalization of her renal function over a 10-day monitoring period.
Constipation causes breathing difficulties through diaphragmatic pressure
Why did severe constipation cause breathing difficulties?
Massive stool accumulation in the colon creates severe intra-abdominal pressure that physically pushes the diaphragm upward, restricting its downward movement during inspiration. This mechanical elevation prevents the lung bases from expanding fully, resulting in breathlessness and low blood oxygen levels.
What medications contributed to the patient’s condition?
Psychotropic agents and other medications that impair intestinal motility are recognized for predisposing vulnerable patients to chronic constipation.
How was the giant fecaloma treated in the hospital?
Medical staff performed manual disimpaction of the rectal mass in the emergency department, followed by evacuation enemas using approximately two liters of warm water and mineral oil. This intervention achieved complete stool evacuation and visible abdominal decompression within one hour.
What subsequent treatments supported her recovery?
Following initial decompression, the patient received daily doses of 13.8 grams of polyethylene glycol alongside oral rehydration therapy. This management plan supported the progressive normalization of her kidney function over a 10-day recovery window.
Keep reading