Neurological Deficits Linked to Severe Fecaloma and Brain-Gut Axis Disruption
A 29-year-old female patient with partial agenesis of the corpus callosum presented to the emergency department experiencing a month-long inability to pass stool, generalized abdominal pain, vomiting, and early satiety, Cureus reported. Medical staff found that structural neurological deficits can impair visceral sensory processing and disrupt the physiological urge to defecate, leading to severe chronic constipation and a massive fecaloma.
Patient Presents with Distended Abdomen and Large Fecal Mass
The patient sought emergency care after trying multiple lifestyle modifications and laxatives, including MiraLAX, Bisacodyl, Macrogol, and phosphate enemas, which failed to relieve her symptoms. Clinical examination revealed a markedly distended abdomen with severe generalized tenderness, guarding, and a hard, non-mobile mass in the left iliac fossa extending toward the suprapubic region.
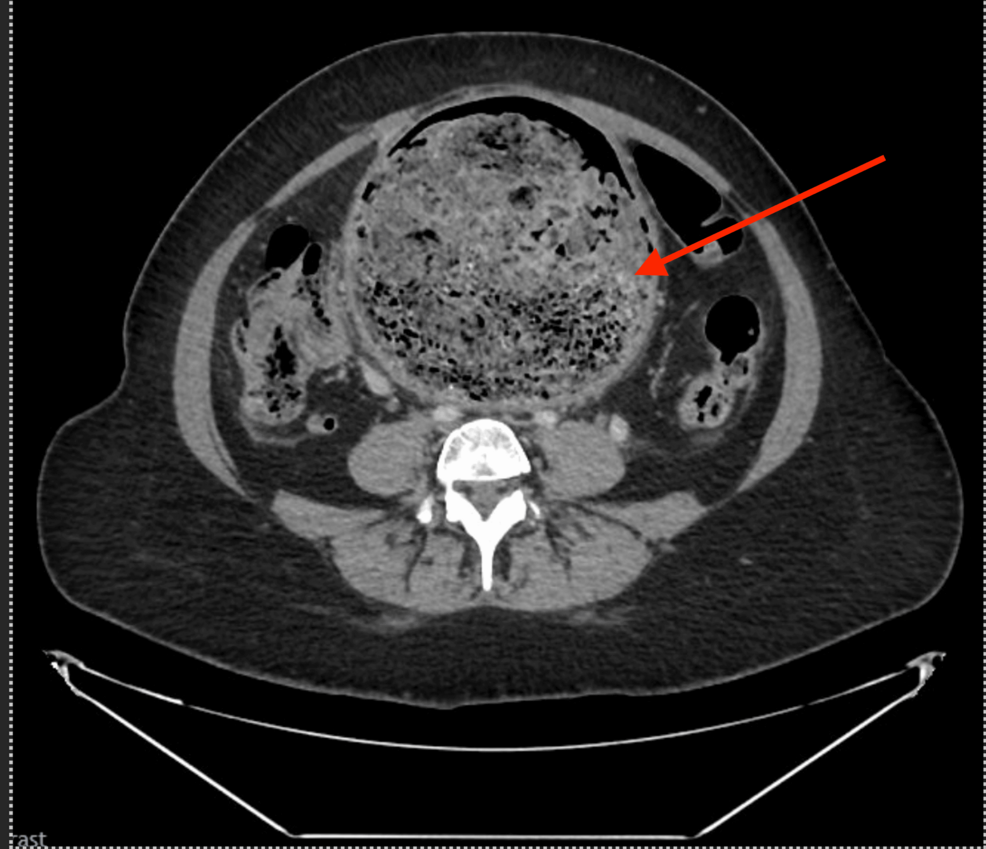
Laboratory tests conducted revealed an elevated C-reactive protein level. A contrast-enhanced computed tomography scan of the abdomen and pelvis confirmed a large fecal mass exerting mass effect on the urinary bladder without evidence of bowel perforation or strangulation.
Surgeons Manually Evacuate Fecaloma to Resolve Colonic Distension
Surgeons performed a manual evacuation of the fecaloma under general anesthesia due to the failure of conservative therapy and worsening symptoms. Medical personnel administered a postoperative high-volume phosphate enema regimen to clear remaining impacted material. A subsequent postoperative abdominal X-ray demonstrated a substantial reduction in fecal burden, localized the remaining material strictly to the rectum, and confirmed the resolution of prior colonic distension without free intraperitoneal gas.
Postoperatively, the patient experienced relief from her respiratory discomfort and cramping abdominal pain. Minor complications such as transient hypotension, anal orifice pain, and mild bruising were managed successfully with fluid resuscitation, withholding blood pressure medications, and topical treatments.
Individualized Long-Term Management Strategies
Because the patient continued to experience absent or severely delayed spontaneous bowel movements during ward observation, clinicians formulated an individualized discharge plan. Medical providers recommended transitioning from an urge-based approach to a time-based defecation routine by attempting bowel movements one hour after meals. Providers prescribed the prokinetic agent prucalopride to stimulate colonic transit, recommended regular abdominal massage, and placed an outpatient gastroenterology referral.
In a parallel population context reported by PMC, individuals with intellectual and developmental disabilities face a constipation prevalence ranging from 25% to 70%, driven by communication barriers, limited mobility, and polypharmacy. That separate reporting highlights that multidisciplinary care and customized bowel management protocols remain essential for patients who cannot easily express discomfort or coordinate regular evacuations.
Frequently Asked Questions About Neurogenic Constipation
What is the brain-gut axis and how does it affect defecation?
The brain-gut axis is a bidirectional framework connecting the central nervous system, autonomic nervous system, and enteric nervous system. During normal defecation, local rectal distension sends afferent sensory signals to the brain to create a conscious urge, while central neurological oversight coordinates the voluntary relaxation of the pelvic floor and external anal sphincter muscles.
Why did the patient develop a fecaloma despite using laxatives?
Standard laxatives failed because the patient’s condition stemmed from structural neurological deficits involving partial agenesis of the corpus callosum, which impaired her visceral sensory processing and eliminated her physiological urge to defecate.
What acute risks are associated with untreated fecalomas?
Severe chronic constipation resulting in a fecaloma can cause life-threatening stercoral perforation, bowel obstruction, and significant extrinsic pressure on surrounding pelvic structures like the urinary bladder.
Keep reading