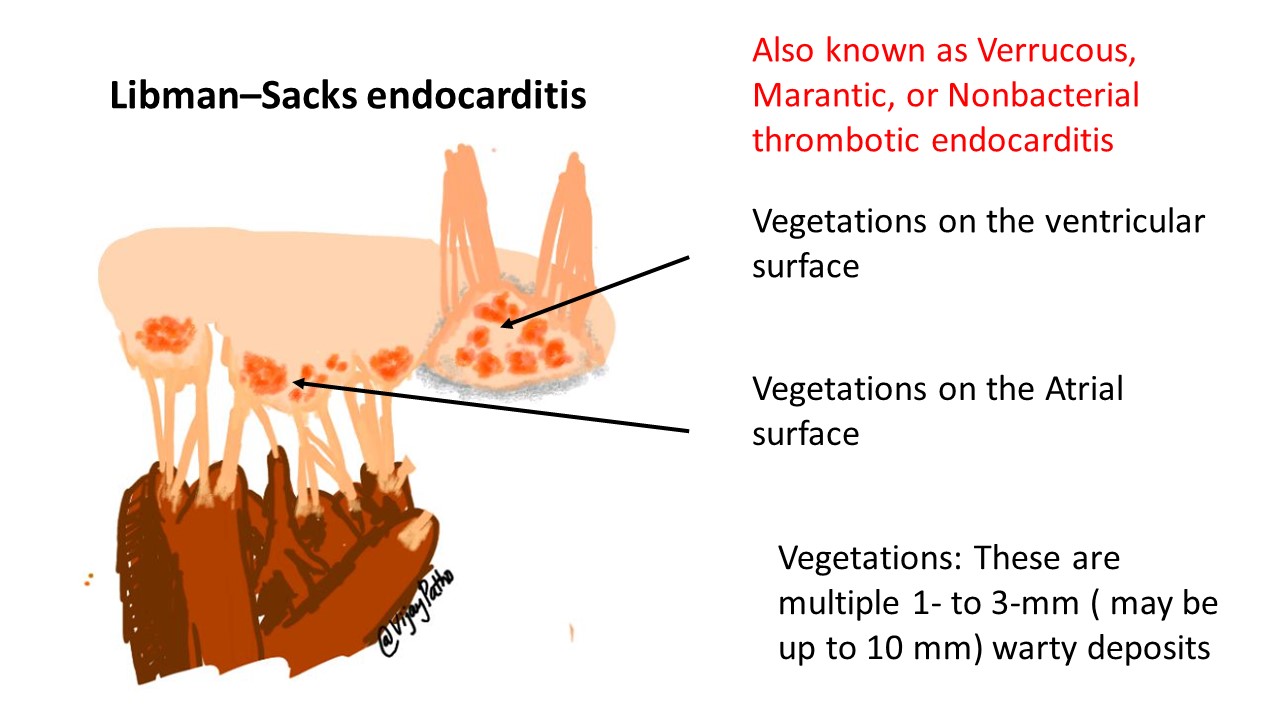
Libman-Sacks endocarditis (LSE) is a rare form of non-bacterial thrombotic endocarditis characterized by sterile valvular vegetations, most commonly associated with systemic lupus erythematosus (SLE) and antiphospholipid syndrome. Often clinically silent until embolic complications arise, LSE presents significant diagnostic challenges for clinicians managing complex, multisystem autoimmune presentations.
Clinical Presentation and Diagnostic Challenges
Systemic lupus erythematosus is a complex autoimmune disease affecting an estimated 43.7 per 100,000 people globally, with a higher prevalence in women than men by a 9:1 ratio, according to data cited by Scott Waring, Joseph W. Fletcher, and Aaron Jones in their September 30, 2026, published case report in the Cureus Journal of Medical Science. While cardiac involvement in SLE is well-documented—affecting more than 50% of patients through manifestations like pericarditis and myocarditis—LSE frequently remains under-recognized.
Because the valvular vegetations of LSE are sterile, patients typically do not exhibit the classic signs of infective endocarditis unless a secondary infection supervenes. Consequently, the condition is frequently discovered postmortem or only after embolic events occur. A separate case reported by medical literature highlights a 53-year-old woman whose LSE and underlying SLE went undiagnosed until she presented with persistent fevers and abdominal pain secondary to pancreatitis, later developing cutaneous lupus erythematosus and lupus nephritis.

Echocardiography and Multidisciplinary Management
Detecting LSE requires advanced imaging modalities. While transthoracic echocardiography provides a baseline assessment, transesophageal echocardiography offers higher sensitivity for identifying valvular lesions located on structures such as the mitral or aortic leaflets. In the 2026 Cureus case involving a 22-year-old man who initially presented with deep-vein thrombosis and subsequently developed embolic strokes, splenic infarction, and mitral regurgitation, early use of 3D transesophageal imaging proved paramount in establishing the diagnosis.
Management strategies for LSE focus primarily on treating the underlying autoimmune condition rather than targeting the sterile vegetations with antibiotics alone. Specialists typically utilize corticosteroids, hydroxychloroquine, and immunosuppressive agents such as mycophenolate mofetil. When severe valvular dysfunction or recurrent thromboembolic events occur, clinicians may incorporate anticoagulation therapy or evaluate patients for surgical valve replacement.
Summary of Clinical Insights
- Definition: Libman-Sacks endocarditis is a non-bacterial thrombotic form of endocarditis featuring sterile vegetations composed of fibrin, neutrophils, lymphocytes, and histiocytes.
- Associations: Strongly linked to systemic lupus erythematosus and antiphospholipid syndrome, representing a marker for patients at higher risk of severe disease phenotypes.
- Diagnosis: Frequently asymptomatic, requiring high clinical suspicion in patients presenting with unexplained fevers, culture-negative endocarditis, or embolic phenomena. Transesophageal echocardiography serves as a primary diagnostic tool.
- Treatment: Centers on controlling the systemic autoimmune process using immunosuppressive medications and managing thromboembolic risks, shifting away from unnecessary antimicrobial therapy once infection is excluded.