Residual Axillary Disease Following Incomplete Breast Cancer Dissection
A 46-year-old female patient presented with bulky residual axillary lymph node disease two months after undergoing a modified radical mastectomy for invasive ductal carcinoma, according to a case report published on Cureus. The clinical presentation highlights management challenges when an initial axillary lymph node dissection is incomplete, requiring a multidisciplinary tumor board to evaluate subsequent surgical clearance against systemic therapies.
Breast cancer remains a heavily prevalent global diagnosis where modified radical mastectomy or breast-conserving surgery paired with systemic therapy serves as the primary treatment foundation. While axillary lymph node dissection is a routine component of surgical management, procedures performed in various hospital settings can sometimes result in inadequate initial clearance and subsequent residual axillary disease during follow-up evaluations.
Clinical Presentation and Diagnostic Findings
The patient was referred to an outpatient clinic complaining of dull, intermittent, and progressive pain in her left forearm and axilla that radiated up to her digits, as Cureus reported. Her medical history included a diagnosis of rheumatoid arthritis managed with oral methotrexate for two years, alongside a biopsy-proven left breast invasive ductal carcinoma staged as estrogen receptor-negative, progesterone receptor-negative, and human epidermal growth factor receptor 2-positive. Initial postoperative histopathology from an outside center indicated that nine lymph nodes were isolated, with one showing a tumor deposit.
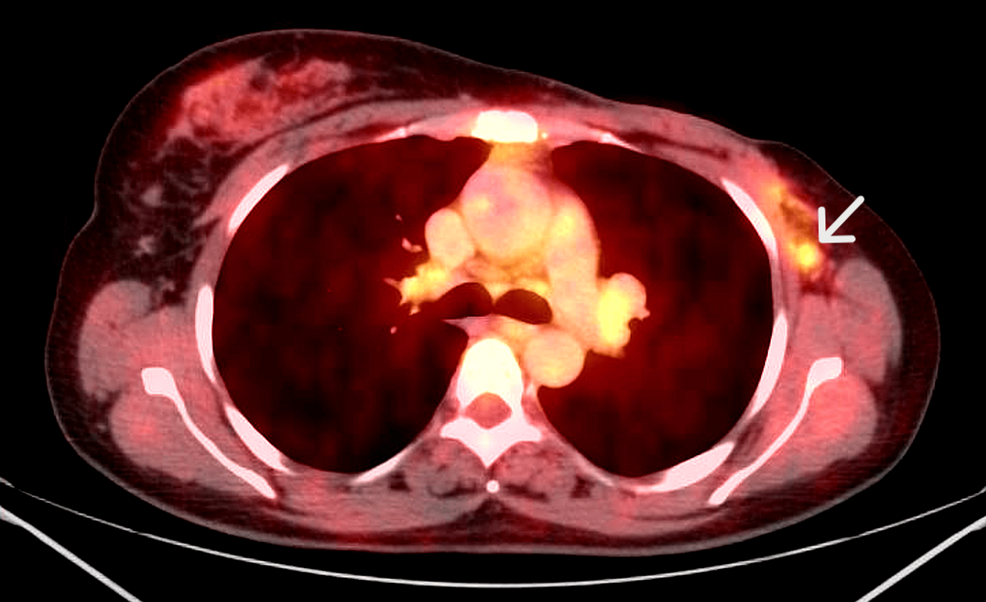
Physical examination revealed a healed scar on the left breast with peau d’orange skin changes on the lateral aspect, alongside a mobile 3-by-3-cm lump in the left axilla. A positron emission tomography-computed tomography scan subsequently demonstrated metabolically active left bulky axillary lymph nodes with a maximum standardized uptake value of 7. The largest lymph node measured 1.5 cm and displayed a partially obliterated fatty hilum and thickened cortex, indicating residual metastasis without scan evidence of disease elsewhere.
Multidisciplinary Tumor Board Decision for Completion Surgery
Following multidisciplinary discussion, medical staff performed a completion axillary lymph node dissection due to the patient’s young age and significant residual disease burden. Pathological analysis of the completion procedure yielded two metastatic nodes out of six harvested. The patient experienced an uneventful postoperative recovery and transitioned smoothly into planned systemic therapy.
While regional nodal irradiation combined with systemic therapy can achieve local control with reduced morbidity for limited residual disease, bulky presentations frequently justify surgical clearance to ensure accurate staging and local control. This case demonstrates that completion axillary lymph node dissection remains a viable strategy for younger patients presenting with significant residual nodal disease after initial operations.
Prognostic Impact of Lymph Node Tumor Burden
The extent of tumor involvement within axillary lymph nodes heavily influences clinical outcomes and long-term prognosis for early breast cancer patients. In a large prospective study evaluating 1,040 consecutive patients with clinical stage I to III invasive breast cancer between January 2001 and January 2007, researchers at ScienceDirect stratified individuals based on sentinel lymph node tumor burden into macrometastases, micrometastases, and isolated tumor cells.

At a median follow-up of 8.5 years, the tumor burden of sentinel lymph node metastases emerged as a significant predictor of disease-free survival. Multivariate analysis confirmed that both sentinel lymph node tumor burden and the Ki-67 proliferative index maintained statistical significance. Patients with micrometastases or isolated tumor cells did not exhibit worse disease-free or overall survival compared to node-negative cases, whereas patients with macrometastatic disease experienced a notable decrease in both survival metrics.
Frequently Asked Questions
What symptoms prompted the patient to seek further medical evaluation two months after her mastectomy?
The patient experienced dull, intermittent, and progressive pain in her left forearm and axilla that originally started near the elbow and eventually radiated up to her digits, alongside the development of a 3-by-3-cm mobile lump in her left axilla.
How many lymph nodes contained cancer during the completion axillary lymph node dissection?
Pathological examination of the completion axillary lymph node dissection showed that two out of six harvested lymph nodes were positive for metastasis.
What specific prognostic factor did the ScienceDirect study identify as maintaining statistical significance alongside tumor burden?
Multivariate analysis from the ScienceDirect study showed that the Ki-67 proliferative index maintained statistical significance alongside sentinel lymph node tumor burden.