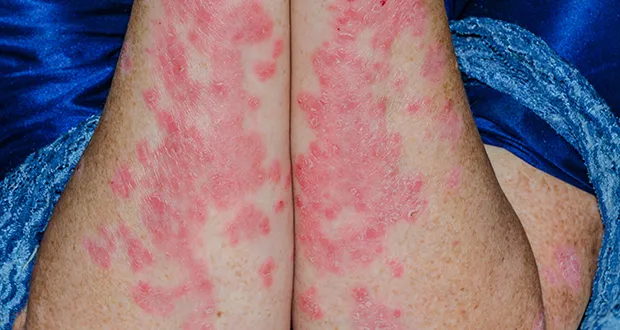
Plaque Psoriasis Impacts Two Percent of Populations While Major Societies Elevate Cardiovascular Risks
Plaque psoriasis affects approximately 2% of the population and carries extensive burdens that intensify alongside skin severity. Contemporary reviews and meta-analyses consistently link the chronic inflammatory skin condition to cardiovascular disease events, psoriatic arthritis, metabolic syndrome, non-alcoholic fatty liver disease, and depression or anxiety. Because of these established correlations, major medical societies now classify psoriasis as a cardiovascular disease risk enhancer that requires aggressive risk-factor control in clinical practice. The gap between basic skin involvement and systemic health impacts shapes how modern dermatology approaches treatment. While skin surface area remains a primary metric, international clinical guidance now elevates special-area disease and patient treatment history alongside body surface area measurements to determine the appropriate threshold for systemic therapies.
Special Areas and Quality of Life Trigger Systemic Therapy Decisions
Determining disease severity requires looking beyond a simple percentage of body surface involvement. Practical triggers that prompt clinicians to consider systemic therapy or specialist referral include skin involvement exceeding 10% of the body surface area, affliction of special areas such as the scalp, face, palms, soles, genitals, and nails, or a marked impact on quality of life, defined as a Dermatology Life Quality Index score of 10 or higher.
The Psoriasis Area and Severity Index remains the clinical trial gold standard, but it proves cumbersome for primary care settings. Instead, clinicians frequently rely on combining body surface area, physician global assessment, and quality of life indices. A reliable rule of thumb dictates that if plaques are painful, itchy, recurrently infected, fissured, or limit manual and sexual function, clinicians should treat the presentation as at least moderate regardless of body surface area.
Cardiometabolic and Mental Health Screenings Catch Hidden Comorbidities
Comprehensive care requires active screening for associated systemic conditions that frequently accompany severe skin disease. Clinicians must screen for psoriatic arthritis by evaluating joint pain, swelling, enthesitis, back pain, and nail disease using validated tools like the Psoriasis Epidemiology Screening Tool.
Cardiometabolic evaluation treats psoriasis as a cardiovascular risk enhancer by measuring blood pressure, lipids, and glycated hemoglobin, while addressing smoking cessation and weight management. Mental health screenings for depression and anxiety remain essential, as mood disorders commonly improve once effective skin control is achieved. Non-alcoholic fatty liver disease appears more frequently among psoriasis patients, making baseline liver function tests and metabolic markers critical before initiating certain systemic medications.
Topical Treatments Serve Primary Care While Systemic Options Clear Skin
First-line management in primary care centers on optimized topical therapies, including potent corticosteroids combined with vitamin D analogues, alongside short courses for acute flares and steroid-sparing maintenance. Routine use of systemic corticosteroids for chronic plaque psoriasis is generally avoided due to significant flare and rebound risks.
When topical treatments fail or disease severity crosses moderate thresholds, modern systemic options offer significant relief. Conventional non-biologic systemics include methotrexate, ciclosporin, and acitretin, each requiring careful monitoring for organ toxicity and teratogenicity. Targeted oral small molecules, such as the phosphodiesterase-4 inhibitor apremlast and the selective tyrosine kinase 2 inhibitor deucravacitinib, provide alternative oral pathways with distinct safety profiles.
Biologic therapies delivered via subcutaneous injection or infusion achieve high rates of near-clear to clear skin. Interleukin-23 inhibitors like guselkumab, risankizumab, and tildrakizumab demonstrate complete skin clearance and durable remission in comparative trials. Meanwhile, interleukin-17 inhibitors such as secukinumab, ixekizumab, and bimekizumab deliver rapid skin clearance, though clinicians exercise caution regarding potential inflammatory bowel disease interactions and candidiasis risks.
Frequently Asked Questions About Psoriasis Management
What specific score on the Psoriasis Epidemiology Screening Tool triggers a rheumatology referral?
A score of 3 or higher out of the 5 screening questions prompts an immediate referral to a rheumatology specialist for suspected psoriatic arthritis.
Why is acitretin management unique compared to other systemic therapies?
Acitretin is a keratinisation modulator that requires highly effective contraception during therapy and for three years after stopping due to its extreme teratogenicity.
How do interleukin-17 inhibitors differ in their target mechanisms?
Medications like secukinumab and ixekizumab target interleukin-17A, whereas bimekizumab uniquely targets both interleukin-17A and interleukin-17F to achieve rapid skin clearance.
Keep reading