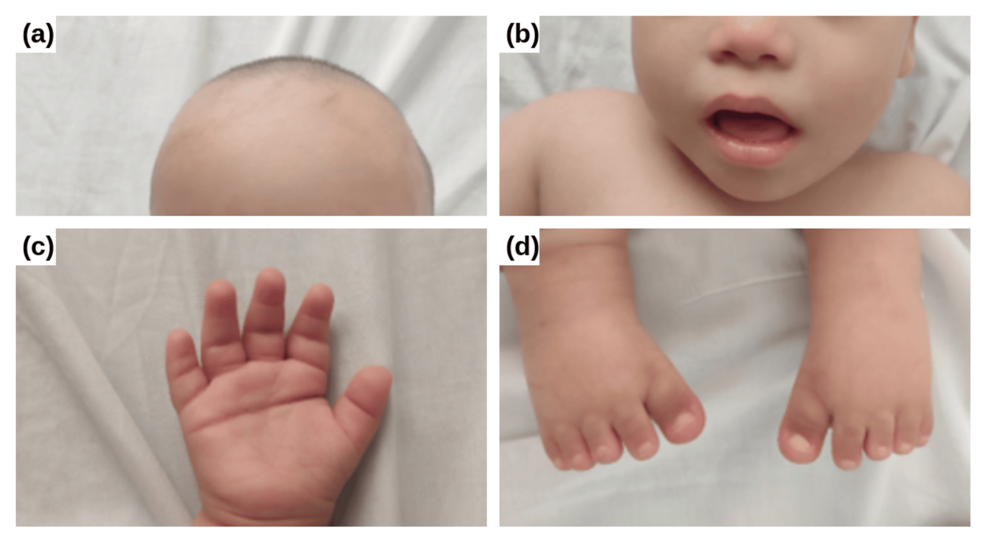
A rare case of mosaic double aneuploidy involving both trisomy 21 and XYY syndrome has been documented in a 24-month-old boy. The patient presents with a dual chromosomal makeup that occurs with extreme rarity, combining the genetic characteristics of Down syndrome—which typically affects 1 in 700 to 1,000 live births—with Jacobs syndrome, an extra Y chromosome condition affecting roughly 1 in 1,000 male births.
Clinical Presentation at Twenty-Four Months
Born at term to a 40-year-old mother and 39-year-old father with a birth weight of 4,100 grams, the toddler required three days in a neonatal intensive care unit for perinatal asphyxia linked to a fetal infection. At 15 months of age, he underwent surgery for bilateral congenital cataracts, a procedure complicated by laryngeal dyspnea that necessitated a pediatric intensive care admission. By 24 months, his weight measured 10 kg and his length stood at 78 cm, placing both measurements slightly below the 50th growth chart percentile established for children with Down syndrome.
Physical examinations revealed classic dysmorphic features associated with trisomy 21, including generalized hypotonia, hypertelorism, bilateral strabismus featuring epicanthal folds, a flat nasal bridge, low-set ears, a short neck, and macroglossia. His hands appeared short and broad with bilateral single transverse palmar creases and clinodactyly of the fifth fingers, while his feet displayed a wide sandal gap between the first and second toes. Genital examinations noted a penile length of 20 mm (-2.5 standard deviations) along with bilateral undescended testes, while cardiac evaluations via transthoracic echocardiography showed no structural abnormalities.
Diagnostic Cytogenetic Findings
Cytogenetic analysis of peripheral blood lymphocytes using Giemsa banding revealed a mosaic double aneuploidy pattern. Testing identified two distinct cell lines: 48,XYY,+21, which accounted for 55.1% of the 49 analyzed cells, and 47,XY,+21, which made up the remaining 44.9%. This laboratory breakdown established the dual diagnosis while demonstrating how trisomy 21 predominated the clinical presentation, potentially masking physical traits that might otherwise point toward the additional Y chromosome.
Developmental assessments at 24 months showed global delays. While the child could sit unsupported and creep, he had not yet achieved crawling, standing, or walking. Laboratory investigations confirmed transient congenital hypothyroidism, while tests for toxoplasmosis, other infections, rubella, cytomegalovirus, and herpes simplex virus returned negative results.
Comparative Genetic Characteristics
| Condition | Genetic Mechanism | Estimated Incidence | Primary Clinical Features |
|---|---|---|---|
| Down Syndrome | Extra copy of chromosome 21 (trisomy 21) | 1 in 700–1,000 live births | Hypotonia, characteristic facial dysmorphism, cognitive delay, congenital heart defects |
| XYY Syndrome | Presence of an additional Y chromosome (47,XYY) | 1 in 1,000 male births | Tall stature, speech delays, learning difficulties, variable genital abnormalities |
| Double Aneuploidy | Coexistence of trisomy 21 and XYY syndrome | Exceptionally rare | Overlapping features predominantly influenced by trisomy 21, requiring karyotyping for confirmation |
Patient Management and Diagnostic Follow-Up
Medical teams initiated pelvic ultrasounds, a barium enema, and anorectal manometry to investigate the patient’s cryptorchidism and chronic constipation. Because XYY syndrome typically presents with subtle or variable manifestations and often remains undiagnosed during early childhood, researchers emphasize that comprehensive karyotyping remains vital for patients presenting with suspected Down syndrome when clinical features diverge or warrant deeper genetic evaluation.
The coexistence of these two chromosomal variations underscores the necessity of precise cytogenetic testing in pediatric populations. As clinicians continue monitoring the patient’s growth, endocrine status, and developmental milestones, the documented case adds to the sparse medical literature regarding double aneuploidy involving sex and autosome chromosomes.
Worth a look