SGLT2 Inhibitors Face Scrutiny in Polycystic Kidney Disease Treatment
Sodium-glucose cotransporter 2 (SGLT2) inhibitors slow the loss of kidney function in general chronic kidney disease, but their safety in autosomal dominant polycystic kidney disease remains unproven. The 2025 Kidney Disease: Improving Global Outcomes guideline does not recommend these medications for ADPKD patients, even for managing diabetes, because the drugs have not been evaluated for this specific genetic condition.
The treatment paradox stems from how these medications work. SGLT2 inhibitors cause glycosuria and osmotic diuresis, prompting the body to raise vasopressin levels to conserve water. Because vasopressin acts through cyclic AMP to drive kidney cyst growth, researchers worry the drugs could accelerate the exact process that the approved therapy tolvaptan blocks.
Diverging Findings From Recent Clinical Analyses
Two meta-analyses published in 2026 examined the accumulating observational cohorts, case series, and one open-label crossover trial regarding SGLT2 inhibitors in ADPKD patients. Tantush et al. pooled eight studies covering 3,180 patients and reported a slower decline in estimated glomerular filtration rates. However, 2,640 of those patients came from a single American cohort composed entirely of individuals with type 2 diabetes.
Kanbay et al. published a second meta-analysis pooling six studies with 451 patients. While this analysis found a slower rate of eGFR decline compared to pre-treatment baselines, it showed no significant difference when compared directly to patients not taking SGLT2 inhibitors and no measurable effect on total kidney volume.
Dual Inhibitor Phlorizin Reduces Cyst Growth in Rats
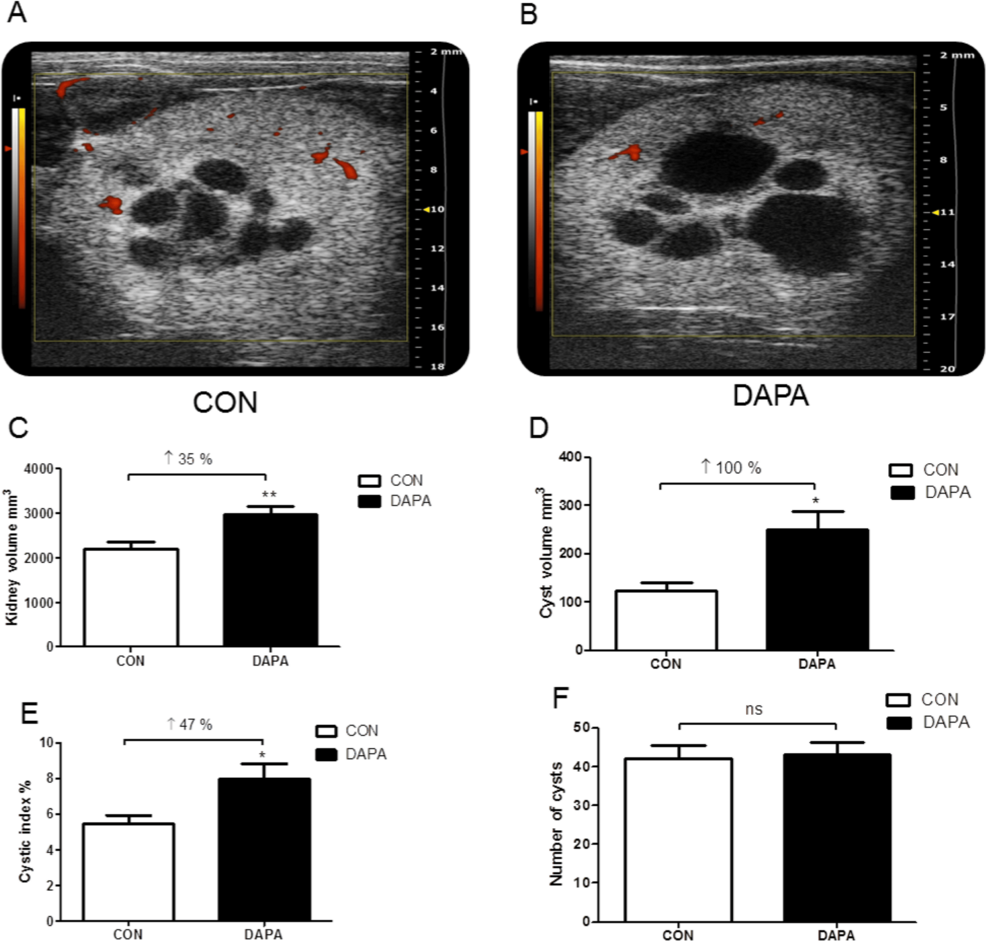
Preclinical testing in animal models highlights inconsistent responses depending on the underlying pathology. In Han:SPRD rats, where cysts originate in the proximal tubule, the dual SGLT1 and SGLT2 inhibitor phlorizin reduced cyst growth and preserved kidney function. Conversely, in PCK rats modeling autosomal recessive polycystic kidney disease with distal cysts, dapagliflozin increased cyst volume by 23 percent and quadrupled albuminuria. While tolvaptan remains the only approved disease-modifying drug for ADPKD, its use requires regular liver monitoring and large fluid intake due to aquaresis.
Frequently Asked Questions About SGLT2 Inhibitors and ADPKD
* Why are SGLT2 inhibitors excluded from standard ADPKD treatment guidelines?
The 2025 KDIGO guidelines omit these medications because clinical trials establishing their benefits for chronic kidney disease specifically excluded ADPKD patients due to concerns over vasopressin stimulation and cyst growth.
* What did Tantush et al.’s meta-analysis discover about patient outcomes?
Tantush et al. reported a slower decline in estimated glomerular filtration rates across 3,180 pooled patients, though the vast majority of those individuals belonged to a single US cohort with type 2 diabetes.
* How do animal models react differently to SGLT2 inhibition?
Proximal-tubule cyst models like the Han:SPRD rat showed reduced cyst growth with phlorizin, whereas distal-tubule models like the PCK rat experienced increased cyst volume and worsened albuminuria when treated with dapagliflozin.
Worth a look