Newer antibiotics cut mortality and kidney injury in drug-resistant infections, review finds
A systematic review of nine comparative studies found that ceftazidime–avibactam regimens lowered 30-day mortality to 33 percent from 48 percent with older colistin-based therapy and reduced acute kidney injury by more than half, Cureus reported.
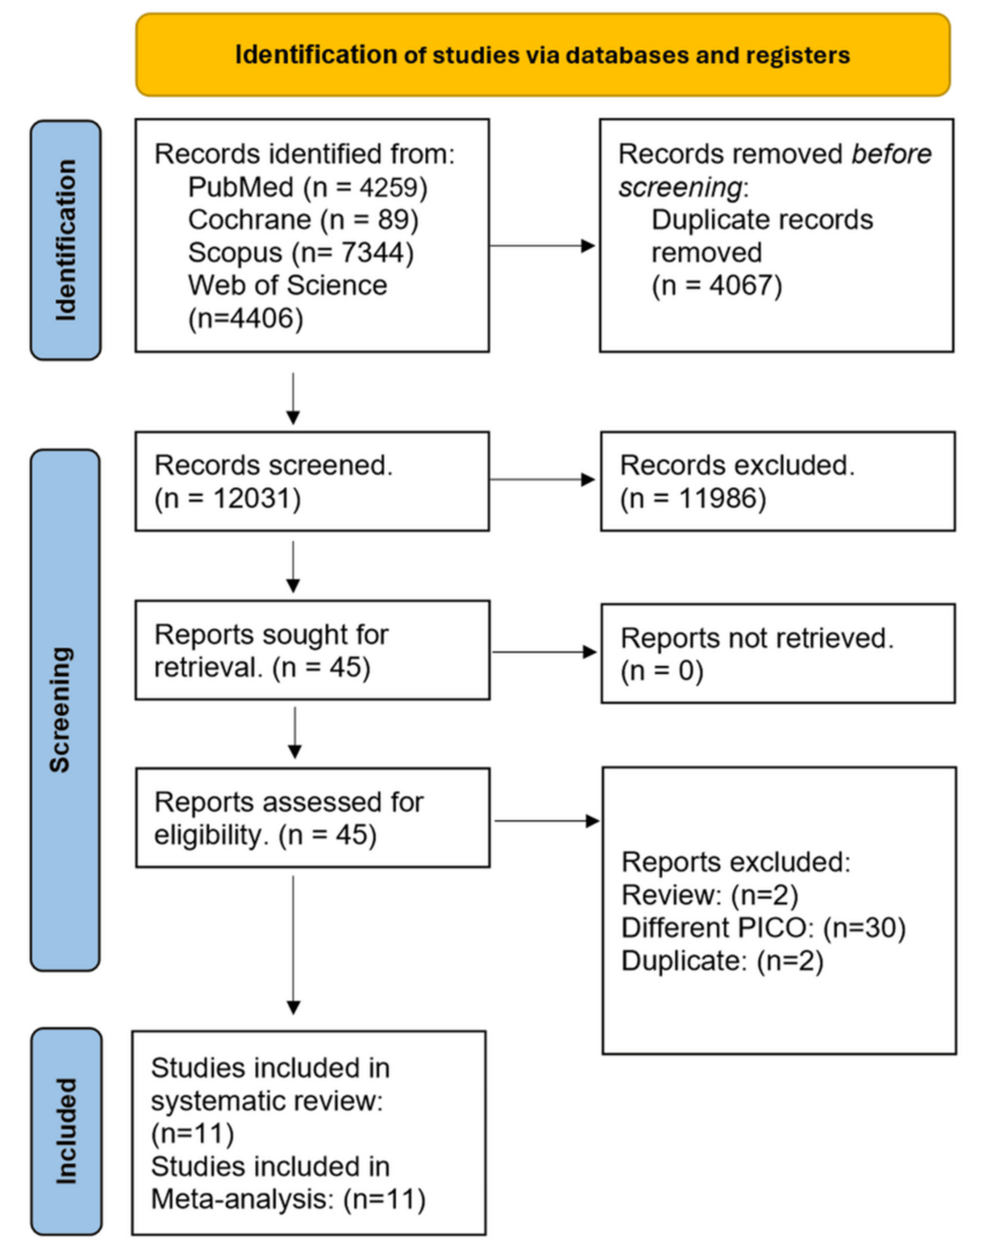
The analysis, published in Cureus and registered in PROSPERO (CRD420261420605), pooled data from adults treated for carbapenem-resistant Enterobacterales (CRE) infections between 2009 and 2024. Reviewers searched PubMed, CENTRAL, Web of Science and Scopus through June 2026 and applied random-effects models to calculate risk ratios for mortality, clinical cure, microbiological eradication and renal outcomes.
“CAZ-AVI was associated with higher clinical cure and substantially less AKI than colistin-based treatment,” wrote Almangour and colleagues in the largest cohort, a 230-patient multicenter study in Saudi Arabia where clinical cure reached 71 percent with the newer agent versus 52 percent with colistin (p=0.004) and acute kidney injury dropped to 15 percent from 33 percent (p=0.002). In a 208-patient matched Italian cohort of KPC-producing Klebsiella pneumoniae bacteremia, 30-day mortality was 36.5 percent with ceftazidime–avibactam salvage therapy versus 55.8 percent with conventional regimens (p=0.005). For metallo-β-lactamase producers, a prospective 102-patient study in Italy and Greece showed 30-day mortality of 19.2 percent with ceftazidime–avibactam plus aztreonam compared with 44 percent on other active antibiotics (p=0.007).
The single randomized trial in the review, CREDIBLE-CR, assigned 40 CRE patients to cefiderocol or best-available therapy. Clinical cure in the Enterobacterales subgroup was 66 percent versus 45 percent; mortality did not differ. Trial-wide mortality imbalance was driven by Acinetobacter infections, not Enterobacterales. Reviewers noted limitations: most evidence came from observational cohorts rather than randomized trials; regimen- and carbapenemase-specific meta-analyses were not feasible because most categories contained too few comparable studies; Embase was not searched; and follow-up periods varied across studies.
The CDC classifies CRE as an urgent public-health threat and the WHO lists it as a critical-priority pathogen. Carbapenemases — KPC, NDM, VIM, IMP and OXA-48-like enzymes — are frequently carried on mobile genetic elements, enabling spread across species and healthcare settings.
“Optimal management remains uncertain,” the review authors concluded. “Emerging resistance to newer agents further underscores the importance of mechanism-directed therapy and antimicrobial stewardship.”
Keep reading