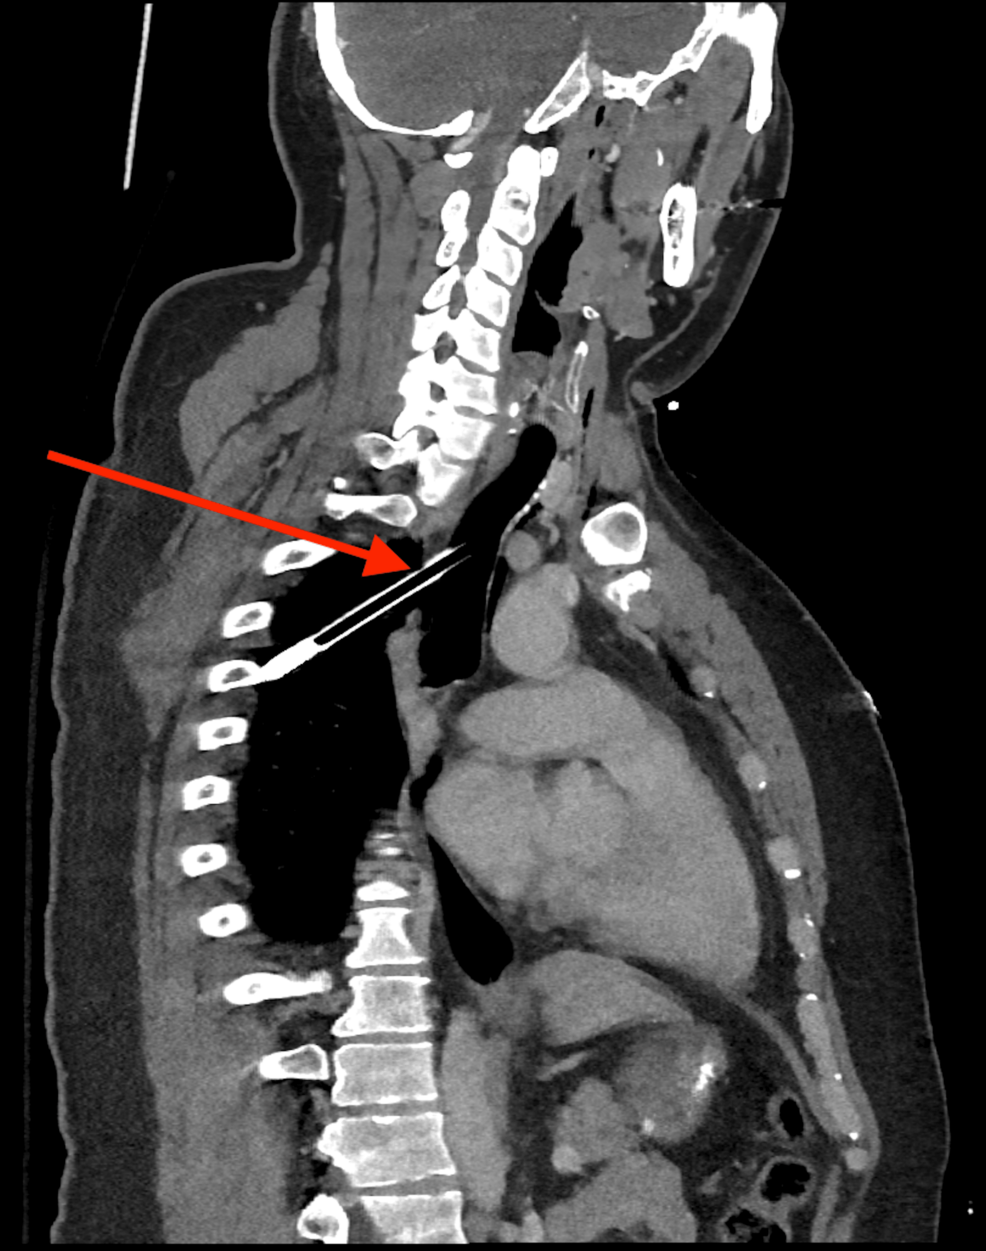
Venovenous ECMO Used for Penetrating Neck Injury
Venovenous extracorporeal membrane oxygenation provided airway and ventilation support for a 34-year-old male who sustained a penetrating neck injury from a crossbow arrow, [cureus.com] reported. The patient, measuring 175 cm in height and weighing 108 kg, arrived at the emergency department after loading his crossbow at home. He reported removing the exposed portion of the arrow himself before arrival, leaving the arrowhead and a section of the shaft lodged within his neck and thorax.
Physical examination revealed a 1 cm midline anterior neck wound with crepitus and no active bleeding. Computed tomography scans of the chest mapped a 7 cm arrow traveling through the anterior midline chest into the superior mediastinum and terminating within the right superior lower lobe. Laboratory values, including complete blood count and comprehensive metabolic panel, returned within normal limits.
Surgical Extraction Under Extracorporeal Support
Medical staff initiated venovenous ECMO prior to anesthesia induction to avoid airway compromise from patient movement or intubation manipulation. Awake bronchoscopy confirmed a tracheal injury with the embedded arrow. The trauma surgery team performed an anterior repair of the neck and the trachea, followed by an esophagogastroduodenoscopy that showed no esophageal injury.
Providers then repositioned the patient into the left lateral decubitus position, which caused a brief desaturation to 80 percent and a chatter phenomenon on the ECMO circuit. Medical staff resolved the circuit issue by administering 250 mL of albumin for volume support. A robotic-assisted thoracoscopic procedure extracted the arrow intact from the right upper lobe. The arrowhead was located behind the superior vena cava, above the azygos vein, and anterior to the esophagus.
A repeat bronchoscopy after the tracheal repair demonstrated good tissue approximation without air leaks on the ventilator. Clinicians successfully weaned the patient from venovenous ECMO while leaving the 6.0 MLT in place. The patient was extubated, transferred to recovery with a face mask for oxygen delivery, and kept under observation with a chest tube in place.
Frequently Asked Questions About the Case
Why was venovenous ECMO chosen instead of immediate intubation?
Traditional intubation and mechanical ventilation carry significant risks of exacerbating tracheal injuries, creating false passages, or inducing rapid respiratory failure. Venovenous ECMO maintains oxygenation and ventilation without requiring direct manipulation of the damaged trachea prior to surgical repair, as documented in the Cureus case report.
How deep did the arrow penetrate into the patient’s body?
Computed tomography imaging showed that the remaining 7 cm portion of the arrow traveled from the anterior midline chest through the superior mediastinum and ended inside the right superior lower lobe of the lung.
What complications occurred during the surgical procedure?
The patient experienced a brief oxygen desaturation down to 80 percent when shifted into the left lateral decubitus position. During this phase, a chatter phenomenon occurred on the ECMO circuit, which medical staff successfully corrected by administering 250 mL of albumin for volume support.
Keep reading