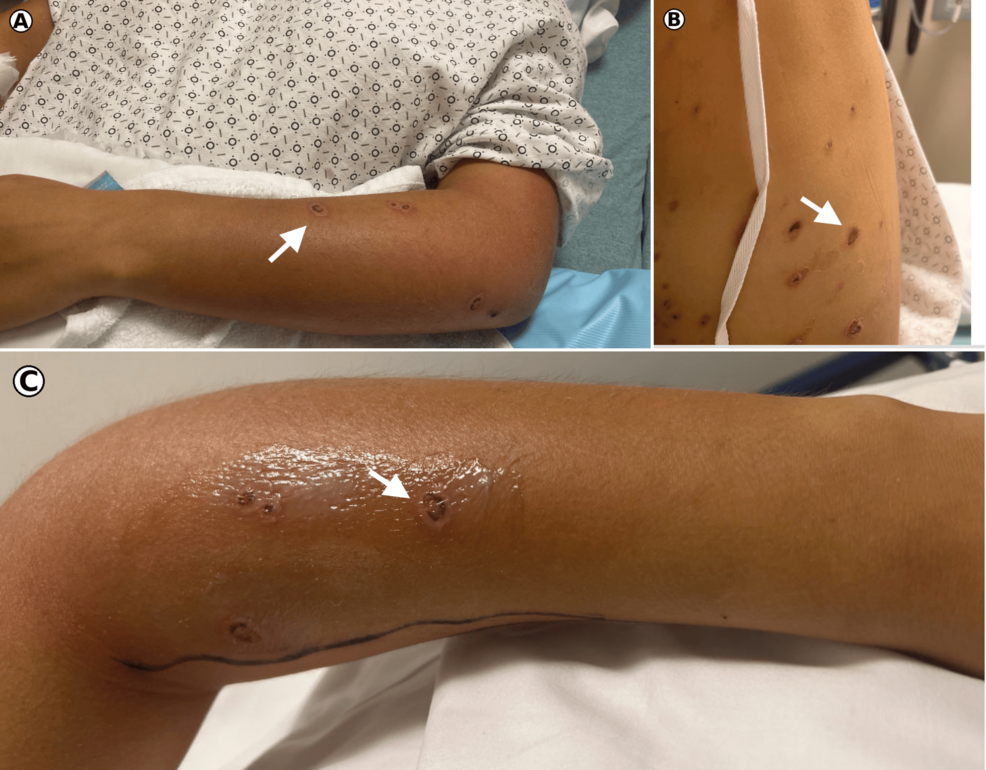
Disseminated bullous impetigo in an immunocompetent adult is rare, manifesting as an extensive skin infection that predominantly affects young children. An 18-year-old woman with no underlying medical history developed a widespread vesiculobullous rash covering her trunk, intertriginous folds, buttocks, perineum, and lower extremities after sustaining cutaneous abrasions during travel in rural Costa Rica.
While impetigo accounts for more than 140 million cases globally, 70% of diagnoses involve nonbullous presentations, and it is most frequently seen in children aged two to five years. Bullous impetigo makes up the remaining 30% and stems exclusively from exfoliative toxin-producing Staphylococcus aureus, which cleaves desmoglein 1 to trigger superficial skin blistering.
Travel Exposures And Initial Misdiagnosis In Costa Rica
During her travels, the patient swam in oceans and rivers, slept on outdoor cots under mosquito nets, and sustained abrasions from scraping her back against a forest log.
New lesions continued to emerge through the ninth day of illness alongside fevers. Upon returning to the United States on the tenth day of illness, she sought emergency hospital care.
Hospital Presentation And Severe Laboratory Markers
Hospital examination on Day 10 revealed a regular rhythm tachycardia of 116 beats per minute and a maximum temperature of 39.5°C. Physical findings showed diffuse erythema, warmth, and swelling on the left dorsal elbow and forearm, and numerous superficial ovoid lesions in various stages on the back.
Laboratory testing showed significant systemic inflammation, with a white blood cell count of 24 × 10³/µL, 89% neutrophils, a C-reactive protein level of 17.4 mg/dL, and a procalcitonin level of 1.2 ng/mL. Wound cultures isolated methicillin-sensitive Staphylococcus aureus (MSSA), while all other infectious studies obtained were negative.
Orthopedic Complications And Targeted Antibiotic Treatment
On the second hospital day, the patient developed worsening left elbow pain and swelling. Orthopedic specialists diagnosed cellulitis with septic olecranon bursitis.
Initial broad-spectrum intravenous therapy with vancomycin, ceftriaxone, and doxycycline was narrowed to oral cephalexin at 500 mg four times daily alongside topical mupirocin. Her fevers, elbow discomfort, and skin lesions resolved.
Frequently Asked Questions
Why does bullous impetigo rarely affect immunocompetent adults?
Bullous impetigo is common in childhood, but it is distinctly uncommon in immunocompetent adults. When adult cases do occur, they usually involve predisposing factors like atopic dermatitis flares or underlying malignancies that facilitate auto-inoculation.
What caused the patient’s elbow complication during hospitalization?
The patient developed cellulitis with septic olecranon bursitis on her second hospital day. This localized bacterial spread required evaluation by orthopedic specialists alongside her ongoing dermatological care.
Which diagnostic tests confirmed the causative organism?
Wound culture of the skin lesion isolated methicillin-sensitive Staphylococcus aureus, guiding physicians to narrow her treatment regimen from broad-spectrum intravenous antibiotics to targeted oral cephalexin and topical mupirocin.
Worth a look