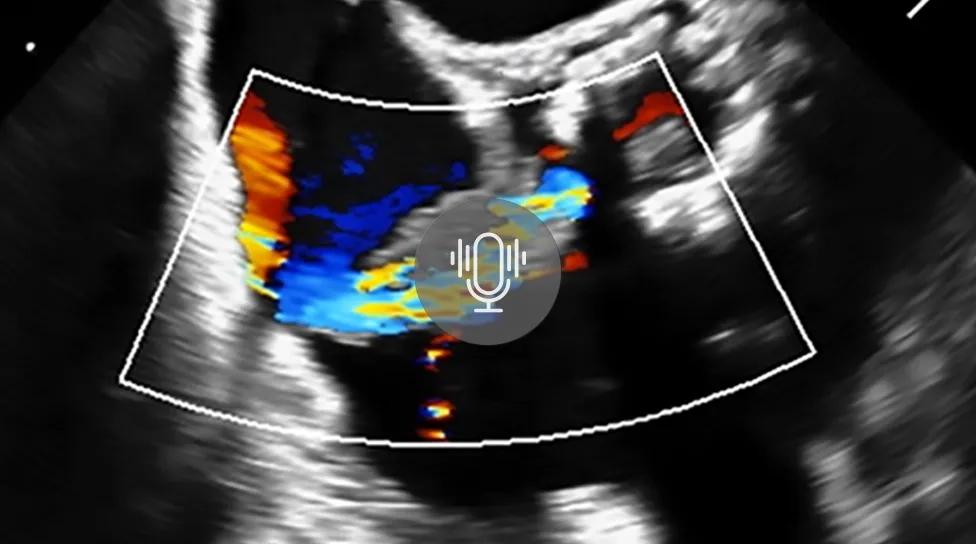
When a heart team treats a patient with aortic valve endocarditis, time is of the essence more than in many other care scenarios, Consult QD reported.
If the vegetation burden is large, the infection can remain uncontrolled while raising the risk of a detached embolus and subsequent stroke.
Patients who develop signs and symptoms of heart failure can experience severe aortic valve regurgitation. That complication can rapidly lead to cardiogenic shock because the left ventricle lacks time to compensate for the sudden pressure surge, according to Cleveland Clinic.
“When we see these patients, we need to quickly assess who requires urgent and elevated care due to risks like these,” said Milind Desai, MD, MBA, Medical Director of Cleveland Clinic’s Aorta Center. “These are the types of red flags that will send me to the office of one of my cardiac surgeon colleagues right away.”
Evaluating Complex Anatomical Destruction
Endocarditis can also induce abscess formation that impinges on the atrioventricular node, resulting in an atrioventricular block. Managing these complex presentations requires evaluating initial imaging, timing surgical intervention, and choosing among distinct operative approaches.
Surgeons follow a logical sequence of three options depending on how severely the infection has damaged the tissue. The preferred approach involves valve repair to preserve the native valve whenever clinicians encounter a localized infection early enough.
“Typically, if it’s a localized infection, we remove that small part and reconstruct the affected portion of the leaflet,” said Per Wierup, MD, PhD, a heart surgeon at Cleveland Clinic, told Consult QD. “That’s our ideal, go-to approach.”
Choosing Surgical Repair Methods
When the valve is extensively damaged by the infection, replacement becomes necessary. Surgeons generally select a tissue prosthesis to eliminate the need for long-term anticoagulation therapy, which can increase the risk of future brain bleeds.
A third option is deployed when the infection extends beyond the native valve to form an abscess. In those cases, surgeons practically always use a homograft to manage extensive destruction and resist reinfection.
“The third option is considered when the infection has spread outside the native valve and has created an abscess,” Wierup told Consult QD. “In these cases, even if the abscess is small, we practically always use a homograft, which is very, very efficient in taking care of extensive destruction and also highly resistant to reinfection.”
Addressing Double-Valve Endocarditis
Double-valve endocarditis involving both the aortic and mitral valves can require a Commando operation when infection affects the curtain between them. The procedure requires opening the area between the valves, removing the infection, and reconstructing the curtain with bovine pericardium.
Surgeons then place a mitral valve prosthesis alongside an aortic valve prosthesis or a homograft. While Wierup performed many of those operations earlier in his career, he has learned to avoid them in less destructive cases by using local reconstructions.
Intraoperative visualization remains critical because surgical judgment must adapt to the actual anatomy discovered during the operation. Multidisciplinary management and volume-based experience dictate the success of these complex interventions.
Frequently Asked Questions
Why does a stroke complicate the timing of aortic valve endocarditis surgery?
Once a patient suffers a stroke from a detached embolus, clinicians must often wait up to six weeks until a neurologist clears the patient for surgery to minimize additional neurological risks, according to Cleveland Clinic.
What specific cardiac finding makes a cardiologist contact a surgeon immediately?
An enlarging PR interval or advanced degrees of atrioventricular block caused by an abscess impinging on the atrioventricular node serves as an immediate red flag, Cleveland Clinic reported.
Cleveland Clinic, founded in 1921 by faculty and alumni of Case Western Reserve University School of Medicine, has been ranked the world’s top hospital for cardiology and heart surgery for the past twenty years. The nonprofit academic medical center recorded 15.96 million patient visits and 82,608 employees in 2024.
Why do surgeons generally choose tissue prostheses over mechanical valves for these replacements?
Surgeons choose tissue prostheses to avoid the long-term need for anticoagulation medications, which can lead to brain bleeds down the road, Wierup told Consult QD.
Worth a look