Acute coronary syndromes typically demand elevated cardiac troponin levels and distinct electrocardiogram changes, yet clinicians sometimes encounter severe arterial blockages with atypical initial presentations.
A 47-year-old male patient with hyperlipidemia and a coronary artery calcium score exceeding 200 reported worsening exertional chest pain and dyspnea. Despite normal electrocardiogram findings, serial troponin measurements, prior stress tests, and echocardiograms, his continuing symptoms prompted hospital admission for suspected unstable angina.
Cardiac catheterization subsequently revealed a complete, 100% occlusion of the proximal right coronary artery. Medical teams successfully treated the lesion with a drug-eluting stent, and the patient’s symptoms resolved completely within three months. This clinical scenario illustrates the diagnostic limitations of relying exclusively on non-invasive testing and standard biomarkers when detecting significant coronary artery disease, particularly in patients with established collateral circulation.
Clinical Judgment in Diagnostic Uncertainty
Medical evaluations for acute coronary syndromes require distinguishing between unstable angina, non-ST-elevation myocardial infarction, and ST-elevation myocardial infarction. Universal definitions mandate evidence of acute myocardial injury demonstrated by a rise or fall in cardiac troponin above the assay-specific 99th-percentile upper reference limit alongside ischemia. However, patients presenting with ischemic symptoms without biomarker evidence often fall within the unstable angina spectrum.
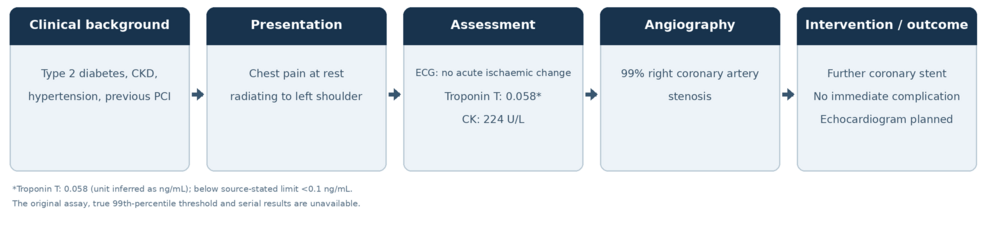
In a separate case reviewed by Cureus, a male patient in his 60s with chronic kidney disease, diabetes, and hypertension presented with resting chest pain, an initial electrocardiogram showing no acute ischemic changes, and a troponin T level of 0.058 ng/mL.
Although this numerical value fell below the source-stated reference cutoff of 0.1 ng/mL, subsequent angiography identified a critical 99% stenosis of the right coronary artery requiring stent placement. Treating clinicians recorded a diagnosis of non-ST-elevation myocardial infarction based on clinical presentation and coronary history, highlighting how obstructive coronary anatomy can coexist with atypical biomarker results.
Risk Stratification and Invasive Management
Integrating structured risk stratification tools such as the Thrombolysis in Myocardial Infarction and HEART scores helps clinicians evaluate patients with chest pain when initial non-invasive testing remains inconclusive. Chronic kidney disease frequently complicates biomarker interpretation because baseline troponin concentrations can remain chronically elevated without an acute coronary event, making serial measurements essential.
Specialists emphasize that clinical judgment remains vital when assessing patients with high pre-test probabilities of coronary disease. Early invasive diagnostics may be warranted even when initial electrocardiograms and cardiac biomarker panels fail to show definitive evidence of acute injury.
Related reading