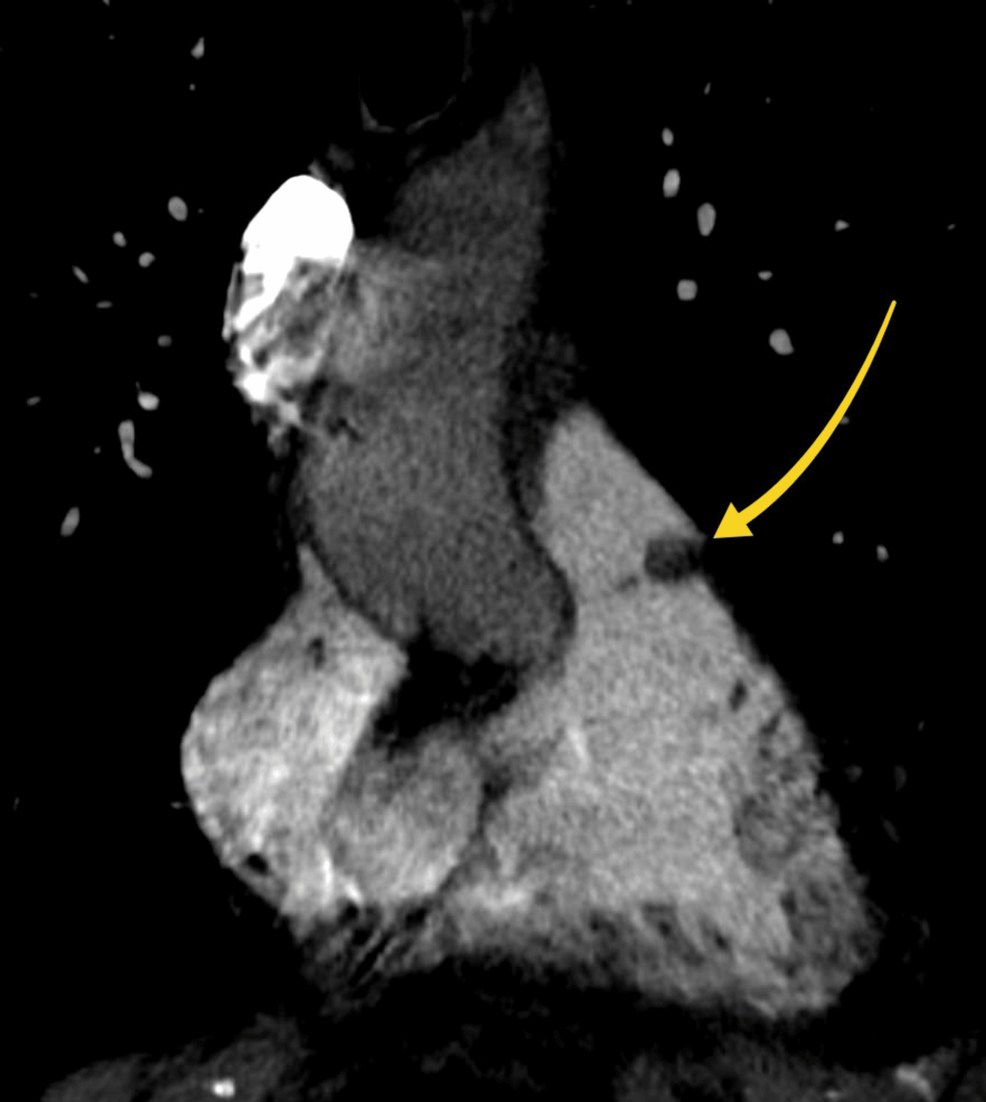
A 60-year-old woman with atypical chest discomfort was found to have an incidental pulmonary valve thrombus despite having no history of pulmonary embolism or known hypercoagulable states, Cureus reported.
Imaging reveals unexpected valvular mass
The patient sought medical attention after experiencing exertional dyspnoea and a sensation of being unable to take an adequate breath. Her husband also observed increased breathing effort during routine walking.
Initial transthoracic echocardiography showed no significant structural cardiac abnormalities or valvular pathology, though clinicians said that views were suboptimal due to the patient’s body habitus. A subsequent CT coronary angiography, performed to investigate her symptoms, identified an incidental filling defect associated with the pulmonary valve.
While the CT coronary angiography showed no flow-limiting coronary artery disease, a dedicated CT pulmonary angiogram confirmed the presence of the lesion. This follow-up scan excluded pulmonary embolism, which is a more common cause of right-sided heart issues.
Multimodality testing clarifies diagnosis
Because the nature of the mass was uncertain, a multidisciplinary team recommended cardiac MRI (CMR) for further characterization. The CMR identified a 10 mm solid ovoid lesion on the pulmonary valve.
The imaging findings helped clinicians differentiate the mass from other potential conditions:
- Thrombus: The lesion showed intermediate signal intensity on cine sequences and lacked abnormal enhancement on delayed gadolinium imaging, which favored a diagnosis of thrombus.
- Infective Endocarditis: Clinical, laboratory, and imaging evidence, including negative blood cultures, ruled out infection.
- Benign Tumors: The absence of delayed gadolinium enhancement helped distinguish the mass from vascularized tumors like papillary fibroelastoma.
The patient’s laboratory results showed a total cholesterol level of 5.5 mmol/L, which is above the reference range of less than 5.0 mmol/L, but her CRP levels remained low at less than 1 mg/L, indicating no active inflammation, Cureus.
Anticoagulation leads to complete resolution
Medical teams treated the patient with warfarin anticoagulation. A follow-up CT pulmonary angiogram conducted three months later demonstrated the complete radiological resolution of the pulmonary valve lesion.
This resolution supported the original diagnosis of thrombus. The case highlights the difficulty of diagnosing unexpected valvular masses, as they can closely resemble infective vegetations or benign tumors on standard imaging.
Comparison of cardiac mass differentials
| Condition | Typical Imaging Characteristics | Key Differentiating Factor in This Case |
|---|---|---|
| Pulmonary Valve Thrombus | Filling defect on CT; no gadolinium enhancement | Resolved completely following warfarin treatment |
| Infective Endocarditis | Valvular vegetation; often associated with fever/infection | Negative blood cultures and low CRP levels |
| Papillary Fibroelastoma | Small, mobile, pedunculated mass | Lack of vascularized enhancement on CMR |
Common causes of right-sided thrombus
While left-sided intracardiac thrombi are frequently linked to atrial fibrillation or left ventricular dysfunction, right-sided thrombi are less common. According to medical literature, right-sided thrombi typically occur in association with:
- Deep venous thrombosis
- Pulmonary embolism
- Malignancy
- Right ventricular dysfunction
- Intracardiac devices or central venous catheters
Isolated pulmonary valve thrombus remains exceptionally rare in patients without structural valve disease, pulmonary hypertension, or pulmonary embolism.