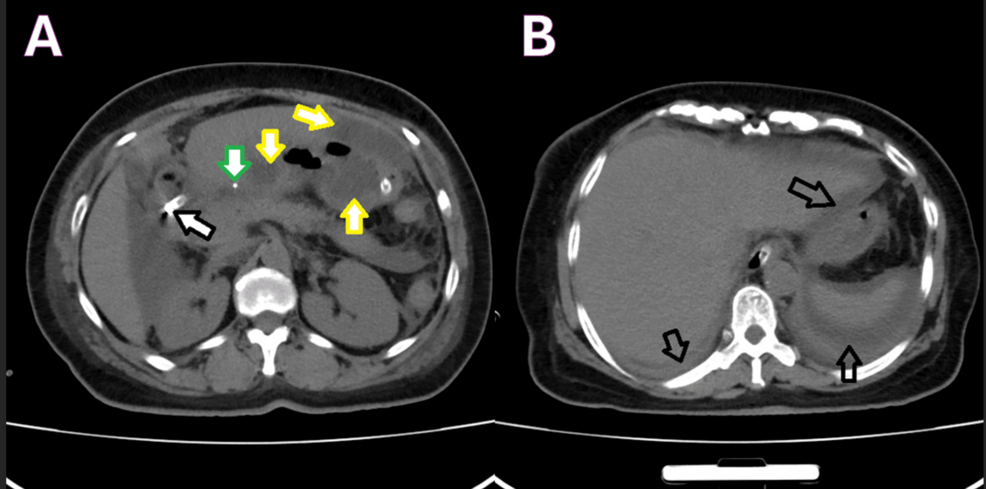
A 60-year-old woman with diabetes and hypertension died of septic shock two days after surgeons found a 4-centimetre fish bone inside a small liver abscess and generalized purulent peritonitis, despite a gastric perforation that appeared sealed at operation, Cureus reported
The case, published in the journal’s June 2024 edition, illustrates how a contained visceral injury can mask the severity of intra-abdominal infection, particularly in patients whose comorbidities blunt the inflammatory response.
The patient presented with one week of progressively worsening but relatively mild diffuse abdominal pain and nausea, without fever or a history of foreign-body ingestion.
“Patients with fish bone-related gastrointestinal perforation may present with nonspecific symptoms, including subacute abdominal pain and low-grade fever, which can delay diagnosis,” the authors wrote.
At initial evaluation she was tachycardic at 105 beats per minute with mild diffuse tenderness. Four hours after arrival leukocytosis was 12,000 cells per microlitre; two hours later she spiked a fever of 39.5 °C, the white-cell count had risen to 16,000, and lactate climbed to 2.3 mmol per litre with a creatinine of 1.6 mg per decilitre.
Computed tomography showed a calcific-density foreign body penetrating the posterior wall of the gastric antrum, mild pneumoperitoneum, free fluid and small interloop collections. The findings prompted an emergency laparotomy.
At operation the left hepatic lobe was densely adherent to the gastric antrum. A 1-by-1-centimetre abscess in the left lobe contained the fish bone, which was removed. The presumed antral penetration site appeared sealed; no gastric repair was performed. The peritoneal cavity was lavaged and two drains were placed.
Postoperatively the patient remained hypotensive at 80/60 mmHg or lower, febrile to 40 °C, and developed worsening acidosis (pH 7.16), hyperlactatemia (8.0 mmol/L) and acute kidney injury (creatinine 3.0 mg/dL). Despite meropenem, vasopressors and mechanical ventilation she died on postoperative day two.
A systematic review of 178 cases of liver abscess caused by ingested foreign bodies found that fish bones accounted for 51 percent of identified objects, the authors noted. Abdominal pain and fever were the most common manifestations, though presentation varies.
CT is generally considered the most useful imaging modality for locating the foreign body and assessing complications, although small bones may still be missed. The combination of a sealed gastric perforation, a tiny hepatic abscess harboring a long fish bone, and diffuse purulent peritonitis appears unusual in the literature.
The operating surgeon, Dr Ernesto Hernández, obtained verbal informed consent for publication from the patient’s next of kin. Written consent was not obtained because re-establishing contact with the family was not feasible.
Why the presentation was deceptive
Diabetes and hypertension can blunt peritoneal signs and fever, allowing a transmural infection to advance before the patient appears critically ill. In this case the inflammatory adhesions between stomach and liver initially contained the perforation, creating a small abscess that sequestered the fish bone and its bacterial load. Once that containment failed, generalized peritonitis and septic shock progressed over hours despite source control.
CT preferred for sharp objects, thorough liver exploration needed
- CT with intravenous contrast remains the study of choice when a sharp foreign body is suspected; plain radiographs miss most fish bones.
- A “sealed” perforation at laparotomy does not exclude ongoing sepsis from a migrated foreign body in an adjacent organ.
- Thorough exploration of the left hepatic lobe and lesser sac is warranted when the gastric antrum is the suspected entry point.
Surgery rates, fish bone statistics, sealed perforation risks
- How common is surgery for ingested foreign bodies?
- Fewer than 1 percent of ingested foreign bodies require surgical intervention; 10 to 20 percent need endoscopic removal, and the majority pass spontaneously.
- What percentage of foreign-body liver abscesses are caused by fish bones?
- In a systematic review of 178 cases, fish bones accounted for 51 percent of identified objects.
- Can a gastric perforation appear sealed at surgery yet still cause fatal peritonitis?
- Yes. In this case the perforation site looked closed, but a fish bone had migrated into the left hepatic lobe, formed a small abscess, and seeded generalized purulent peritonitis that led to septic shock and death.
Related reading