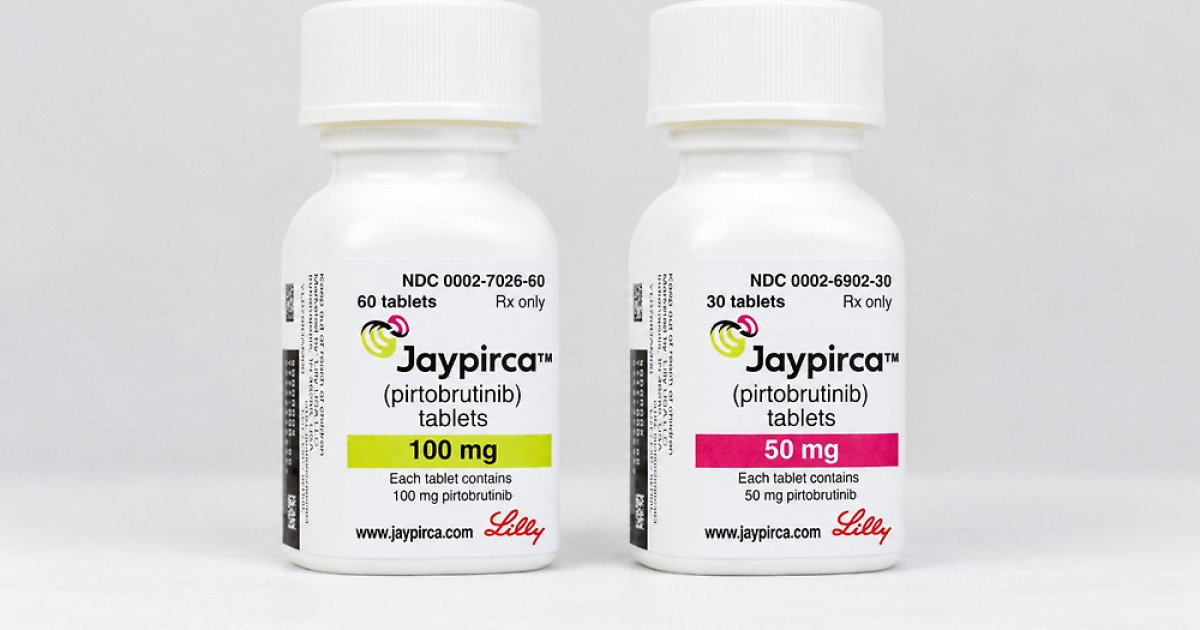
The U.S. Food and Drug Administration approved the targeted blood cancer treatment Jaypirca for expanded use as a first-line monotherapy on October 2, 2024. The decision allows the drug to treat adult patients with chronic lymphocytic leukemia or small lymphocytic lymphoma who have not received prior treatment and do not have a 17p deletion.
FDA Approval Details for Chronic Lymphocytic Leukemia
Chronic lymphocytic leukemia and small lymphocytic lymphoma are blood cancers characterized by the abnormal accumulation of B cells, which are immune cells that produce antibodies to fight infections. Clinicians distinguish the two conditions based on location: chronic lymphocytic leukemia primarily affects the blood and bone marrow, while small lymphocytic lymphoma concentrates mainly in lymph nodes. The newly approved patient population excludes individuals with a 17p deletion, a genetic anomaly involving the loss of a portion of chromosome 17 that affects the TP53 tumor suppressor gene and appears in approximately 5% to 8% of newly diagnosed patients.
Eli Lilly manufactures the medication, known generically as pirtobrutinib. Previously, the regulatory agency restricted Jaypirca use in the United States to adults with chronic lymphocytic leukemia or small lymphocytic lymphoma who had already received treatment with a covalent Bruton’s tyrosine kinase inhibitor and experienced disease progression or treatment failure.
Clinical Trial Results from the BRUIN CLL-313 Study
The international Phase 3 clinical trial known as BRUIN CLL-313 provided the clinical evidence supporting the expanded approval. The study enrolled 282 previously untreated patients lacking a 17p deletion, dividing them equally into a Jaypirca treatment group and a comparator group receiving bendamustine combined with rituximab. Bendamustine is a chemical chemotherapy agent that damages cancer cell DNA, while rituximab is an antibody therapy targeting CD20 on the surface of B cells. The combination of these two agents forms a chemoimmunotherapy regimen.
Researchers conducted the trial as an open-label study where both participants and medical staff knew which treatment was administered. Patients in the Jaypirca arm took a daily 200mg dose until disease progression or unmanageable toxicity occurred, whereas the comparator group received bendamustine and rituximab for six cycles. At a median follow-up of 28.1 months, Jaypirca reduced the risk of disease progression or death by approximately 80% compared to the bendamustine-rituximab regimen. The 24-month progression-free survival rate reached 93.4% for the Jaypirca group and 70.7% for the comparator group, while the overall response rates were 94% and 81%, respectively. The median progression-free survival reached 33.5 months in the comparator arm, but the median was not reached in the Jaypirca arm during the follow-up period. The Journal of Clinical Oncology published these findings.
Comparison With Existing BTK Inhibitors and Combination Regimens
Jaypirca functions as a non-covalent Bruton’s tyrosine kinase inhibitor. Bruton’s tyrosine kinase is a protein that transmits signals necessary for B cells to grow and survive. Older covalent Bruton’s tyrosine kinase inhibitors, such as ibrutinib, acalabrutinib, and zanubrutinib, bind permanently to a specific site on the protein to halt its activity. In contrast, Jaypirca binds reversibly, attaching and detaching from the target protein. This design allows it to maintain activity even when mutations occur at the C481 binding site that typically confer resistance to covalent inhibitors.
Despite these pharmacological differences, the Phase 3 trial compared Jaypirca only against bendamustine and rituximab rather than newer covalent Bruton’s tyrosine kinase inhibitors or venetoclax-based targeted therapies currently utilized in frontline settings. Consequently, clinical data directly comparing Jaypirca to other modern targeted therapies remain unavailable.
Regulatory Status and Safety Information in South Korea
South Korea approved Jaypirca for relapsed or refractory mantle cell lymphoma in 2024. Current domestic regulations also permit its use as a monotherapy for adult chronic lymphocytic leukemia and small lymphocytic lymphoma patients who have previously undergone Bruton’s tyrosine kinase inhibitor therapy. However, the South Korean regulatory approval does not yet encompass the frontline patient population recently authorized by the U.S. Food and Drug Administration.
The approved therapeutic dosage in South Korea is 200mg taken orally once daily until disease progression or unacceptable toxicity develops. Prescribing information instructs healthcare providers and patients to monitor for specific adverse events, including infections, bleeding events, cytopenias, cardiac arrhythmias, secondary primary malignancies, and hepatotoxicity.
Frequently Asked Questions About the New Treatment Indication
What specific genetic mutation excludes patients from this new frontline indication?
Patients with a 17p deletion are excluded from this specific frontline indication for Jaypirca. This genetic anomaly affects the TP53 tumor suppressor gene and is identified in approximately 5% to 8% of newly diagnosed chronic lymphocytic leukemia and small lymphocytic lymphoma cases.
How does Jaypirca differ in binding mechanics from traditional inhibitors?
Traditional covalent inhibitors like ibrutinib, acalabrutinib, and zanubrutinib bind permanently to a specific site on the Bruton’s tyrosine kinase protein. Jaypirca binds reversibly, allowing it to attach and detach while retaining efficacy even if mutations develop at the C481 binding site.
What dosage and administration schedule was evaluated in the Phase 3 trial?
Participants in the BRUIN CLL-313 trial took a daily 200mg dose of Jaypirca continuously until disease progression or unmanageable toxicity forced discontinuation. The comparator group received bendamustine and rituximab limited to six cycles.
Is Jaypirca currently approved for frontline treatment in South Korea?
No. While South Korea approved the drug for relapsed or refractory mantle cell lymphoma and previously treated chronic lymphocytic leukemia or small lymphocytic lymphoma patients, frontline use for treatment-naive patients is not yet part of the local regulatory approval.
Keep reading