Four Toxigenic Diphtheria Cases Confirmed in Nagpur Residential Institute
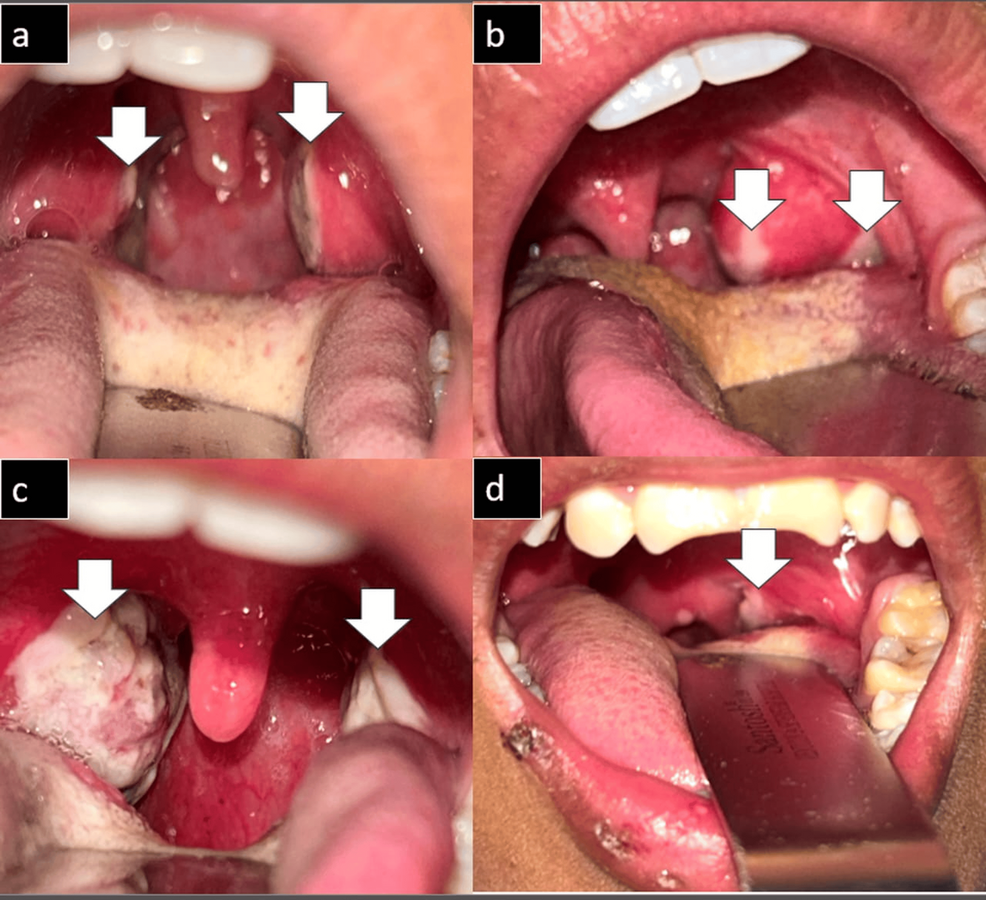
Four epidemiologically linked cases of toxigenic respiratory diphtheria involving three minors and one young adult male have been confirmed at a residential educational institute in Nagpur, Maharashtra, India, Cureus reported. The outbreak, classified as a moderate epidemic incident by Global Incident Tracker, involved patients presenting with fever, throat pain, odynophagia, tonsillar enlargement, and tonsillar pseudomembrane formation.
Clinical Presentations and Patient Timelines
Case 1, a 21-year-old male, and Case 2, his 15-year-old younger sibling, had resided at the residential educational institute for approximately three months after arriving from Assam with unknown immunization histories. Both declined hospital admission and returned home against medical advice. Subsequent field investigations identified two additional cases within the same residential network: Case 3, a 15-year-old student, and Case 4, a 13-year-old student, both of whom had completed their primary immunization schedules up to five years of age.
Oropharyngeal examinations across all four patients revealed Grade II tonsillar enlargement and adherent whitish-grey pseudomembranes that bled upon attempted removal, alongside posterior pharyngeal congestion. None of the four patients exhibited a bull neck appearance, palpable lymphadenopathy, or systemic complications involving the heart or nervous system. Field investigations determined that approximately 160 residential students lived at the institute, with the remaining students staying asymptomatic.
Laboratory Diagnostics and Molecular Confirmation
Microbiological workup confirmed toxigenic Corynebacterium diphtheriae across all specimens. Direct throat smears examined via Gram staining showed slender, non-spore-forming Gram-positive bacilli with club-shaped ends, while Albert staining demonstrated metachromatic granules predominantly at the poles. Cultures yielded whitish-grey circular colonies on blood and chocolate agar, and black pinpoint colonies on potassium tellurite agar. Phenotypic characterization showed the isolates were catalase-positive, glucose-fermenting, nitrate-reduction-positive, and gelatinase-negative.
Elek’s tests proved positive for toxin production, and real-time polymerase chain reaction assays detected both the bacterium and the toxA gene.
Treatment Protocols and Institute Containment
Management strategies varied based on patient admission status. The two siblings who refused hospital admission were managed in home isolation with a 14-day course of oral erythromycin at 500 mg. The admitted patients received intravenous diphtheria antitoxin at 20,000 IU alongside oral erythromycin administered at 40 to 50 milligrams per kilogram daily every six hours for 14 days. To curb further transmission, probable contacts across the institute received prophylactic azithromycin at 500 mg for three days. Following these interventions, public health authorities reported no further symptomatic cases or secondary transmissions linked to the institute.
Frequently Asked Questions About the Nagpur Diphtheria Cluster
What specific laboratory tests confirmed the diphtheria diagnosis?
Diagnosis was confirmed through Albert and Gram staining of direct throat smears, bacterial isolation on blood, chocolate, and potassium tellurite agars, positive Elek’s tests for toxin production, and real-time PCR detection of the toxA gene.
How many residential students were screened during the field investigation?
Field investigations identified residential students living at the Nagpur educational institute, all of whom were assessed for symptoms and exposure.
What prophylactic treatment was given to exposed contacts?
Probable contacts identified during the institute investigation received a three-day course of azithromycin at 500 mg to prevent further spread of the infection.
Worth a look