An 86-year-old woman undergoing right hip hemiarthroplasty under spinal anesthesia experienced an acute intraoperative myocardial infarction and ventricular fibrillation following the interruption of clopidogrel therapy, according to a case report. While hip fracture repairs in older adults carry a documented 30-day myocardial infarction prevalence of approximately 2%, the case highlights a dangerous clinical sequence where monitor-detected ST-segment elevation preceded hemodynamic collapse in an asymptomatic patient.
Perioperative monitor shows progressive ST-segment elevation
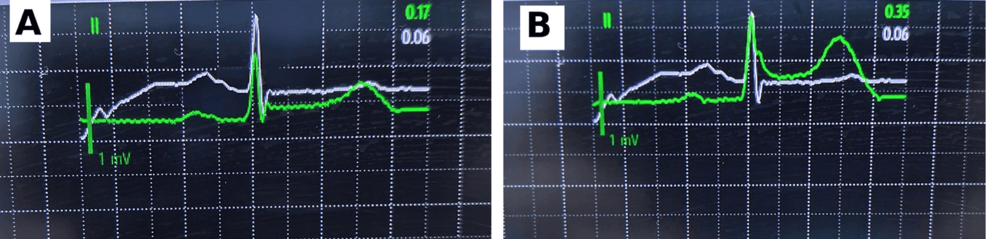
Surgery began at 09:00 following spinal anesthesia administered at 08:10 with 2.0 mL of 0.5% hyperbaric ropivacaine, which achieved a T10 sensory block by 08:20. Clopidogrel had been withheld for one week prior to the hospital admission, though accessible medical records did not document who recommended the discontinuation or whether preoperative aspirin was continued. At 09:32, the perioperative monitor displayed progressive ST-segment elevation. Review of the stored ST-analysis showed lead II values increasing from approximately 0.17 mV at 09:33:06 to 0.35 mV at 09:37:06. An anesthesia nurse recognized the abnormality, verified the monitor finding, and immediately notified the clinical team, prompting an urgent cardiology consultation at approximately 09:33. By 09:34, the patient’s heart rate and blood pressure began to drop, leading the medical team to administer intravenous nitroglycerin, norepinephrine, and dopamine while establishing invasive arterial pressure monitoring.
Patient suffers ventricular fibrillation during emergency transfer
An urgent 12-lead electrocardiogram performed at approximately 10:15 confirmed an acute inferior myocardial infarction. Emergency transfer from the operating room pathway began at approximately 10:40, but between 10:41 and 10:45, the patient suffered ventricular fibrillation during transit to the catheterization laboratory. Nursing staff performed cardiopulmonary resuscitation and delivered electrical defibrillation at 200 J per attempt. Each shock yielded only transient rhythm recovery that degenerated back into ventricular fibrillation after roughly 30 to 40 seconds, until coronary reperfusion was achieved. An organized rhythm was successfully documented at approximately 10:56.
Medical team treats right coronary artery occlusion
Coronary angiography revealed an acute proximal-to-mid right coronary artery occlusion with thrombus at the site of a stent implanted previously. Initial balloon angioplasty left substantial residual stenosis and thrombus estimated at 80% to 90%. To treat this, the medical team administered 6 mL of intracoronary tirofiban and deployed an additional 2.75 x 29 mm drug-eluting stent. Final angiographic imaging confirmed TIMI grade 3 flow with roughly 30% residual stenosis. Post-procedure antithrombotic therapy consisted of 300 mg of aspirin, 180 mg of ticagrelor, tirofiban, and 12,500 U of intravenous heparin sodium.
Blood tests track severe myocardial injury and recovery
Postoperative blood tests tracked severe myocardial injury followed by gradual improvement. On postoperative day 1, troponin T exceeded 50 ng/mL, CK-MB measured 130.51 ng/mL, myoglobin reached 400.64 mg/mL, and BNP registered 8994.37 ng/mL. By postoperative day 5, troponin T peaked at 4056 ng/mL, while myoglobin dropped to 76.60 mg/mL and BNP to 3481 ng/mL. On postoperative day 9, troponin T decreased to 900 ng/mL, myoglobin fell to 50.90 mg/mL, and BNP declined to 3187 ng/mL. The patient experienced no major bleeding, blood transfusions, or neurological complications, and successfully ambulated before being discharged on postoperative day 15.
Frequently Asked Questions About Perioperative Stent Thrombosis
What caused the acute coronary occlusion during hip surgery?
Coronary angiography revealed an acute occlusion with thrombus at the exact location of a right coronary artery stent, a complication heightened by the perioperative interruption of antiplatelet medication and surgical stress responses.
How was the ischemic event initially detected in the operating room?
An anesthesia nurse recognized progressive ST-segment elevation on the continuous electrocardiographic monitor, verified the finding, and immediately escalated the concern to initiate a multidisciplinary emergency response before hemodynamic collapse occurred.
What medications were administered after the emergency stent placement?
Following successful angioplasty and drug-eluting stent implantation, the patient received a regimen of 300 mg of aspirin, 180 mg of ticagrelor, intracoronary tirofiban, and 12,500 U of intravenous heparin sodium.
Related reading