Cardiovascular disease remains a leading cause of preventable death worldwide, yet the tools used to predict it often fail the populations that need them most.
A new narrative review published in Cureus maps the gap between artificial-intelligence promise and clinical reality in resource-limited settings, concluding that no randomized trial has yet shown AI-supported primary prevention reduces first cardiovascular events in those environments. The review, which searched PubMed through October 31, 2026, argues that algorithmic accuracy alone cannot close gaps in medication access, laboratory capacity, or follow-up continuity.
Conventional risk scores such as Framingham and WHO charts already disagree on who counts as high risk. A cross-sectional study in rural Andhra Pradesh, India, found the WHO score classified fewer people as high risk than Framingham or Australian tools, but without outcome data it could not prove whether the WHO model underestimated true risk, Cureus reported.
In the same cohort, only 9% to 12% of high-risk adults were on lipid-lowering or antihypertensive therapy. Across 41 low- and middle-income countries, statin use for primary prevention hovered at 8.0%, and hypertension control reached roughly 10%, with the largest drop-off occurring between blood-pressure measurement and diagnosis.
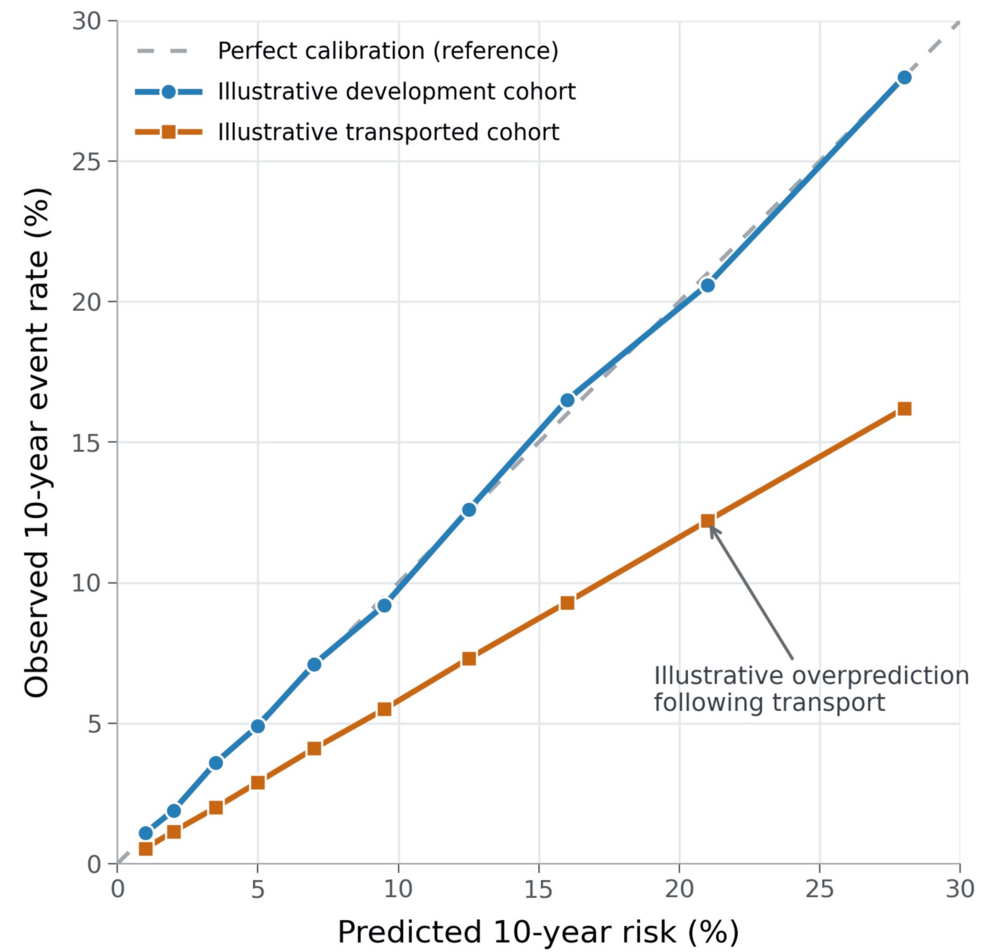
AI models have largely demonstrated improved discrimination — ranking patients by risk — within development cohorts drawn from well-resourced health systems. The review notes that discrimination, measured by the area under the receiver operating characteristic curve, is not the same as calibration, which checks whether predicted probabilities match observed event rates.
An American Heart Association scientific statement previously warned that algorithm development must connect to meaningful patient benefit. The Cureus authors frame prevention as a shared workflow across pathology, pharmacology, and community medicine, asking at each step whether an AI tool changes a clinical action in a way that is affordable, reliable, and beneficial.
A randomized controlled study from Indonesia, published separately in the Journal of Medical Internet Research, tested an AI-based clinical decision support prototype against automated decision support and no support. In a three-way, within-subject design, 102 general practitioners from all seven Indonesian geographical regions assessed nine clinical vignettes.
The AI prototype improved correct risk assessment by 27% and appropriate management decisions by 18% compared with no support, according to the JMIR study. Decision-making time increased modestly. The authors cautioned that the prototype represented contemporary machine-learning calculators incorporating additional predictors, not a deployed system, and that vignette performance may not translate to real-world outcomes.
The European Commission’s Joint Research Centre reached a similar conclusion in a 2024 report surveying the cardiovascular AI continuum from prevention to health-system optimization. The JRC identified evidence generation, regulatory harmonization, equitable access, and clinical integration as prerequisites for responsible deployment, noting that lessons from cardiovascular care will transfer to other non-communicable diseases. Neither the Indonesian trial nor the JRC report demonstrated a reduction in hard cardiovascular events.
The Cureus review proposes a staged, clinician-supervised framework for implementation in resource-limited settings, beginning with external validation of transported models against local event rates, followed by prospective studies measuring process changes, risk-factor control, and eventually clinical outcomes. The relevant test, it argues, is whether an AI tool narrows a specific gap better than a simpler, locally validated chart.
What the evidence shows so far
| Setting | Intervention | Primary Finding | Limitation |
|---|---|---|---|
| Rural Andhra Pradesh, India | Comparison of Framingham, WHO, Australian risk scores | WHO score classified fewer as high risk; 9–12% of high-risk adults on preventive meds | No outcome data to judge underestimation |
| 41 LMICs | Statin eligibility vs. use | 8.0% of eligible adults reported statin use | Cross-sectional; self-reported adherence |
| Europe (JRC report) | Policy review of cardiovascular AI continuum | Identified evidence, regulation, access, integration gaps | No new trial data; policy-level analysis |
No trial proves AI prevents first cardiovascular events
Has any randomized trial proven AI prevents first heart attacks or strokes in low-resource settings?
Why do conventional risk scores disagree in the same population?
Different equations weight risk factors differently and were derived in distinct cohorts. The Andhra Pradesh study showed Framingham, WHO, and Australian tools produced substantially different high-risk proportions, but without follow-up events it is impossible to know which classification matches reality.
What did the Indonesian AI decision-support study actually measure?
It measured correct risk assessment and management decisions — prescribing aspirin, statins, antihypertensives, and referrals — across nine clinical vignettes. It did not measure patient outcomes, adherence, or long-term clinical events.
What does the European JRC report recommend for cardiovascular AI?
The report calls for stronger evidence generation, regulatory harmonization, equitable access frameworks, and clinical integration standards, arguing that cardiovascular care can set the template for responsible AI across non-communicable diseases.
Cureus, the journal publishing the review, began as PeerEMed in 2009 and adopted its current name in December 2012; its founding editors-in-chief are John R. Adler of Stanford University and Alexander Muacevic of LMU Munich. It joined the Springer Nature group in December 2022 and is indexed in PubMed Central, though Clarivate removed it from the Master Journal List in 2025, ending its Web of Science coverage and impact factor.
What is the proposed next step for AI in resource-limited prevention?
The Cureus authors propose a staged framework: external validation against local event rates, prospective process studies, risk-factor control trials, and finally outcome trials — all under clinician supervision and judged against simpler, locally validated alternatives.
Related reading