A 36-year-old woman with a history of triple-negative breast cancer developed acute fibrinous pericarditis 42 weeks after her final dose of pembrolizumab, a case that shows the long-term risks of immunotherapy.
Despite having completed her treatment nine months prior, the patient presented with life-threatening complications that blurred the lines between cancer recurrence and immune-related toxicity.
Patient Presents with Hemodynamic Collapse and Pericardial Effusion
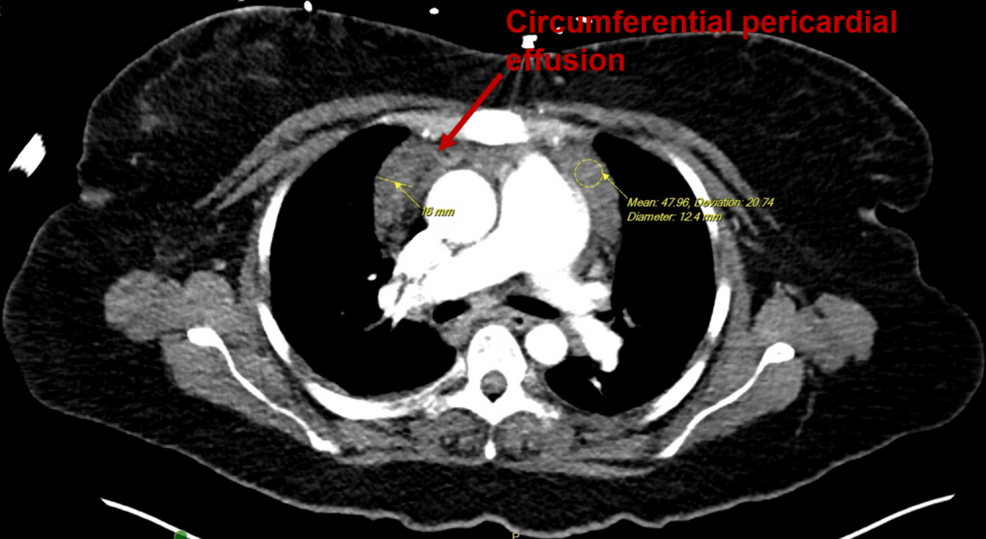
The patient, a BRCA1 mutation carrier, arrived at the hospital following a four-day descent into chest pain, fever, malaise, and dyspnea. Her clinical state was critical: she exhibited tachycardia of 150 beats per minute and hypotension of 92/36 mmHg. Imaging via computed tomography and echocardiography identified a 1.8 cm circumferential intermediate-density pericardial effusion.
Laboratory markers signaled systemic inflammation, with a C-reactive protein of 97.2 mg/L, an erythrocyte sedimentation rate of 64 mm/h, and significant leukocytosis. According to Cureus, the clinical picture was too ambiguous for non-invasive methods; doctors could not distinguish whether the effusion was malignant, autoimmune, or infectious. This uncertainty necessitated invasive tissue sampling.
Emergency Surgical Intervention
Driven by the patient’s hemodynamic instability, surgeons performed an open subxiphoid pericardial window and partial pericardiectomy. The procedure required the resection of the xiphoid and the removal of a 4×8 cm island of pericardium to ensure continuous drainage. Post-operative pathology eventually cleared the primary fear of malignancy, confirming instead acute fibrinous pericarditis.
Management shifted to a regimen of ibuprofen, colchicine, and a hydrocortisone taper. While this led to symptomatic improvement, the recovery was not linear. Within two weeks of discharge, the patient returned with a small-to-moderate loculated pericardial effusion, which required conservative management by cardiology and critical care teams.
The Timeline of Late-Onset Toxicity
The timing of this event—42 weeks post-immunotherapy—falls squarely into the category of “late” immune-related adverse events (irAEs). The American Society of Clinical Oncology defines late irAEs as those manifesting at least six months after the cessation of immunotherapy, as reported by Cureus. While most toxicities emerge during active treatment, the window for cardiovascular complications following pembrolizumab can extend up to 54 weeks.
Immune-Mediated Inflammation Requires Surgical Intervention for Diagnosis
The initial suspicion of malignancy was rooted in the patient’s history of stage IIA triple-negative breast cancer, as pericardial effusions in oncology patients are frequently linked to metastatic disease. However, the inflammation was confirmed to be immune-mediated.
While surgical intervention is rarely required for ICI-associated pericardial disease, it was deemed essential here due to the patient’s instability and the urgent need for a definitive diagnosis. Doctors must determine whether the patient's recent return with a loculated effusion indicates a permanent change in her clinical trajectory.