Cardiogenic Shock After Rituximab Treatment
A 64-year-old woman developed cardiogenic shock seven days after receiving her second dose of rituximab for immune thrombotic thrombocytopenic purpura, Cureus reported.
The severe cardiac complication unfolded alongside a serum sickness-like reaction, forcing doctors to stop the monoclonal antibody therapy and provide emergency life support.
The patient arrived at the emergency department with acute chest pain, respiratory distress, and profound asthenia.
Her medical history included systemic lupus erythematosus diagnosed in 1989 and Sjögren’s syndrome diagnosed in 2002. She also had a documented history of immune thrombotic thrombocytopenic purpura (iTTP) originally diagnosed in 2015, which had been managed with therapeutic plasma exchange and periodic monitoring.
Rituximab infusions managed ADAMTS13 activity levels
The patient experienced a biological relapse in 2024 when her ADAMTS13 activity dropped to 12 percent. This drop led doctors to prescribe a standard four-week course of rituximab, which successfully raised her enzyme activity and was well tolerated without immediate adverse events.
She returned for follow-up in January 2026, showing an asymptomatic drop in ADAMTS13 activity down to 6.9 percent.
In line with updated 2025 guidelines from the International Society on Thrombosis and Haemostasis, clinicians initiated preemptive rituximab to prevent a clinical relapse. She received her first infusion fourteen days before her eventual hospital admission and her second infusion seven days prior.
Emergency admission for worsening chest pain and cardiac failure
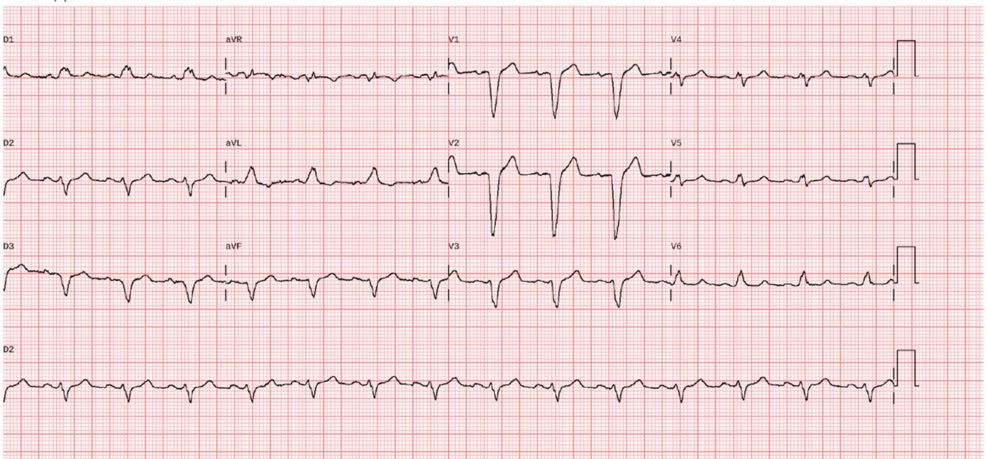
Six days after her second infusion, the patient sought care at an emergency department for arthralgia, but doctors discharged her with symptomatic treatment after initial blood tests and chest X-rays appeared normal. She returned the following day with worsening chest pain, dyspnea, and somnolence. Vital signs revealed a blood pressure of 92/42 millimeters of mercury, a capillary refill time exceeding four seconds, and a venous lactate level of 3 millimoles per liter.
Point-of-care echocardiography revealed a left ventricular ejection fraction of just 5 to 10 percent, accompanied by diffuse hypokinesis and a sub-aortic velocity time integral of 8 centimeters. Doctors admitted her to the intensive care unit and started dobutamine and norepinephrine support. Computed tomography pulmonary angiography and coronary angiography ruled out pulmonary embolism and coronary artery blockages.
Serum Sickness Diagnosis and Recovery
Two days after admission, the patient developed an erythematous macular rash and diffuse arthromyalgia, accompanied by complement consumption with a C3 level of 0.76 grams per liter and a C4 level of 0.04 grams per liter. Clinicians diagnosed a serum sickness-like reaction and immediately withheld all further rituximab doses while starting intravenous methylprednisolone at 80 milligrams per day.
Inotropic and vasopressor support was completely withdrawn seventy-two hours after admission. A cardiac magnetic resonance imaging scan performed on day five showed no myocardial tissue abnormalities, acute myocarditis, or Takotsubo syndrome. By day eight, bedside echocardiography showed her ejection fraction recovering to 40 to 50 percent, and she was discharged home on oral corticosteroids.
Frequently Asked Questions
What condition was being treated with rituximab?
The patient was receiving rituximab as a preemptive treatment for immune thrombotic thrombocytopenic purpura after routine blood tests showed severely low ADAMTS13 activity at 6.9 percent.
What symptoms indicated heart failure on admission?
The patient presented with acute chest pain, dyspnea, profound asthenia, a blood pressure of 92/42 millimeters of mercury, and a left ventricular ejection fraction estimated between 5 and 10 percent.
Keep reading