Prostate Cancer Imaging Cost Analysis Favors Piflufolastat F 18
A health economic evaluation published in Cureus indicates that the prostate-specific membrane antigen (PSMA) PET radiotracer piflufolastat F 18 delivers greater clinical effectiveness and lower long-term costs than competing diagnostic tools for men with prostate cancer in the United States. Prostate cancer ranks as the second most commonly diagnosed malignancy and the second leading cause of cancer mortality among men domestically, with an estimated 299,010 new cases and 35,250 deaths projected for 2024. Accurately staging the disease at initial diagnosis or upon biochemical recurrence remains critical for patient survival.
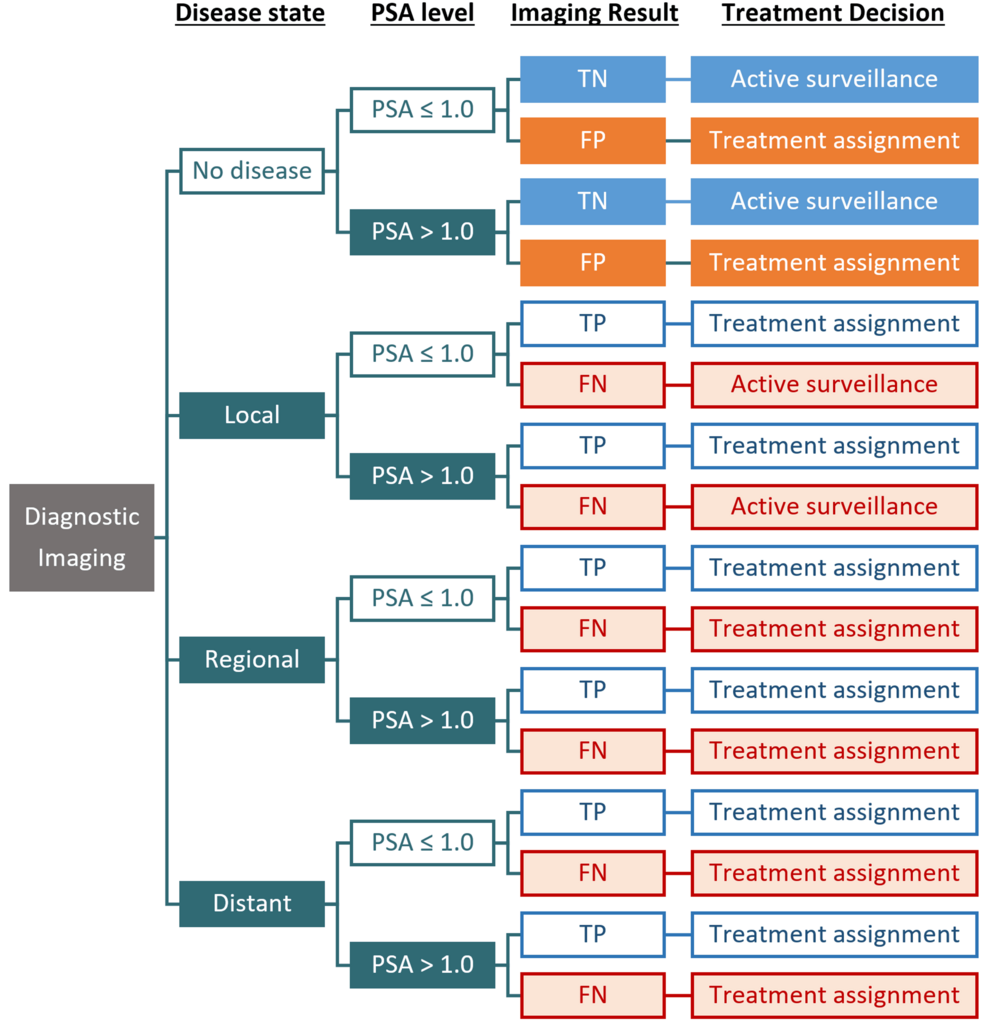
The cost-effectiveness analysis utilized a hybrid economic model consisting of a decision tree combined with a Markov model to evaluate diagnostic and treatment pathways over a lifetime horizon. The model evaluated direct healthcare costs from a United States third-party payer perspective, reflecting a mix of commercial and Medicare payers. Inputs drew from clinical trials including OSPREY, CONDOR, and LIGHTHOUSE, alongside public data and published literature. All costs were standardized in 2021 US dollars using the US Bureau of Labor Statistics Consumer Price Index, according to PMC data.
Comparative Effectiveness Across Diagnostic Modalities
Over a lifetime horizon, piflufolastat F 18 demonstrated the highest effectiveness in life-years and quality-adjusted life-years compared to alternative imaging options. According to the Cureus findings, piflufolastat F 18 yielded 6.79 life-years and 5.23 QALYs. In comparison, PMC reported slightly different modeled totals of 6.80 life-years and 5.33 QALYs for the same tracer. Comparators across the evaluations ranged from 6.50 to 6.76 for life-years and 4.92 to 5.30 for QALYs.
When evaluated against flotufolastat F 18, gallium 68-PSMA-11, and conventional imaging—which includes bone scans, computed tomography, and magnetic resonance imaging—piflufolastat F 18 proved more cost-effective. The Cureus analysis calculated incremental cost-effectiveness ratios of $762 per incremental QALY compared to flotufolastat F 18, $91,985 compared to PSMA 11, and $138,434 compared to conventional imaging. Using a willingness-to-pay threshold of $150,000, piflufolastat F 18 generated the greatest net monetary benefit at $588,702, with corresponding probability estimates of being cost-effective ranging from 71.0% to 100.0% depending on the specific comparator.
Clinical Trials Informing Diagnostic Accuracy
The economic model relied on diagnostic accuracy inputs derived from major clinical trials investigating PSMA PET tracers. The OSPREY and CONDOR clinical trials provided data to inform the diagnostic accuracy inputs for the piflufolastat F 18 cost-effectiveness model. These trials established that PSMA-targeted PET radiotracers offer superior sensitivity and specificity compared to conventional imaging modalities, which often miss regional or distant metastases.
Clinical guidelines recommend thorough initial staging because missing metastatic disease leads to suboptimal treatment selection and poorer survival outcomes. While five-year relative survival exceeds 99% for localized or regional prostate cancer, it drops sharply to 34% for distant metastatic disease. Up to 50% of patients treated initially with curative intent experience biochemical recurrence within 10 years, making accurate localization essential before selecting salvage therapies such as radiation or androgen deprivation therapy.
Future Research and Regulatory Landscape
The regulatory environment for prostate cancer diagnostics has expanded rapidly since the FDA approved fluciclovine F 18 in 2016, followed by PSMA 11 in 2020 and 2021, piflufolastat F 18 in 2021, and flotufolastat F 18 in 2023. Professional groups continue to refine disease management standards. The Prostate Cancer Working Group 4 has updated its recommendations to emphasize detailed baseline assessments of all PSMA-positive loci—including the prostate bed, lymph nodes, bones, and visceral organs—during clinical trials and standard clinical evaluations.
While expanded use of PSMA PET imaging in clinical trials aims to improve monitoring and trial design, these changes point toward broader integration into routine clinical practice. Payers and providers continue to evaluate these economic models to determine coverage policies as new radiotracers enter the diagnostic market.
Related reading