Bilateral Facial Palsy and Cavernous Sinus Lesions in Neurosarcoidosis
A 40-year-old man who developed sequential bilateral facial nerve palsy alongside right abducens nerve palsy was diagnosed with possible neurosarcoidosis, Cureus reported in a published case study. The patient presented to clinicians in August 2026 with right-sided lower motor neuron facial weakness and an inability to move his right eye outward, before developing contralateral left facial weakness the following day.
Neurosarcoidosis represents a rare neurological manifestation of systemic sarcoidosis, occurring in roughly 5% to 15% of patients with the granulomatous disorder. While facial nerve palsy is a recognized complication, simultaneous or sequential bilateral involvement is uncommon, appearing in only 15% to 25% of neurosarcoidosis cases according to MDPI, which reviewed related clinical presentations involving a 52-year-old female patient.
Clinical Evaluation and Diagnostic Findings
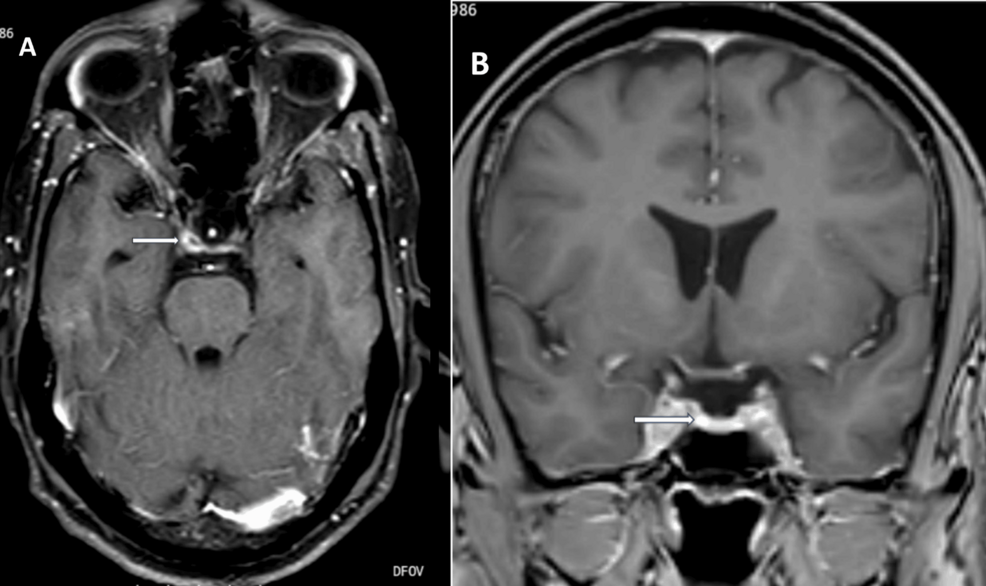
Initial neurological examinations revealed that the male patient could not completely close either eye, resulting in bilateral scleral show characteristic of lagophthalmos, alongside bilateral grade I papilledema observed during ophthalmological evaluation. Contrast-enhanced magnetic resonance imaging demonstrated asymmetric soft-tissue thickening and abnormal enhancement restricted to the right cavernous sinus and extending toward the right orbital apex.
Systemic evaluations via high-resolution computed tomography of the chest showed prominent bilateral hilar and mediastinal lymphadenopathy, including a subcarinal lymph node measuring 3.4 centimeters, without significant pulmonary parenchymal abnormalities. Laboratory tests revealed an elevated serum angiotensin-converting enzyme level of 85.1 U/L against a reference range of 12 to 68 U/L, and an elevated erythrocyte sedimentation rate of 41 mm/hour.
Fluid analysis shows normal results despite cardiac history
Cerebrospinal fluid analysis showed clear and colorless fluid with a normal cell count of 4 cells/mm³, protein at 43.05 mg/dL, and glucose at 59 mg/dL. Cytology tests, acid-fast bacilli smears, and bacterial cultures returned negative results for infectious etiologies. The patient’s medical history included an episode of symptomatic monomorphic ventricular tachycardia in March 2026 that required direct-current cardioversion for palpitations, dizziness, and syncope.
Although the prior ventricular arrhythmia pointed toward potential cardiac involvement of sarcoidosis, dedicated cardiac magnetic resonance imaging or fluorodeoxyglucose positron emission tomography was not performed, leaving cardiac sarcoidosis unconfirmed. Clinicians categorized the case as possible neurosarcoidosis under the Neurosarcoidosis Consortium Consensus Group framework due to the presence of multiple cranial neuropathies, cavernous sinus-orbital apex lesions, and systemic lymphadenopathy without confirmed tissue biopsy.
Patient receives corticosteroid therapy for disease management
Medical management for the patient involved five days of intravenous methylprednisolone pulse therapy, followed by oral corticosteroids administered at approximately 1 mg/kg/day with a planned gradual taper.
Concurrently, MDPI reported on a separate patient case involving a 52-year-old woman with simultaneous bilateral facial nerve palsy and systemic lymphadenopathy who achieved long-term disease remission over a three-year follow-up period using low-dose prednisone therapy.
Frequently Asked Questions About Bilateral Facial Palsy in Neurosarcoidosis
What defines sequential bilateral facial nerve palsy in neurosarcoidosis?
Sequential bilateral facial nerve palsy involves the loss of facial nerve function on one side followed by contralateral facial weakness within a 30-day window. In this case, the patient developed left-sided facial weakness one day after presenting with right-sided lower motor neuron facial weakness and right abducens nerve palsy.
Why was a cavernous sinus lesion unable to explain all cranial nerve deficits?
The sixth cranial nerve traverses the cavernous sinus, which explained the right abducens nerve palsy and the enhancing skull-base lesion seen on magnetic resonance imaging. However, the facial nerve follows a separate anatomical course, meaning a unilateral cavernous sinus lesion could not account for the patient’s sequential bilateral facial nerve involvement.
What criteria established the diagnosis of possible neurosarcoidosis?
In accordance with the Neurosarcoidosis Consortium Consensus Group framework, the diagnosis relied on clinical cranial neuropathies, neuroimaging evidence of cavernous sinus-orbital apex enhancement, elevated serum angiotensin-converting enzyme levels of 85.1 U/L, and extracranial thoracic lymphadenopathy while excluding alternative infectious causes.