A Rare Cardiac Collapse
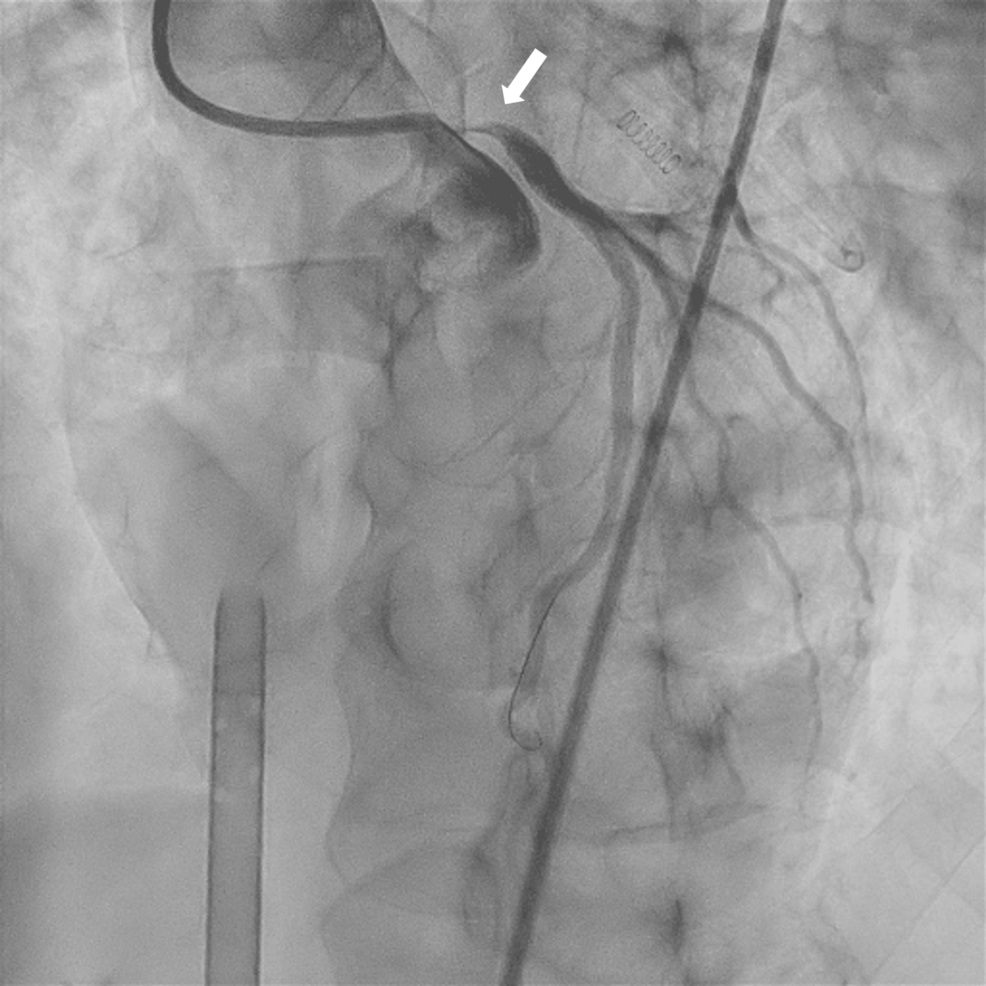
A 49-year-old previously healthy man suffered a sudden cardiopulmonary arrest during exercise. Bystander cardiopulmonary resuscitation and an automated external defibrillator shock restored circulation; however, recurrent ventricular fibrillation required extracorporeal membrane oxygenation (ECMO) support. Angiography unveiled a 99% stenosis at the ostium of the left main coronary artery.
Challenging the Atherosclerotic Norm
In most patients, a blockage of this severity is attributed to standard atherosclerosis. However, the patient’s age and the isolated nature of the lesion prompted his clinical team to look for inflammatory causes. After ruling out systemic inflammatory vasculopathies—confirmed by normal immunoglobulin G4 levels and a lack of systemic vascular inflammation—doctors turned to serological testing. The results revealed positive rapid plasma reagin (RPR) and Treponema pallidum hemagglutination assays, raising suspicion for coronary ostial stenosis associated with syphilitic arteritis.
Imaging and Histopathological Evidence
To distinguish this lesion from conventional plaque, physicians utilized intravascular ultrasound (IVUS). The imaging showed a predominantly fibrous lesion with minimal calcification or lipid content, a profile atypical for conventional atherosclerosis. To obtain tissue samples, physicians performed directional coronary atherectomy (DCA) before inserting a stent. Histopathological evaluation revealed fibrous intimal thickening without cholesterol deposition or features of typical atherosclerotic plaque. This synthesis of imaging and clinical data suggested a diagnosis of suspected cardiovascular syphilis.
The medical literature highlights the unpredictable nature of syphilitic cardiovascular involvement. Another report details a 51-year-old man who presented with syncope caused by syphilitic aortitis. Unlike the 49-year-old patient, this individual showed circumferential ascending aortic wall thickening and inflammation, eventually requiring coronary artery bypass grafting. These cases illustrate that while syphilitic aortitis is rare in the antibiotic era, it should still be considered as a potential cause of coronary ostial stenosis in patients without coronary risk factors.
Clinical Insights on Modern Syphilitic Care
Treatment for the patient required a two-pronged approach: the infection was addressed with intramuscular benzathine penicillin G administered once weekly for three consecutive weeks, while the structural coronary damage was repaired with a drug-eluting stent. The patient’s case suggests that coronary ostial involvement can manifest as a localized issue or an early stage of cardiovascular syphilis, and that the diagnosis should not be dismissed solely because classical manifestations of syphilitic aortitis are absent.
Related reading