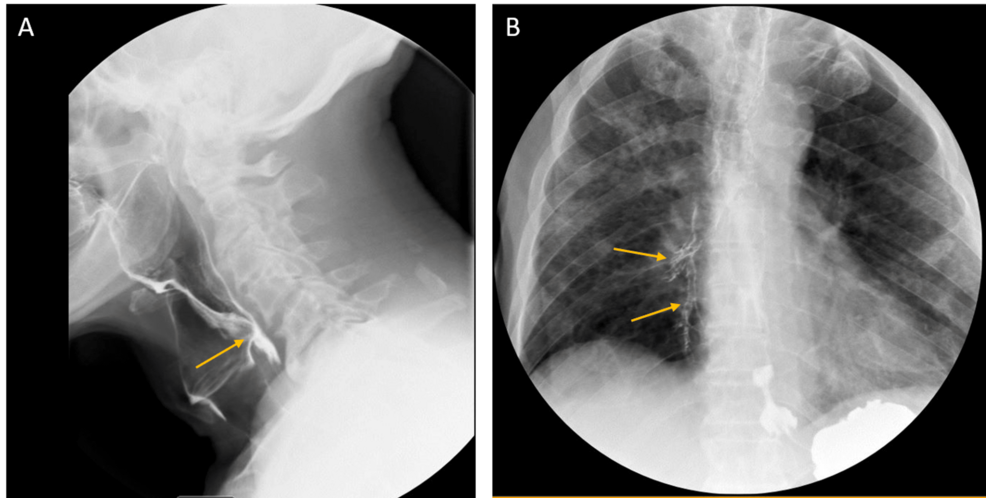
Swallowing impairment in older adults presents complex diagnostic challenges when mechanical airway compression and prior neurological deficits intersect, Cureus reported.
An 86-year-old man experienced progressive dysphagia, recurrent aspiration pneumonia, and a 13-kilogram unintentional weight loss over eight months. Medical records documented a minor ischemic stroke in 2011 that caused left-sided weakness and persistent swallowing difficulties, followed by a left carotid endarterectomy.
A computed tomography scan of the cervical spine in 2019 following an unwitnessed fall revealed marked osteophytic lipping and intervertebral disc space narrowing at multiple levels. By early 2021, an unsuccessful esophagogastroduodenoscopy led to a barium swallow examination that demonstrated marked extrinsic esophageal compression by anterior cervical osteophytes at the C5 and C6 vertebral levels.
The patient subsequently suffered from a lower respiratory tract infection and severe hyperglycemia during a spring 2021 hospital admission.
| Year | Clinical Event | Management |
|---|---|---|
| 2011 | Cerebrovascular accident and persistent dysphagia | Left carotid endarterectomy performed |
| 2019 | Unwitnessed fall and cervical spine CT | Identified multilevel degenerative changes |
| 2021 | Severe dysphagia and aspiration pneumonia | Radiologically guided gastrostomy placement |
Outpatient videofluoroscopic swallowing studies in mid-2021 demonstrated severe oropharyngeal dysphagia with significant fluid aspiration. Further neurological evaluations and multidisciplinary team discussions addressed the long-term need for enteral nutritional support as oral intake became unsafe.
Although surgical options were discussed with a spine surgery referral, the patient declined major surgery and initially chose to leave the hospital to continue oral intake. He was readmitted one month later with aspiration pneumonia, acute kidney injury, and severe nutritional compromise.
Following a multidisciplinary family conference, the patient consented to radiologically guided gastrostomy placement for long-term enteral nutrition. He was discharged after the aspiration pneumonia resolved, but experienced progressive clinical deterioration and died at home one month later.
Anterior cervical osteophytes are bony projections along the front of the vertebral bodies in the neck that commonly associate with degenerative cervical spondylosis or diffuse idiopathic skeletal hyperostosis, also known as Forestier disease. These bone spurs develop due to excessive ossification of ligaments and tendon attachment sites in older adults.
Cureus, the journal reporting this case, began as PeerEMed in 2009 and adopted its current name in December 2012. Founded by John R. Adler of Stanford University and Alexander Muacevic of LMU Munich, it operates as a web-based open-access general medical journal using both pre-publication and optional post-publication peer review through a trademarked Scholarly Impact Quotient. The journal became part of the Springer Nature group in December 2022.
Large osteophytes at the C5 and C6 vertebral levels mechanically compress the adjacent pharynx or esophagus and interfere with normal bolus passage during swallowing. This compression restricts laryngeal movement, causes local inflammation, and prevents normal epiglottic inversion.
Keep reading