Propofol Infusion Syndrome Triggered in 21-Year-Old Trauma Patient
A 21-year-old man developed propofol infusion syndrome (PRIS) after receiving a prolonged propofol infusion for refractory status epilepticus. The patient experienced acute cardiovascular collapse, severe metabolic acidosis, and multiorgan failure four days after starting the sedative. Medical teams immediately discontinued the propofol and deployed aggressive organ support, including simultaneous dual-circuit continuous renal replacement therapy and high-dose euglycemic insulin.
Status Epilepticus Treatment and Four-Day Escalation
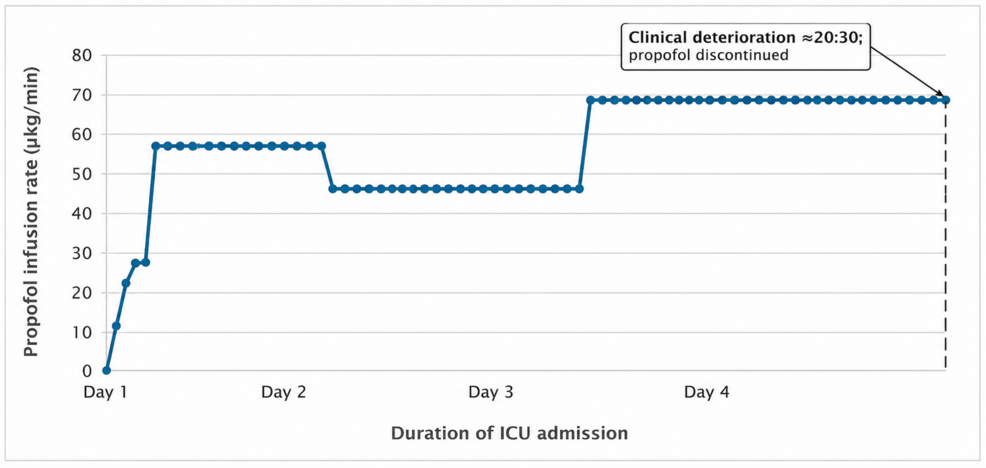
The patient arrived at the intensive care unit following an unwitnessed fall and ongoing seizure activity, compounding a severe traumatic brain injury he sustained months earlier that required a decompressive craniectomy. Clinicians initiated a propofol infusion alongside fentanyl and multiple antiepileptic medications to manage persistent epileptiform activity observed on continuous electroencephalography. Medical records show the mean infusion rate reached 56.8 µg/kg/min over four days. Within the 35 hours preceding his clinical deterioration, the infusion rate increased to a final peak of 68.5 µg/kg/min.
Rapid Clinical Deterioration and Laboratory Findings
On the fourth day in the intensive care unit, the patient suffered an abrupt decline characterized by profound bradycardia, rapidly progressive cardiogenic shock, and brown urine indicating severe muscle breakdown. Laboratory tests revealed a lactate spike to 10.3 mmol/L, a worsening high-anion-gap metabolic acidosis with a pH of 7.17, and a creatine kinase level of 62,600 IU/L that later peaked at 931,000 IU/L on the sixth day. Additional findings included hypertriglyceridemia at 11.5 mmol/L, hyperkalemia at 6.7 mmol/L, and acute kidney injury with creatinine jumping from 89 µmol/L at admission to 497 µmol/L. Bedside echocardiography demonstrated severe global left ventricular dysfunction with an ejection fraction of 20%, while serial electrocardiograms traced a rapid progression of conduction abnormalities and QTc prolongation exceeding 500 milliseconds.
Multimodal Critical Care Intervention and Recovery
Medical staff ceased the propofol infusion within five to 10 minutes of hemodynamic instability. To counteract the mixed shock state, physicians administered noradrenaline, adrenaline, dobutamine, and vasopressin. Due to the severity of the metabolic acidosis and rhabdomyolysis, clinicians placed two separate dialysis catheters to operate two continuous renal replacement therapy circuits simultaneously for heightened solute clearance. High-dose euglycemic insulin and enteral L-carnitine were added to address suspected mitochondrial dysfunction and myocardial failure. Hemodynamic and metabolic parameters began to stabilize within six hours.
Frequently Asked Questions
What is propofol infusion syndrome?
Propofol infusion syndrome is a condition involving acute cardiovascular collapse, metabolic acidosis, rhabdomyolysis, and multiorgan failure, associated with prolonged propofol exposure.
Why did the patient require prolonged propofol sedation?
The 21-year-old man suffered from refractory status epilepticus following an unwitnessed fall, necessitating mechanical ventilation and continuous sedation to control persistent seizure activity.
How did clinicians manage the multi-organ failure?
Upon stopping the propofol, the medical team administered vasoactive infusions, high-dose euglycemic insulin, and enteral L-carnitine. They also utilized a dual-circuit continuous renal replacement therapy setup to aggressively clear toxins and correct severe acidosis.