Silent ST-Elevation Myocardial Infarction Discovered in an 82-Year-Old Patient
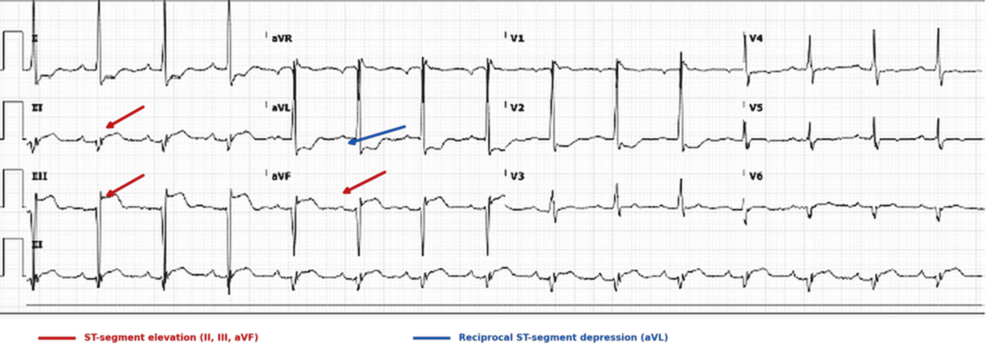
An 82-year-old man presenting to the emergency department with dizziness and transient lower-extremity weakness was found to have an acute inferior ST-elevation myocardial infarction (STEMI) that produced no chest pain, Cureus reported. The patient, who had a history of hypertension, dyslipidemia, dementia, and coronary artery disease, ran out of his antihypertensive and lipid-lowering medications and took them inconsistently. Triage electrocardiography unexpectedly revealed inferior ST-segment elevation with reciprocal depression, prompting a code STEMI activation 31 minutes after the tracing was completed.
Stent restores blood flow after total coronary occlusion
High-sensitivity troponin I levels rose from an initial critical value of 172 pg/mL to a peak of 120,968 pg/mL on hospital day 2. Emergent coronary angiography revealed total occlusion of an aneurysmal proximal-to-mid right coronary artery alongside multivessel disease involving the left coronary system. Interventional cardiologists treated the culprit lesion with a single drug-eluting stent to restore normal coronary blood flow, while managing residual multivessel disease medically with planned surgical revascularization. The patient recovered without hemodynamic compromise.
Diagnostic Challenges in Elderly and Cognitive-Impaired Patients
Silent or painless myocardial infarction remains a diagnostic challenge, particularly in older adults and those with cognitive impairment who cannot report classic anginal symptoms. Historical registry data indicate that roughly one-third of patients with confirmed myocardial infarction present without chest pain.

While the 82-year-old patient described in the Cureus report presented with dizziness and weakness due to lapsed medication adherence, alternative presentations appear in medical literature under similar clinical classifications. A separate case reported by NAMS Annals detailed a 64-year-old male diabetic ex-serviceman who presented with dizziness, a fall, and non-bilious vomiting. That patient experienced normal initial electrocardiograms before serial tracings revealed an inferior STEMI, highlighting how diabetic autonomic neuropathy can mask ischemic pain and lead clinicians to misattribute symptoms to benign causes.
Why the triage electrocardiogram review was delayed?
Why was the electrocardiogram not reviewed immediately in triage?
Several electrocardiograms were pending simultaneously in the triage queue, which delayed physician interpretation of the tracing from 16:59 until 17:30, at which point the STEMI code was activated.
What secondary conditions were identified during the initial hospital workup?
Initial laboratory results showed mild normocytic anemia with a hemoglobin level of 11.0 g/dL and an acute kidney injury attributed to prerenal azotemia, with serum creatinine rising to 1.55 mg/dL against a baseline of 1.19 to 1.23 mg/dL.
Worth a look