A 25-Year-Old Man Died After Tuberculosis Destroyed His Aortic Wall
A 25-year-old man from Nepal with longstanding renovascular hypertension and extensive arterial disease died of massive hemorrhage and shock after disseminated tuberculosis produced a destructive pseudoaneurysm in his aorta, Cureus reported. Autopsy confirmed necrotizing granulomatous disease in his lungs, kidneys and aortic wall, in a case the journal said highlights how hard it is to tell chronic large-vessel vasculitis apart from a superimposed aortic infection.
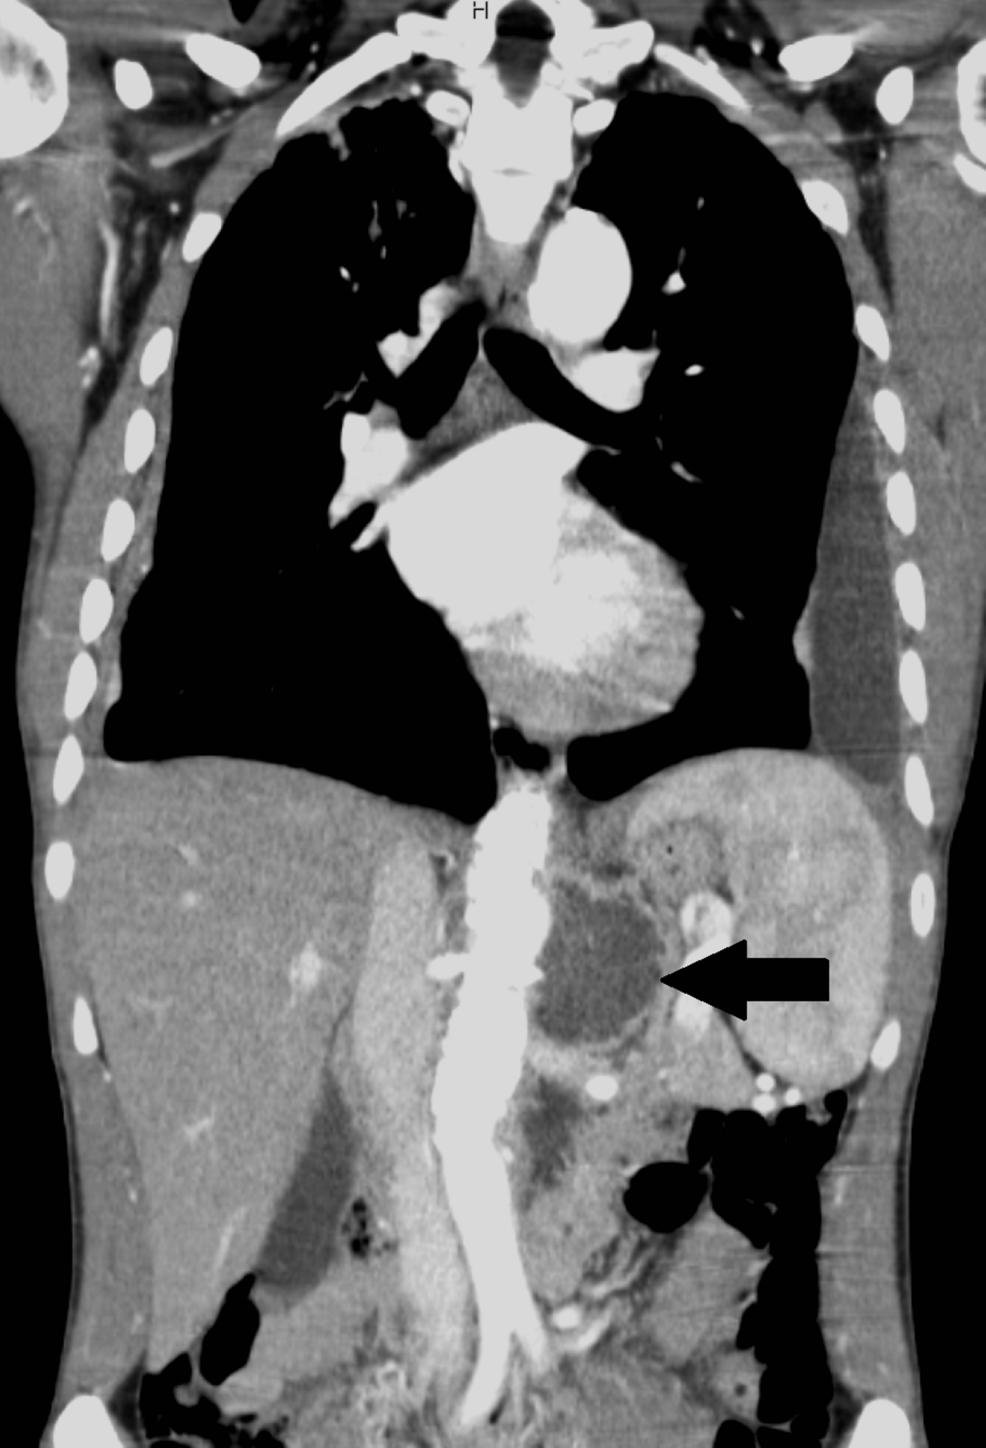
The patient, who had lived in Portugal for about four years and worked in agriculture, had been diagnosed with arterial hypertension secondary to renal artery stenosis at age 17 and had bilateral renal artery stents placed. When he presented to an emergency department with weeks of cough, fever, appetite loss and back pain, computed tomography angiography showed pulmonary tuberculosis, a heavily calcified “porcelain aorta,” and a large periaortic collection just below the celiac trunk that raised suspicion of a mycotic aneurysm or pseudoaneurysm.
Early-Onset Hypertension and Multivessel Disease Pointed to Takayasu Arteritis
Cureus reported that the combination of renovascular hypertension diagnosed at 17, critical stenosis of the celiac trunk, occlusion of the superior mesenteric artery, bilateral renal artery occlusion and extensive aortic calcification raised clinical suspicion of Takayasu arteritis, a chronic granulomatous vasculitis of the aorta and its major branches. The 2022 American College of Rheumatology/European Alliance of Associations for Rheumatology classification criteria provide a framework, Cureus noted, but were not developed as diagnostic criteria and should not be used alone to establish the diagnosis.
Imaging quantified the aortic threat: a second CTA measured the periaortic collection at 80 × 35 mm, with peripheral enhancement and disruption of the intimal calcifications, findings concerning for an infectious pseudoaneurysm. A transthoracic echocardiogram also showed severe dilated cardiomyopathy with a left ventricular ejection fraction of roughly 23%.
He Declined Surgery Nine Days Before the Fatal Rupture
Smear-positive pulmonary tuberculosis was confirmed microbiologically, and standard first-line therapy with isoniazid, rifampicin, pyrazinamide and ethambutol was started. About a month after admission, the patient was transferred to a tertiary center for vascular surgical assessment, but he declined further diagnostic investigations and surgical intervention, Cureus reported.
Nine days after that assessment, he developed sudden abdominal pain, then massive gastrointestinal hemorrhage, severe metabolic acidosis and refractory shock, deteriorating to cardiac arrest and death. Autopsy showed disseminated necrotizing granulomatous disease involving the lungs, kidneys and aortic wall, with transmural arteritis, neutrophilic infiltration, microabscess formation and tissue necrosis in the aorta.
TB and Takayasu Arteritis: An Association Without Proven Causation
A systematic review cited by Cureus found reports of active or latent tuberculosis among Takayasu arteritis patients but insufficient evidence that tuberculosis directly causes the vasculitis; proposed mechanisms include abnormal immune responses to mycobacterial antigens and cross-reactivity involving a 65-kDa heat shock protein of Mycobacterium tuberculosis. The journal noted that whether tuberculosis contributed to progression of this patient’s underlying vascular disease, or simply infected an already diseased aortic wall, cannot be determined from the available evidence.
The same uncertainty appears elsewhere in the literature: a case report published in the PMC-indexed journal described a 10-year-old Tunisian girl with Takayasu arteritis revealed by renovascular hypertension alongside pulmonary tuberculosis, and called her one of only a few published childhood-onset cases, underlining what that report termed the strong relationship between the two conditions — an association, not a proven causal link.
Questions Readers Ask About This Case
What is Takayasu arteritis?
It is a chronic granulomatous vasculitis that affects the aorta and its main branches, potentially causing stenosis, occlusion, aneurysm and renovascular hypertension. Cureus notes it primarily affects younger individuals, and the PMC-indexed report describes it as frequently seen in young women but also occurring in children.
Can tuberculosis infect the aorta itself?
Yes, though rarely. Cureus reports that tuberculous involvement of the aortic wall can cause destructive aortitis, mycotic aneurysm or pseudoaneurysm, with potentially fatal complications, and that management generally combines antituberculous therapy with definitive vascular treatment when feasible.
Why was the diagnosis so difficult in this patient?
Because the imaging overlapped: chronic large-vessel vasculitis and infectious aortitis can produce similar clinical and radiologic findings. Cureus reports that in this case the destructive periaortic lesion was temporally and pathologically tied to disseminated tuberculosis, while the early-onset, extensive arterial disease favored a pre-existing vasculopathy.
What did the autopsy establish?
It confirmed disseminated necrotizing granulomatous disease in the lungs, kidneys and aortic wall, with transmural aortitis, microabscesses and necrosis compatible with infectious aortic involvement. Staining for microorganisms was inconclusive because of autolytic artifacts, so M. tuberculosis was not directly demonstrated in the aortic wall.
Related reading