Primary Synovial Sarcoma of the Thyroid Diagnosed in a 27-Year-Old Patient
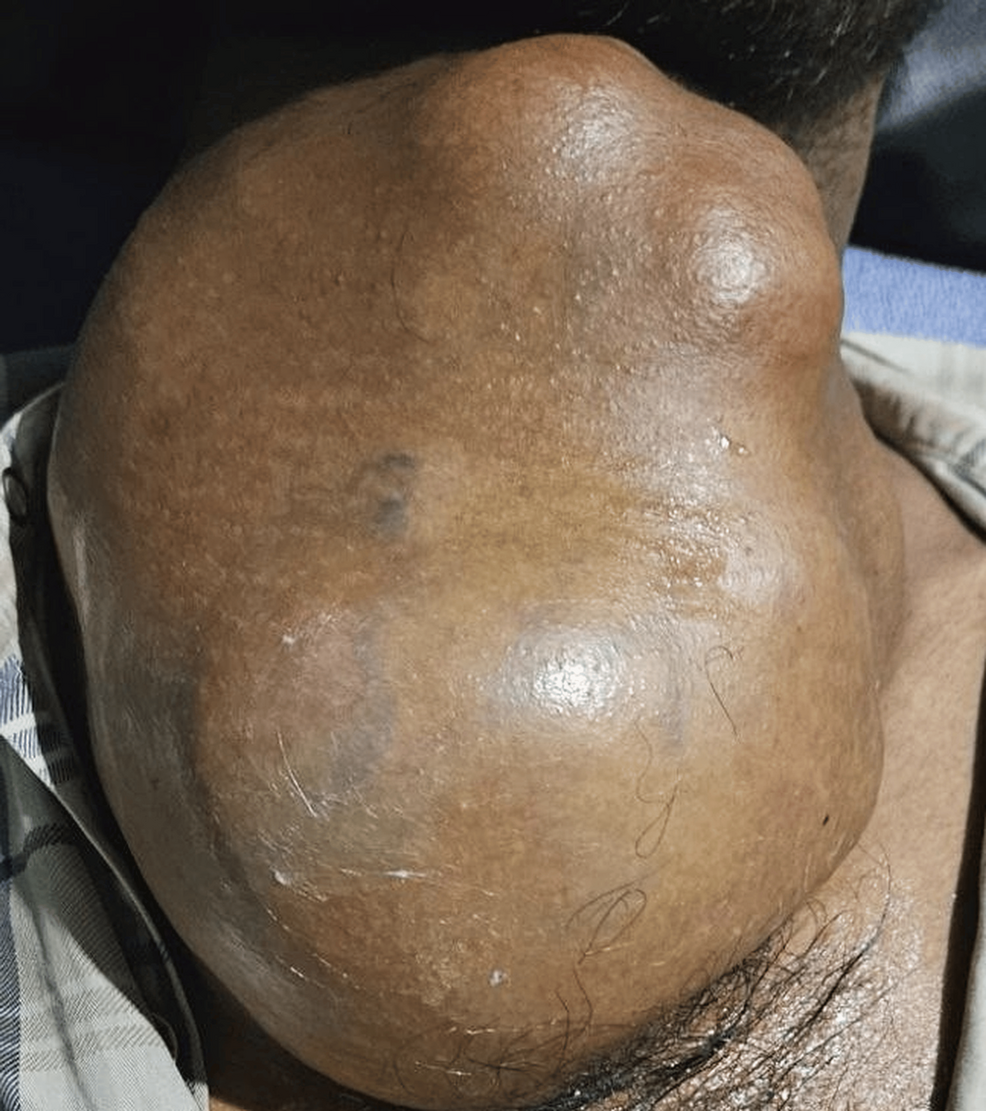
Primary synovial sarcoma of the thyroid is an exceptionally rare high-grade tumor, with medical literature documenting only 19 prior cases in English-language reports, Cureus reported in a detailed case study. A 27-year-old male patient presented to clinicians with a 13-centimeter anterior neck mass that enlarged progressively over 11 months, accompanied by dysphagia, dyspnea, cough, and hoarseness.
Clinical Presentation and Radiological Findings
The patient’s physical examination revealed a multilobulated, firm, and mildly tender midline neck mass that moved with swallowing. Diagnostic imaging, including a neck ultrasound, demonstrated a heterogeneous solid-cystic mass arising from the right thyroid lobe with coarse internal calcifications and prominent vascularity on color Doppler. Shear elastography measured a maximum elasticity of 113.85 kilopascals, indicating a heterogeneously stiff lesion.
Contrast-enhanced computed tomography of the neck mapped the mass from the hyoid bone to the manubrium sterni in the superior mediastinum. The imaging showed that the tumor encased the right common carotid artery by more than 180 degrees along a segment beginning a few centimeters above its origin, alongside encasement of the entire carotid bifurcation and the proximal-most parts of the internal and external carotid arteries. All involved vessel lumina remained patent, and the trachea was displaced without wall invasion.
Metastatic Spread and Diagnostic Confirmation
Chest computed tomography identified multiple variable-sized pulmonary metastatic nodules, including an 8.2-centimeter multilobulated lesion in the left hilar region, alongside bilateral hilar lymphadenopathy and a left-sided pleural effusion. Cytological examination of serosanguinous fluid obtained via diagnostic thoracentesis confirmed a malignant pleural effusion containing cellular clusters of spindle cells.
An ultrasound-guided core needle biopsy of the neck mass revealed a biphasic tumor composed of spindle and epithelial components. Immunohistochemistry showed focal staining for pan-cytokeratin, epithelial membrane antigen, and CD99, alongside diffuse nuclear expression of transducin-like enhancer of split 1 and positivity for vimentin and Bcl-2. Markers for primary thyroid carcinoma—including thyroid transcription factor-1, thyroglobulin, calcitonin, and PAX8—tested negative. Fluorescence in situ hybridization using an SS18-SSX fusion probe confirmed the diagnosis by demonstrating the characteristic t(X;18) translocation.
Multidisciplinary Management and Treatment Plan
Because the tumor involved major cervical blood vessels and had already produced distant pulmonary metastases and a malignant pleural effusion, the treating multidisciplinary team deemed upfront surgical resection unsafe. The patient began systemic chemotherapy with a regimen of doxorubicin and ifosfamide, with physicians planning to evaluate surgical options after assessing the initial treatment response. The patient completed four cycles of chemotherapy before being lost to follow-up, leaving the subsequent clinical course and final treatment outcome unknown.
Clinical Questions About Rare Thyroid Sarcoma
What defines primary synovial sarcoma of the thyroid histologically?
The tumor is classified histologically into monophasic, biphasic, or poorly differentiated forms, and it is definitively defined by the t(X;18) translocation that produces the characteristic SS18-SSX fusion gene.
Why was upfront surgery ruled out for this patient?
The multidisciplinary team considered initial surgery unsafe because the tumor encased the right common carotid artery and its branches by more than 180 degrees and had already spread to the lungs and pleural space.
What markers distinguished this tumor from typical thyroid cancer?
Immunohistochemistry tests for thyroid transcription factor-1, thyroglobulin, calcitonin, and PAX8 all returned negative results, ruling out standard primary thyroid carcinomas.
Related reading