Urgent Graft Replacement Follows Rapid Aneurysm Expansion
An 80-year-old man with polymyalgia rheumatica underwent urgent supracoronary ascending aortic replacement after his aorta expanded from 40 mm to 78 mm, as Cureus reported. The rapid aneurysmal growth, coupled with a focal ulcerated wall lesion, prompted medical intervention to prevent rupture. Subsequent histopathological analysis of the resected tissue revealed lymphocytic aortitis.
Presentation, History, and Accelerated Growth Metrics
The patient presented to the emergency department late in 2025 with intermittent palpitations, dizziness, and breathlessness lasting approximately one week. Medical records showed he had a history of arterial hypertension, dyslipidemia, and type 2 diabetes. Fluorodeoxyglucose-positron emission tomography performed in mid-2023 for polymyalgia rheumatica had revealed inflammatory uptake in his shoulder and pelvic girdles, without documented large-vessel vasculitis at that time. He had previously received treatment with methotrexate and glucocorticoids.
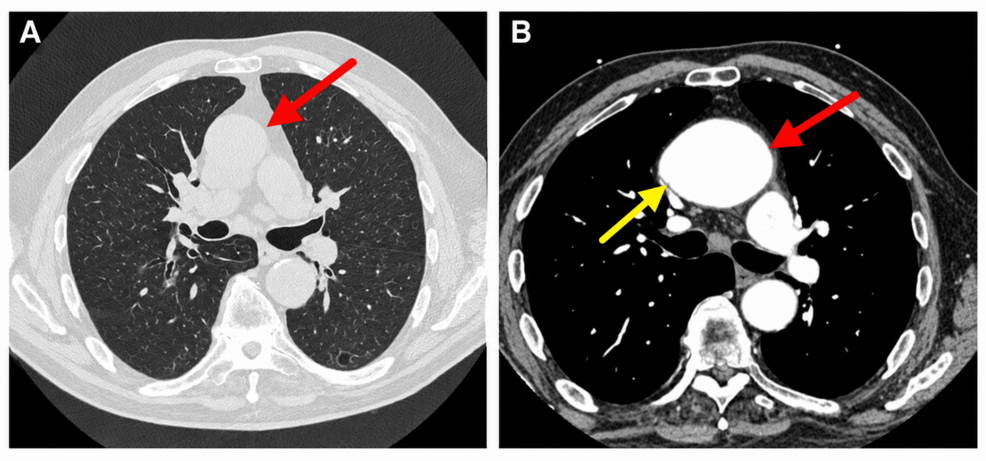
A non-contrast, non-ECG-gated chest CT performed for pulmonary evaluation in late 2024 showed an ascending aortic diameter of approximately 40 mm. A contrast-enhanced CT angiography scan performed one year later revealed that the ascending aorta had expanded to 78 mm in maximum diameter. While the difference in acquisition protocols between the two scans limited direct quantitative comparison, the interval change substantially exceeded the typical growth rate of 0.2 mm per year documented for nonsyndromic ascending aortic aneurysms.
Median Sternotomy and Intraoperative Dissection Challenges
The surgical team performed median sternotomy two days after the diagnostic CT angiography scan. Intraoperative inspection confirmed marked aneurysmal enlargement alongside a focal ulceration of the aortic wall. Surgeons used femoral arterial and right atrial venous cannulation to establish normothermic cardiopulmonary bypass.
Dissection of the diseased aorta proved challenging due to surrounding inflammatory changes that complicated tissue plane separation. After applying aortic cross-clamping and cold blood cardioplegia, surgeons resected the aneurysmal segment and implanted a 32-mm Dacron graft. Proximal and distal anastomoses were secured using 4-0 polypropylene sutures reinforced with felt strips and surgical sealant. The procedure involved 162 minutes of cardiopulmonary bypass and 123 minutes of aortic cross-clamping without circulatory arrest.
Microscopic Analysis and Lymphocytic Infiltrate Identification
The final pathology report diagnosed lymphocytic arteritis, noting that the findings warranted clinical correlation to exclude Horton’s disease.
Postoperative Complications and 47-Day PET-CT Clearance
The early postoperative course involved hemorrhagic shock that required vasopressor support and one unit of packed red blood cells. A follow-up fluorodeoxyglucose-positron emission tomography and computed tomography scan performed 47 days after surgery showed no metabolic evidence of active large-vessel vasculitis.