Retrospective Dental Review Evaluates 46 Molar Sites Treated in Private Practice Over Five Years
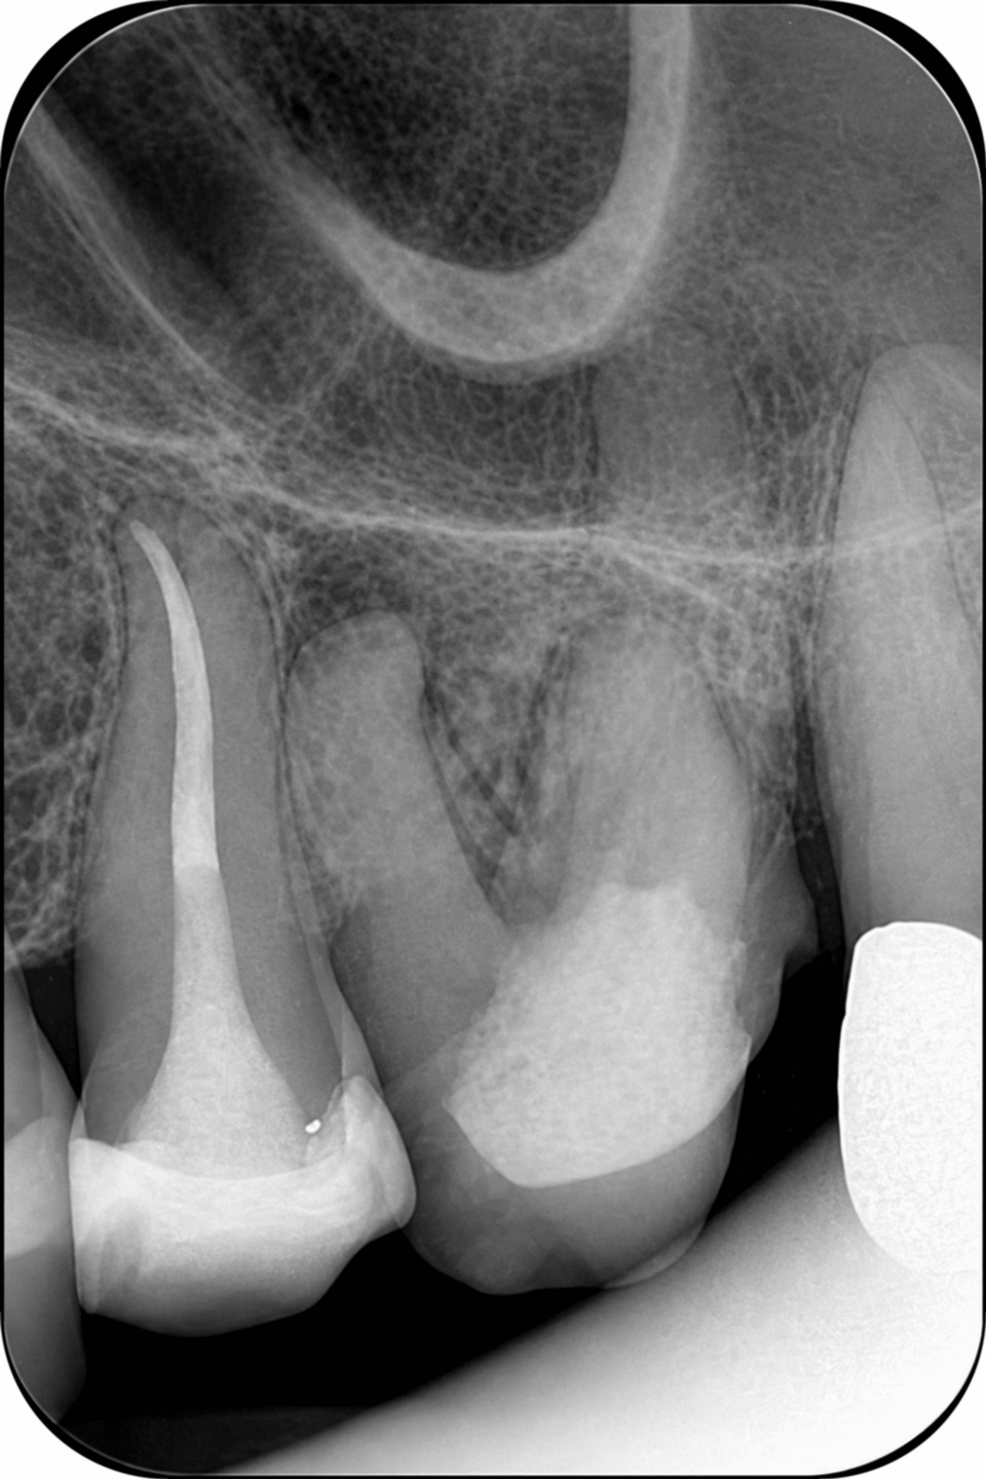
A clinical case series evaluated 46 molar sites across 46 patients who underwent immediate implant placement with planned immediate restorative management over a five-year period. The retrospective study, conducted entirely in private practice settings, contrasts with parallel investigations from academic medical centers. While posterior extraction sites present complex anatomical challenges, the private practice review documented limited mechanical complications using a restoratively driven protocol.
Nicholas Fahey performed all procedures and managed or reviewed the available follow-up records. The private practice series recorded 23 maxillary and 23 mandibular sites experiencing failing molars. The clinical protocol required cone beam computed tomography (CBCT) imaging and an intraoral scan prior to surgery. This planning centered on the digitally planned implant position rather than simply following the center of the extraction socket. During the procedures, clinicians utilized custom surgical guides.
Complications across the 46 private practice cases remained minimal. Maxillary case 12 experienced postoperative pain, while maxillary case 15 involved a loose custom healing abutment that was tightened at the initial postoperative visit alongside a recorded insertion torque of 25 N·cm. Mandibular case 15 exhibited slight recession at the custom healing abutment site. Meanwhile, mandibular case 20 did not achieve adequate primary stability, and custom healing abutment placement was delayed for 12 weeks.
Diverging Outcomes in Posterior Extraction Site Trials
Academic evaluations report higher failure rates when executing immediate implant placement in posterior regions. A prospective pilot study conducted at the Department of Oral and Maxillofacial Surgery (University of Groningen, University Medical Hospital) examined 15 consecutive patients receiving immediate implants in molar extraction sockets. That prospective trial documented that four of the 15 mobile implants failed and required removal before the one-year mark, yielding an implant and restoration survival rate of 73.3%.

Researchers note that while immediate implant placement has become common in the maxillary aesthetic zone, posterior applications involve distinct anatomical obstacles. Divergent roots, broad extraction sockets, variable interradicular bone, and proximity to the maxillary sinus floor or the inferior alveolar canal constrain surgical execution. Although systematic reviews cited by the Groningen investigators indicate high survival rates in select molar studies, wide-diameter implants have similarly been associated with elevated failure rates in other controlled clinical trials.
Clinical Protocol Variations and Patient Selection Criteria
The private practice series enforced an inclusion requirement where failing molars were slated for immediate implant replacement, with the sole exclusion criterion being an extraction site too large to permit immediate placement. Conversely, the academic trial at the University of Groningen restricted its 15 patient enrollments strictly to sites presenting enough bone to expect primary implant stability and an implant site free of infection. Pre-existing infection was recorded in 37 of 45 sites with documented status in the private practice cohort, representing 82.2% of the cases.
Provisional materials also varied significantly between the evaluated cohorts. The private practice cases utilized zirconia provisional materials in 24 sites, polymethyl methacrylate in 18 sites, and composite in three sites. Insertion torque values across 45 of those private practice entries spanned 25-80 N·cm. Residual defects were managed selectively using autogenous bone collected during osteotomy preparation combined with particulate allograft and platelet-derived material, with barrier membrane and/or connective-tissue grafting added when the buccal plate or soft-tissue volume required additional support.
Clinical differences and follow-up timelines in trials
What was the primary clinical difference between the private practice case series and the academic trial?
The private practice series evaluated 46 molar sites where 82.2% of documented cases presented with pre-existing infection, whereas the academic trial at the University of Groningen explicitly restricted its 15 patient enrollments to infection-free sites expected to achieve primary stability.
How long were patients followed in these clinical evaluations?
The private practice case series reviewed patients at two and eight weeks, with the restorative phase initiated at 12 weeks, while the prospective academic trial tracked its patients for a 1-year follow-up period after restoration placement.
What specific provisional materials were used in the private practice procedures?
Clinicians utilized zirconia for provisional restorations in 24 sites, polymethyl methacrylate in 18 sites, and composite in three sites.
Worth a look